Related Experiment Video
Updated: Jun 23, 2026
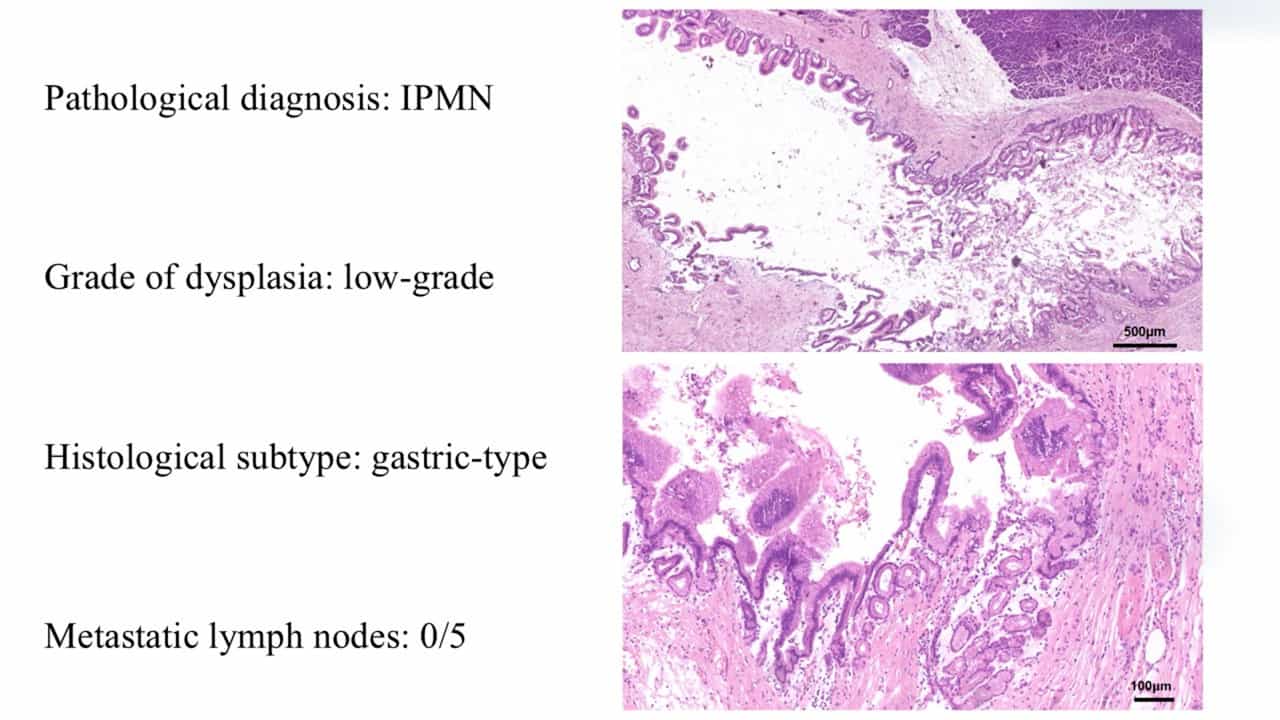

Robotic Duodenum-preserving Total Pancreatic Head Resection for Intraductal Papillary Mucinous Neoplasms
Published on: April 17, 2026
Pancreatic injury response is different depending on the method of resecting the parenchyma
Teemu Lämsä1, Hai-Tao Jin, Panu H Nordback
1Department of Gastroenterology and Alimentary Tract Surgery, Tampere University Hospital, Tampere, Finland.

Objectives:
The present study was performed to compare the pancreatic injury response on the parenchymal resection either with ultrasonic scissors, electrocautery, or surgical scalpel.
Methods:
A 1 x 0.5 cm piece of rat pancreas was resected from side of the pancreas either with ultrasonic scissors (Harmonic Scalpel; UltraCision, Ethicon Endosurgery Inc., Cincinnati, OH) or electrocautery (Force FX; Valleylab, Tyco Healthcare Group LP, Boulder, CO) at two power levels, 1 and 3; 8W and 25W, respectively, or with surgical scalpel. Hemostasis was provided after surgical scalpel either with cellulose patch (Interceed; Johnson and Johnson Medical, Inc., New Brunswick, NJ), three stitches of 6-0 polydioxanone at tightness of 0.6N or fibrin glue (Tisseel Duo Quick; Baxter AG, Wien, Austria). Blood sample and pancreas specimens, both at the resection site and far away, were taken 1, 7, and 21 days postoperatively from exposed animals, sham operated animals (n = 18 in each) and from unexposed baseline animals (n = 5). Necrosis, edema, leukocyte infiltration, hemorrhage, vacuolization, and fibrosis were histologically assessed separately.
Results:
Each resection and sham operation induced similar increase in the amylase activity on day 1 with normalization by day 7. Resection with ultrasonic scissors and electrocautery induced more tissue injury to the pancreas than resection with surgical scalpel independent of the method for hemostasis. The injury, although somewhat milder in intensity, was also observed in parts of the pancreas located far away from the site of resection.
Conclusions:
Of the compared methods, surgical scalpel resection plus cellulose patch or fibrin glue hemostasis induced the least histological changes in the pancreatic parenchyma. This injury response spread over the pancreas.
Related Concept Videos
 01:21
Acute Pancreatitis II: Pathophysiology
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:27
Acute Pancreatitis I: Introduction
Acute pancreatitis is characterized by rapid inflammation of the pancreas, often caused by factors like gallstone blockage or excessive alcohol consumption. Chronic pancreatitis, on the other hand, is a slow, progressive inflammation that may result from long-term alcohol abuse, obstructions in the pancreatic duct, or genetic factors.
The causes of acute pancreatitis include:
 01:25
Acute Pancreatitis I: Introduction
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management