Related Experiment Video
Updated: Jun 23, 2026

Translaminar Autonomous System Model for the Modulation of Intraocular and Intracranial Pressure in Human Donor Posterior Segments
Published on: April 24, 2020
Congenital central hypoventilation syndrome from past to future: model for translational and transitional autonomic
Debra E Weese-Mayer1, Casey M Rand, Elizabeth M Berry-Kravis
1Department of Pediatrics, Children's Memorial Hospital, Northwestern University Feinberg School of Medicine, Chicago, IL 60614, USA. dweese-mayer@childrensmemorial.org

Abstract:
The modern story of CCHS began in 1970 with the first description by Mellins et al., came most visibly to the public eye with the ATS Statement in 1999, and continues with increasingly fast paced advances in genetics. Affected individuals have diffuse autonomic nervous system dysregulation (ANSD). The paired-like homeobox gene PHOX2B is the disease-defining gene for CCHS; a mutation in the PHOX2B gene is requisite to the diagnosis of CCHS. Approximately 90% of individuals with the CCHS phenotype will be heterozygous for a polyalanine repeat expansion mutation (PARM); the normal allele will have 20 alanines and the affected allele will have 24-33 alanines (genotypes 20/24-20/33). The remaining approximately 10% of individuals with CCHS will have a non-PARM (NPARM), in the PHOX2B gene; these will be missense, nonsense, or frameshift. CCHS and PHOX2B are inherited in an autosomal dominant manner with a stable mutation. Approximately 8% of parents of a CCHS proband will be mosaic for the PHOX2B mutation. A growing number of cases of CCHS are identified after the newborn period, with presentation from infancy into adulthood. An improved understanding of the molecular basis of the PHOX2B mutations and of the PHOX2B genotype/CCHS phenotype relationship will allow physicians to anticipate the clinical phenotype for each affected individual. To best convey the remarkable history of CCHS, and to describe the value of recognizing CCHS as a model for translational and transitional autonomic medicine, we present this review article in the format of a chronological story, from 1970 to the present day.

Related Concept Videos
 01:23
Physiological Control of Respiration
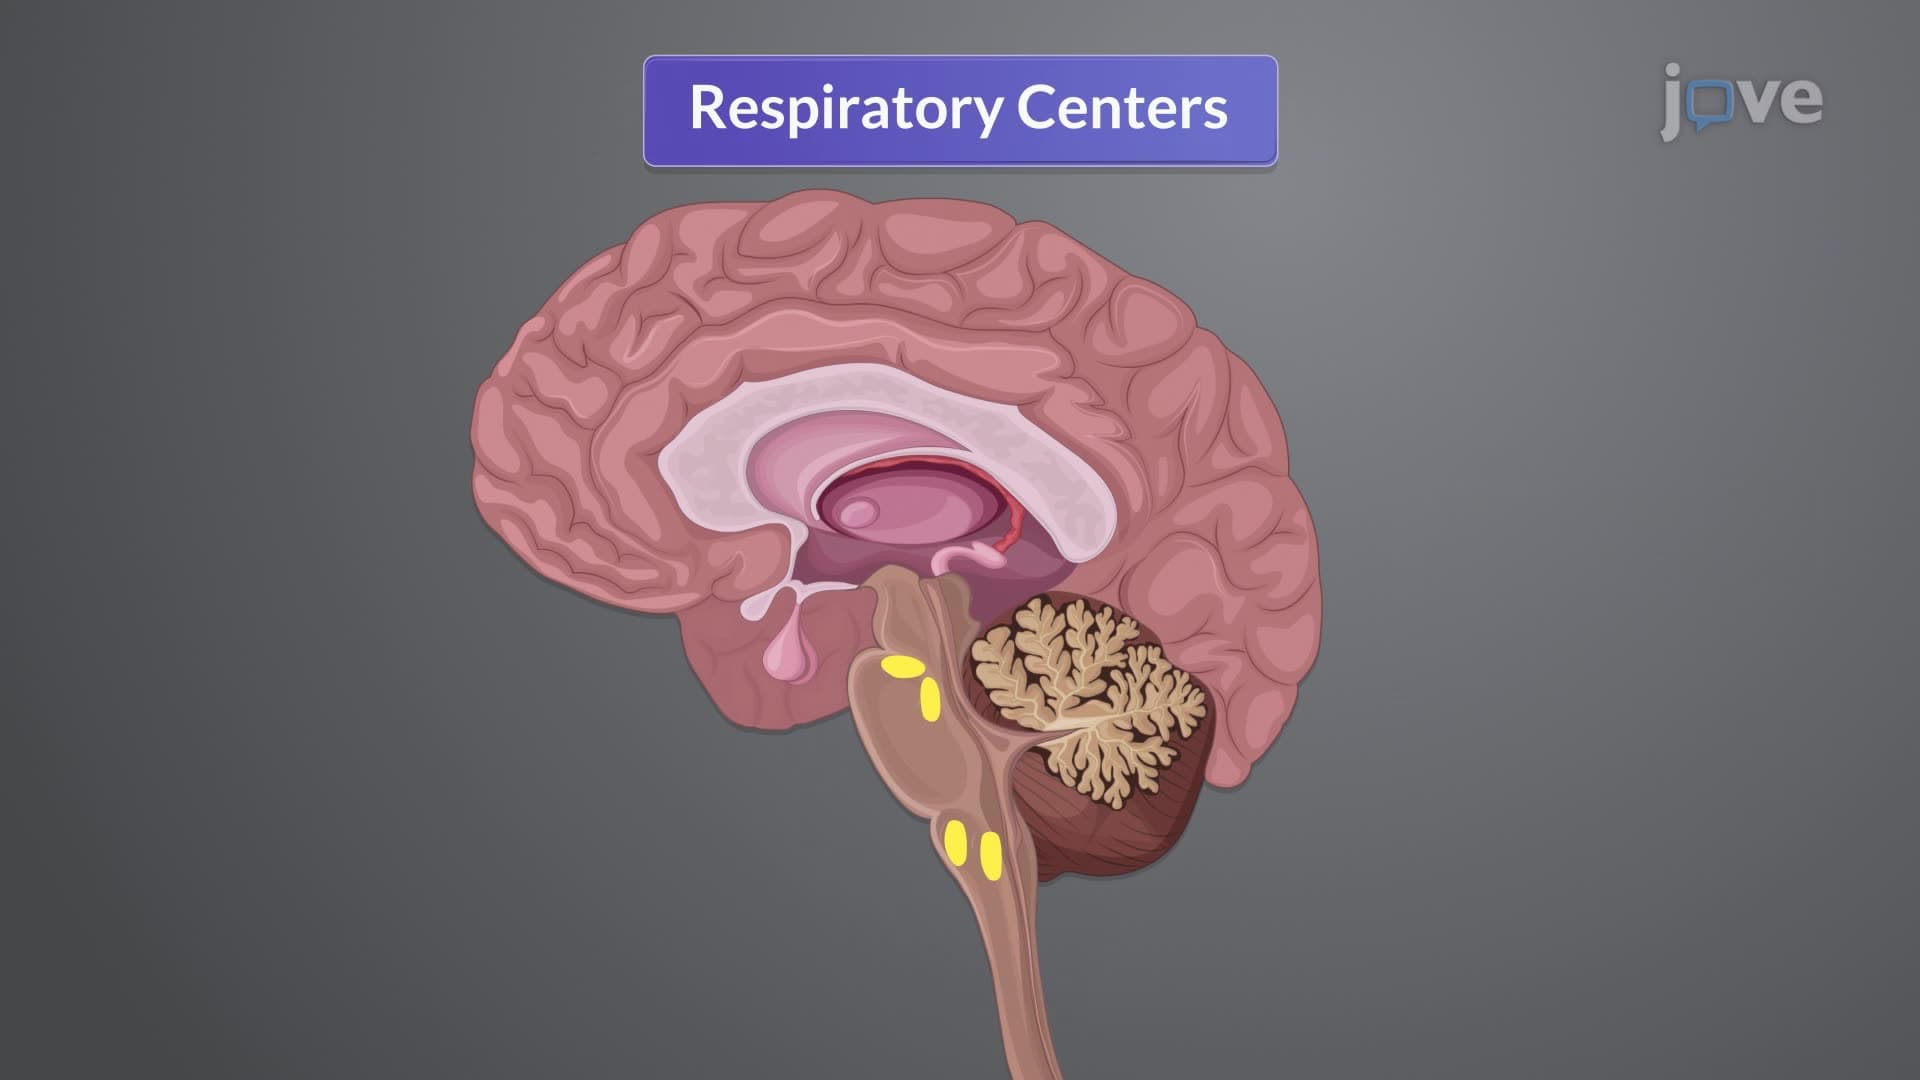
Breathing, a seemingly passive process, is regulated by the respiratory center in the brainstem. This center coordinates the involuntary control of respirations, which means it occurs without conscious effort, ensuring a smooth and uninterrupted pattern.
Regulation of Ventilation
The body maintains ventilation by monitoring levels of carbon dioxide (CO2), oxygen (O2), and hydrogen ion concentration (pH) in the arterial blood. Among these factors, the level of CO2 plays a crucial...
 01:22
Physiology of Respiration II: Neurogenic Control of Respiration
Central Control
The brainstem is the primary site of central control, hosting respiratory centers:
 01:30
Pulmonary Hypertension: Classification and Pathogenesis
There are various classifications for PH, each relating to different underlying causes and also...
 01:18
Neural Control of Respiration
Respiratory Centers in the Brainstem
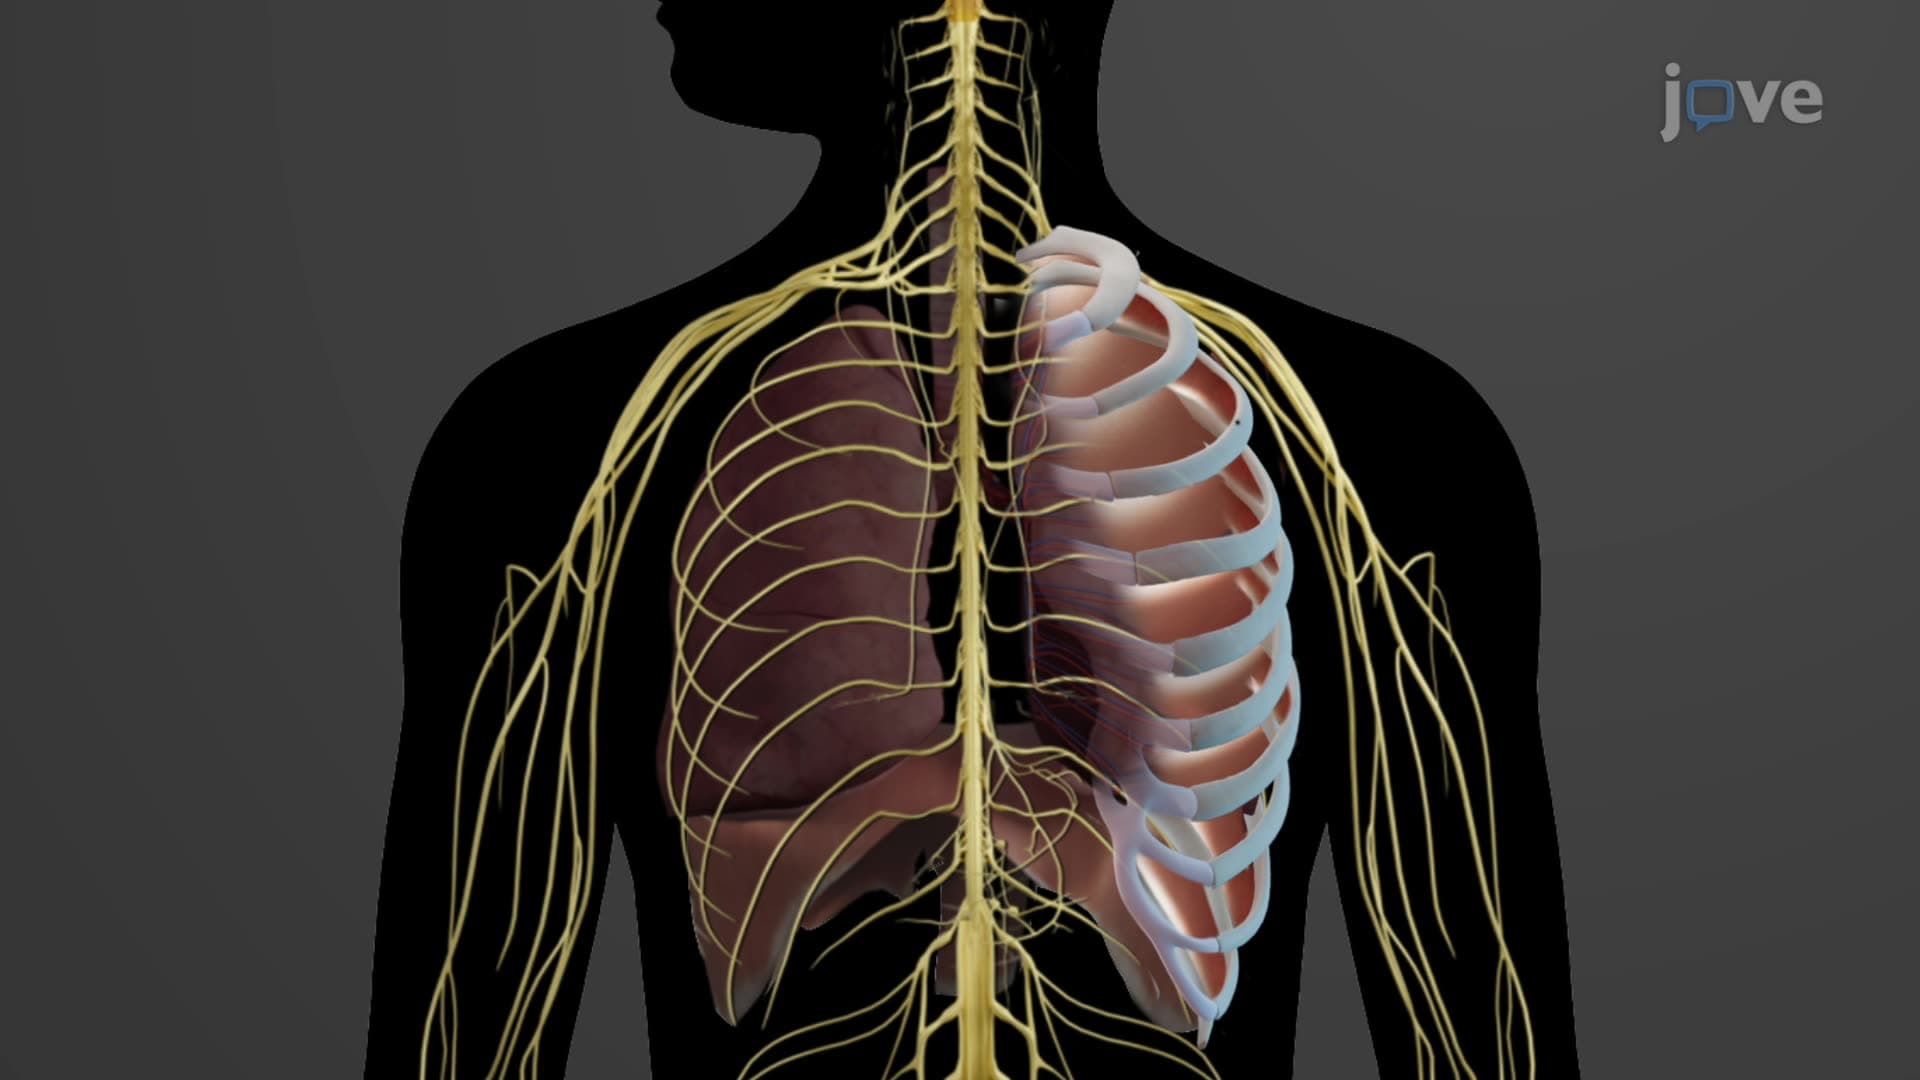
Two primary areas comprise the respiratory center: the medullary respiratory center in the medulla oblongata and the pontine respiratory group in the pons. The...
 01:25
Hyperpnea and Hyperventilation