Related Experiment Video
Updated: Jun 23, 2026
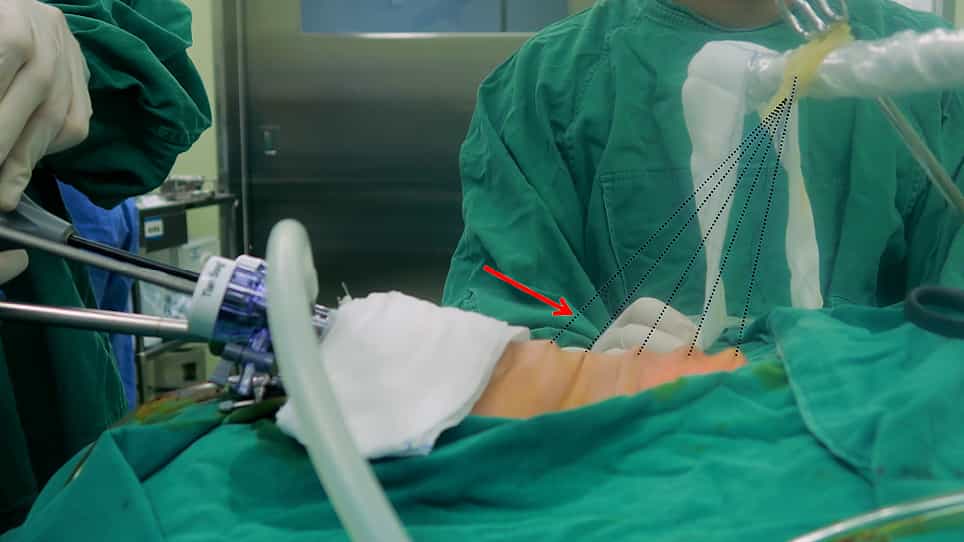

Transoral Endoscopic Thyroidectomy Vestibular Approach for Thyroid Lobectomy
Published on: May 12, 2023
Outcomes following thyroid and parathyroid surgery in pregnant women
Sreyram Kuy1, Sanziana A Roman, Rani Desai
1Department of Surgery, Division of Endocrine Surgery, Yale University School of Medicine, New Haven, CT 06520-8062, USA.

Objectives:
To perform the first population-based measurement of clinical and economic outcomes after thyroid and parathyroid surgery in pregnant women and identify the characteristics of this population and the predictors of outcome.
Design:
Retrospective cross-sectional study.
Setting:
Health Care Utilization Project Nationwide Inpatient Sample (HCUP-NIS), a 20% sample of nonfederal US hospitals.
Patients:
All pregnant women, compared with age-matched nonpregnant women, who underwent thyroid and parathyroid procedures from 1999 to 2005.
Main Outcome Measures:
Fetal, maternal, and surgical complications, in-hospital mortality, median length of stay, and hospital costs.
Results:
A total of 201 pregnant women underwent thyroid (n = 165) and parathyroid (n = 36) procedures and were examined together. The mean age was 29 years, 60% were white, 25% were emergent or urgent admissions, and 46% had thyroid cancer. Compared with nonpregnant women (n = 31 155), pregnant patients had a higher rate of endocrine (15.9 vs 8.1%; P < .001) and general complications (11.4 vs 3.6%; P < .001), longer unadjusted lengths of stay (2 days vs 1 day; P < .001), and higher unadjusted hospital costs ($6873 vs $5963; P = .007). The fetal and maternal complication rates were 5.5% and 4.5%, respectively. On multivariate regression analysis, pregnancy was an independent predictor of higher combined surgical complications (odds ratio, 2; P < .001), longer adjusted length of stay (0.3 days longer; P < .001), and higher adjusted hospital costs ($300; P < .001). Other independent predictors of outcome were surgeon volume, patient race or ethnicity, and insurance status.
Conclusions:
Pregnant women have worse clinical and economic outcomes following thyroid and parathyroid surgery than nonpregnant women, with disparities in outcomes based on race, insurance, and access to high-volume surgeons.

Related Concept Videos
 01:17
Hormones and Bone Tissue
Hormones That Influence Osteoblasts and/or Maintain the Matrix
Several hormones are necessary for controlling bone growth and maintaining the bone matrix. The pituitary gland secretes growth hormone (GH), which, as its name implies, controls bone growth. This happens in several ways: first, it triggers chondrocyte...
 00:59
The Parathyroid Glands
Oxyphil cells, whose functions remain elusive, emerge during late puberty, adding a layer of complexity to the parathyroid gland's intricacies. In contrast, principal parathyroid cells undertake a vital role by producing...
 01:21
Skeleton and Calcium Homeostasis
 00:51
Synthesis and Functions of Calcitonin
The exact mechanisms by which calcitonin operates in calcium homeostasis remain elusive, but its significance is evident in several vital...
 01:27
Hyperthyroidism II: Pathophysiology
 01:18
Functions of Thyroid Hormones
TH is indispensable for the normal development and maturation of the skeletal, muscular, and nervous systems during fetal and childhood growth. It facilitates bone mineral turnover and regulates protein synthesis in developing tissues, contributing significantly to overall growth and...