Related Experiment Video
Updated: Jun 22, 2026
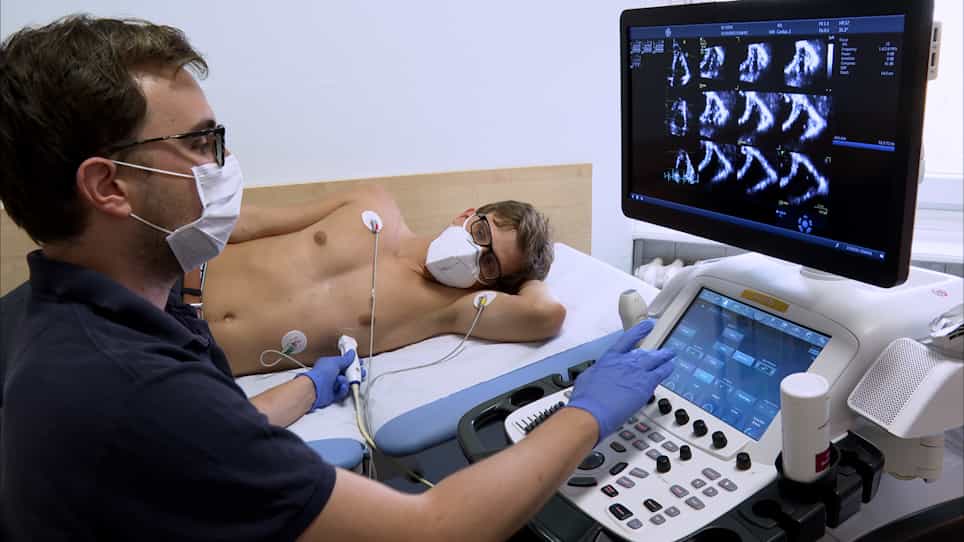
Morphological and Functional Assessment of the Right Ventricle Using 3D Echocardiography
Published on: October 28, 2020
Clinical study of 39 Chinese patients with arrhythmogenic right ventricular dysplasia/cardiomyopathy
Ke-juan Ma1, Ning Li, Hong-tao Wang
1Center for Arrhythmia Diagnosis and Treatment, Fu Wai Cardiovascular Hospital, Chinese Academy of Medical Sciences & Peking Union Medical College, Beijing, China.

Insights
This study details the clinical and electrocardiogram features of Chinese patients with arrhythmogenic right ventricular dysplasia/cardiomyopathy (ARVD/C). Implantable cardioverter-defibrillators (ICDs) offer protection, but ventricular tachycardia recurrence remains a challenge.
Area of Science:
- Cardiology
- Electrophysiology
- Genetic Heart Diseases
Background:
- Limited studies exist on the clinical profile of Chinese patients diagnosed with arrhythmogenic right ventricular dysplasia/cardiomyopathy (ARVD/C).
- Understanding ARVD/C in this population is crucial for accurate diagnosis and management.
Purpose of the Study:
- To describe the clinical characteristics of ARVD/C patients from China.
- To define the specific electrocardiogram (ECG) features in this cohort.
- To evaluate treatment outcomes for ARVD/C in Chinese patients.
Main Methods:
- Retrospective analysis of 39 ARVD/C patients hospitalized between 1998 and 2006.
- Data collection from medical archives and follow-up records.
Main Results:
- The majority of patients (33/39) were male, presenting at an average age of 34.9 years.
- Common symptoms included palpitations (62%) and syncope (44%).
- Key ECG findings were: QRSd >or= 110 ms (69%), epsilon wave (59%), QRSd ratio V(1-3)/V(4-6) >or= 1.2 (82%), T-wave inversions and S-wave upstroke in V(1-3) (96% and 90% in patients without RBBB).
- Radiofrequency catheter ablation (RFCA) for ventricular tachycardia (VT) had a 68% success rate, but VT recurrence was 46% over 16.7 months.
- Implantable cardioverter-defibrillators (ICDs) were effective, with all recipients receiving appropriate shocks.
- One sudden cardiac death and one heart transplant occurred in patients treated with antiarrhythmic drugs alone.
Conclusions:
- This study characterizes the clinical and ECG features of ARVD/C in a Chinese cohort.
- ICDs provide essential protection against malignant arrhythmias in ARVD/C patients.
- High recurrence rates of VT pose a significant challenge for RFCA therapy in ARVD/C management.
Background:
There are few studies on the clinical profile of Chinese patients with arrhythmogenic right ventricular dysplasia/cardiomyopathy (ARVD/C). The purpose of this study was to describe the clinical characteristics of ARVD/C patients from China, particularly to define the features of electrocardiograph and treatment outcomes.
Methods:
Thirty-nine patients hospitalized in Fu Wai Cardiovascular Hospital from 1998 to 2006 were included. The data were obtained from the medical archive and the follow-up records.
Results:
Of these patients 33 were male and 6 female (age at the first presentation was (34.9 +/- 9.8) years). The most common symptoms were palpitation (62%) and syncope (44%). Right precordial QRSd >or= 110 ms was detected in 69% of the patients, epsilon wave in 59%, and a ratio of QRSd in V(1) + V(2) + V(3)/V(4) + V(5) + V(6) >or= 1.2 in 82%. The most frequent features of electrocardiogram in patients without right bundle-branch block were T-wave inversions and S-wave upstroke in V(1)-V(3) >or= 55 ms (96% and 90% of 28 patients, respectively). Radiofrequency catheter ablation (RFCA) for ventricular tachycardia (VT) was successful in 15 (68%) of 22 patients. The recurrence rate of VT was 46% (7/15) during the follow-up of (16.7 +/- 11.2) months. Seven patients had cardioverter/defibrillator (ICD) implanted plus drug therapy and 17 patients took antiarrhythmic drugs alone. During the follow-up of (35.6 +/- 19.0) months, all patients with ICD implanted received at least one appropriate ICD shock. One patient died of ventricular fibrillation suddenly and one patient underwent heart transplantation for progressive biventricular heart failure during the drug therapy alone.
Conclusions:
This study demonstrated the clinical and ECG features of the 39 ARVD/C Chinese patients. ICD provided life-saving protection by effectively terminating malignant arrhythmias, and the high recurrence of VT was the major problem of RFCA therapy.
More Related Videos
 09:36
Dual-Dye Optical Mapping of Hearts from RyR2R2474S Knock-In Mice of Catecholaminergic Polymorphic Ventricular Tachycardia
Published on: December 22, 2023
 09:16
Isolation and Characterization of Cardiac Mesenchymal Stromal Cells from Endomyocardial Bioptic Samples of Arrhythmogenic Cardiomyopathy Patients
Published on: February 28, 2018
Related Concept Videos
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy
 01:29
Cardiomyopathy IV: Restrictive Cardiomyopathy
 01:25
Cardiomyopathy I: Introduction and Classification
 01:30
Dysrhythmias V: Evaluating Dysrhythmias
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:29
Cardiomyopathy V: Interprofessional Care