Related Experiment Video
Updated: Jun 22, 2026


Hybrid PET/MRI Imaging of Alzheimer's Disease Based on 18F-AV-1451
Published on: April 18, 2025
Amyloid PET and MRI in Alzheimer's disease and mild cognitive impairment
E Dimou1, J Booij, M Rodrigues
1Department of Nuclear Medicine, University Hospital, Vienna, Austria.

Abstract:
The neurodegenerative disorder Alzheimer's disease (AD) is the most common form of dementia. It is characterized by progressive impairment of cognitive functions and behavior. To distinguish clinically AD from other forms of dementia is an ongoing challenge. In addition, although mild cognitive impairment (MCI) is recognized as a risk factor for dementia, it remains a challenge to predict on an individual level who will convert to become demented. Amyloid beta (Abeta) is one of the crucial pathological findings in AD. Recently, amyloid tracers for PET imaging have been developed successfully which may offer the unique possibility for measuring fibrillar Abeta load in the living brain. Therefore, in the near future positron emission tomography (PET) may become an important tool for in vivo amyloid imaging contributing to early (differential) diagnosis as well as evaluation of treatment response in AD. Moreover, Abeta may play a role in prediction the conversion of MCI to AD. In this paper we review the recent development of the molecular imaging technique PET and its different radiopharmaceuticals on the trail for imaging amyloid in AD and the conversion of MCI to AD.
Insights
Positron emission tomography (PET) with new amyloid tracers can visualize amyloid beta in Alzheimer's disease (AD) brains. This technique aids in early AD diagnosis and predicting mild cognitive impairment (MCI) to AD conversion.
Area of Science:
- Neuroscience
- Medical Imaging
- Radiochemistry
Background:
- Alzheimer's disease (AD) is the most common dementia, marked by cognitive decline.
- Differentiating AD from other dementias and predicting mild cognitive impairment (MCI) progression to AD are clinical challenges.
- Amyloid beta (Abeta) is a key pathological hallmark of AD.
Purpose of the Study:
- To review the advancements in Positron Emission Tomography (PET) and radiopharmaceuticals for amyloid imaging in AD.
- To explore the potential of in vivo amyloid imaging for early diagnosis and treatment evaluation in AD.
- To assess the role of Abeta in predicting MCI conversion to AD.
Main Methods:
- Review of recent developments in PET imaging technology.
- Discussion of novel radiopharmaceuticals for detecting fibrillar Abeta.
- Analysis of studies on the utility of PET imaging in AD and MCI.
Main Results:
- Successful development of amyloid tracers for PET imaging allows measurement of fibrillar Abeta load in living brains.
- PET imaging shows promise for early and differential diagnosis of AD.
- Abeta imaging may aid in predicting the conversion of MCI to AD.
Conclusions:
- PET imaging with amyloid tracers is emerging as a vital tool for Alzheimer's disease diagnosis and management.
- In vivo amyloid imaging can potentially improve the prediction of MCI to AD conversion.
- Further research and clinical application of PET imaging are expected to advance AD understanding and treatment.
Related Concept Videos
 01:26
Alzheimer's Disease: Overview
The clinical diagnosis of AD hinges on the presence of memory and other cognitive impairments. Biomarkers, such as changes in Aβ and tau...
 01:23
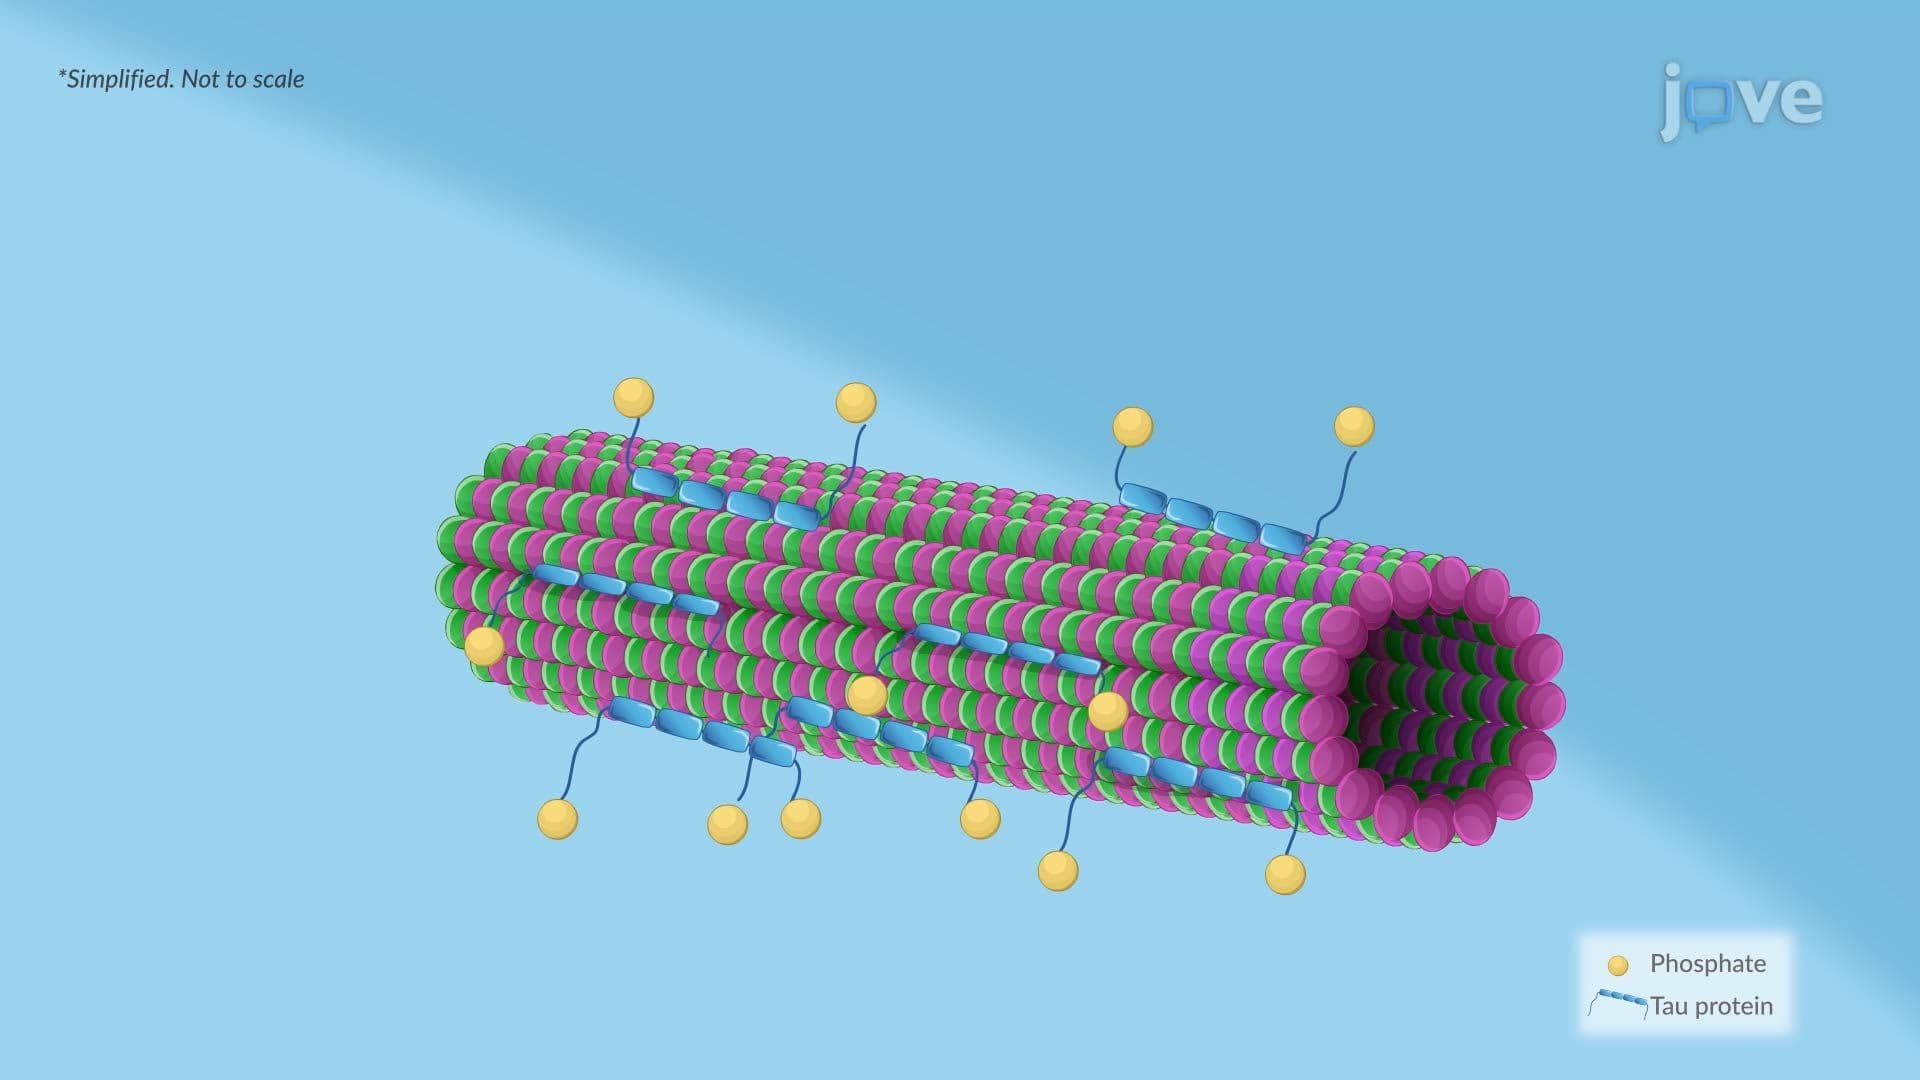
Alzheimer Disease ll: Pathophysiology
 01:22
Alzheimer's Disease: Treatment
 01:29
Alzheimer Disease l: Introduction