Related Experiment Video
Updated: Jun 22, 2026


Bronchial Thermoplasty: A Novel Therapeutic Approach to Severe Asthma
Published on: November 4, 2010
[Bronchial reversibility in the patients with bronchiectasis]
Seher Sevgili1, H Canan Hasanoğlu, Ayşegül Karalezli
1Batman State Hospital, Batman, Turkey.

Abstract:
Pulmonary infections during childhood is an important factor in bronchiectasis ethiology. This disease sometimes may be confused with asthma in diagnosis. Because of bronchial obstruction, the bronchiectasis patients can be misdiagnosed as asthmatic. In this study we aimed to show the obstructive pattern and reversibility percentage in bronchiectasis. The 107 bronchiectasis patients that diagnosed with high resolution computed tomography scanning were included to the study. As a control group 40 volunteers that have no respiratory symptom were chosen randomly. There were 64 (59.81%) men and 43 (40.19%) women patients with a mean age of 48.89 +/- 14.33 years. In control group 40 healthy individuals with a mean age of 43.60 +/- 11.41 were present. The spirometry was done to measure FEV(1), FVC, FEF(25-75%) and reversibility of all 107 individuals and control group. Also diffusion capacity and lung volumes of patients and control group were measured. In the study group 78 (72.90%) patients had obstructive, 26 (24.30%) patients had mixed and 3 (2.80%) patients had restrictive pulmonary function abnormality. Reversibility percentage was recorded as positive for 39 patients in FEV(1) (36.45%) and as positive (> 20%) for 63 patients in FEF(25-75%) (58.9%). In this group mean reversibility percentage in FEV(1) was 19.51 +/- 6.59 and in FEF(25-75%) was 38.62 +/- 26.49. In control group reversibility ratio was 0% for FEV(1). We determined reversibility ratio as 36.45% for FEV(1) and as 58.9% for FEF(25-75%) in our study group, so bronchial reversibility is shown frequently in patients with bronchiectasis. Unfortunately bronchiectasis is often misdiagnosed and some patients are treated for presumed asthma for years. Therefore differential diagnosis of bronchiectasis and asthma should not only be evaluated by reversibility but also by radiologically.
Insights
Childhood pulmonary infections can lead to bronchiectasis, often misdiagnosed as asthma due to bronchial obstruction. This study reveals significant bronchial reversibility in bronchiectasis patients, highlighting the need for accurate differential diagnosis beyond spirometry.
Area of Science:
- Pulmonology
- Respiratory Medicine
- Clinical Diagnostics
Context:
- Childhood pulmonary infections are a significant risk factor for developing bronchiectasis.
- Bronchiectasis diagnosis can be challenging, often confused with asthma due to shared symptoms like bronchial obstruction.
- Misdiagnosis can lead to prolonged, incorrect asthma treatment for bronchiectasis patients.
Purpose:
- To investigate the presence and extent of obstructive patterns and bronchial reversibility in patients with bronchiectasis.
- To differentiate bronchiectasis from asthma by evaluating spirometry parameters, including forced expiratory volume in 1 second (FEV1) and forced expiratory flow rate (FEF25-75%).
- To assess the utility of spirometry and reversibility testing in the differential diagnosis of bronchiectasis.
Summary:
- The study included 107 bronchiectasis patients and 40 healthy controls, assessing pulmonary function via spirometry, lung volumes, and diffusion capacity.
- A significant proportion of bronchiectasis patients exhibited obstructive (72.90%) or mixed (24.30%) pulmonary function patterns.
- Bronchial reversibility was frequently observed in bronchiectasis patients, with positive reversibility noted in 36.45% for FEV1 and 58.9% for FEF25-75%, compared to 0% in controls.
Impact:
- Demonstrates that bronchial reversibility is a common finding in bronchiectasis, complicating its differentiation from asthma based solely on spirometry.
- Emphasizes the critical need for integrating radiological findings, such as high-resolution computed tomography (HRCT) scans, with spirometry for accurate differential diagnosis.
- Highlights the potential for improved diagnostic accuracy and timely, appropriate treatment for bronchiectasis by distinguishing it from asthma.
Related Concept Videos
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features
 01:17
Pulmonary Cycle: Exhalation
 01:26
COPD: Management Using Bronchodilators and Corticosteroids
 01:17
Drugs Used in Lower Respiratory Disorders: Overview
Bronchodilators, the first step of respiration enhancement, come in various forms, each with its own mechanism...
 01:27
Pneumothorax-II
Clinical Manifestations:
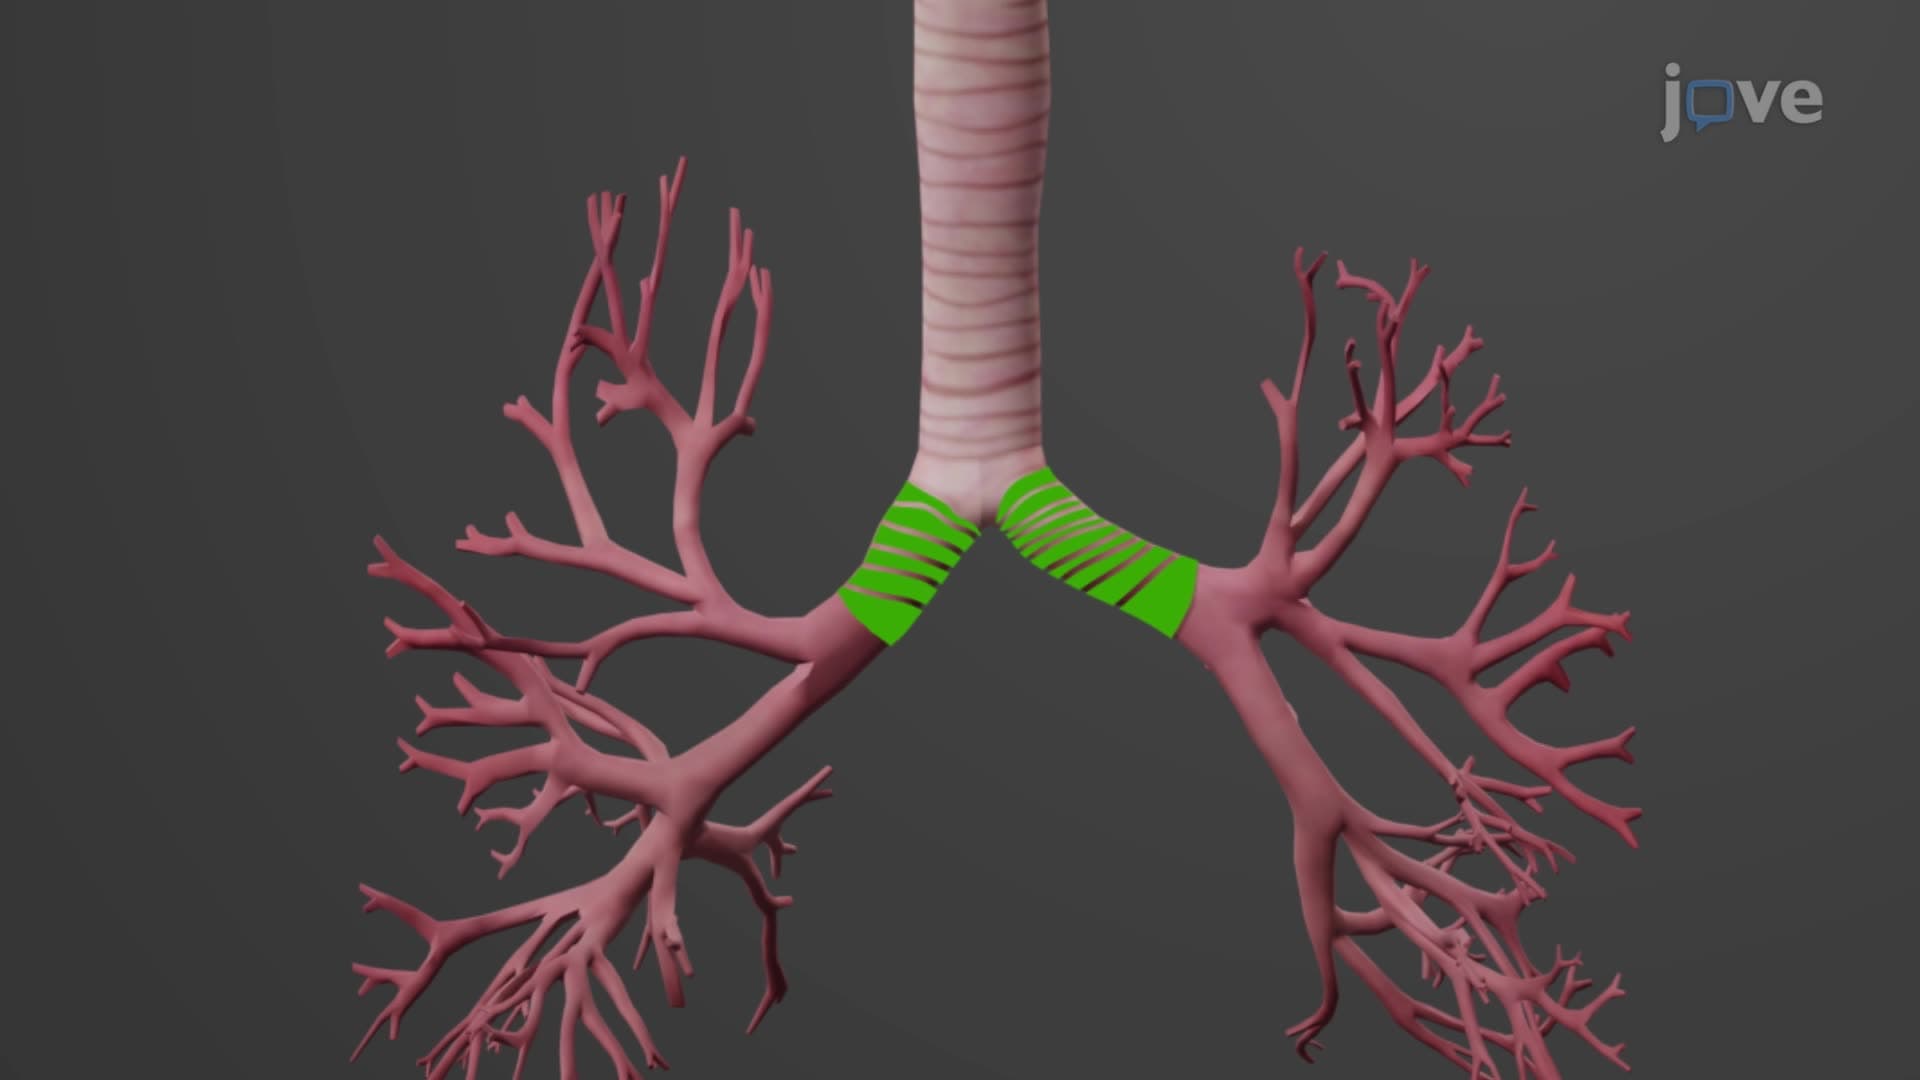 01:23
The Bronchial Tree
The trachea, commonly known as the windpipe, is a tube that connects the larynx (voice box) to the bronchi. At a point called the carina, it bifurcates into two primary bronchi. The right primary bronchus is wider, shorter, and more vertical than the left primary...