Related Experiment Video
Updated: Jun 22, 2026
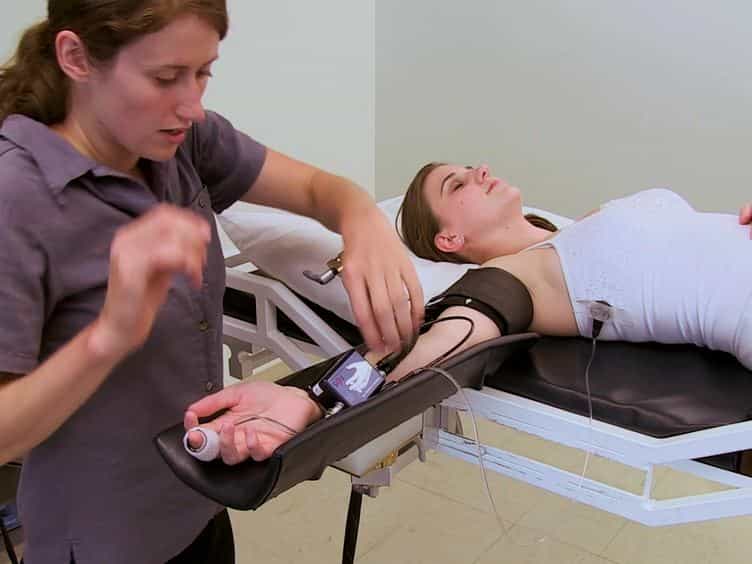

Tilt Testing with Combined Lower Body Negative Pressure: a "Gold Standard" for Measuring Orthostatic Tolerance
Published on: March 21, 2013
Initial orthostatic hypotension is unrelated to orthostatic tolerance in healthy young subjects
Kate N Thomas1, James D Cotter, Sean D Galvin
1Department of Physiology, School of Physical Education, University of Otago, Dunedin, New Zealand.

Abstract:
The physiological challenge of standing upright is evidenced by temporary symptoms of light-headedness, dizziness, and nausea. It is not known, however, if initial orthostatic hypotension (IOH) and related symptoms associated with standing are related to the occurrence of syncope. Since IOH reflects immediate and temporary adjustments compared with the sustained adjustments during orthostatic stress, we anticipated that the severity of IOH would be unrelated to syncope. Following a standardized period of supine rest, healthy volunteers [n=46; 25+/-5 yr old (mean+/-SD)] were instructed to stand upright for 3 min, followed by 60 degrees head-up tilt with lower-body negative pressure in 5-min increments of -10 mmHg, until presyncope. Beat-to-beat blood pressure (radial arterial or Finometer), middle cerebral artery blood velocity (MCAv), end-tidal PCO2, and cerebral oxygenation (near-infrared spectroscopy) were recorded continuously. At presyncope, although the reductions in mean arterial pressure, MCAv, and cerebral oxygenation were similar to those during IOH (40+/-11 vs. 43+/-12%; 36+/-18 vs. 35+/-13%; and 6+/-5 vs. 4+/-2%, respectively), the reduction in end-tidal CO2 was greater (-7+/-6 vs. -4+/-3 mmHg) and was related to the decline in MCAv (R2=0.4; P<0.05). While MCAv pulsatility was elevated with IOH, it was reduced at presyncope (P<0.05). The cardiorespiratory and cerebrovascular changes during IOH were unrelated to those at presyncope, and interestingly, there was no relationship between the hemodynamic changes and the incidence of subjective symptoms in either scenario. During IOH, the transient nature of physiological changes can be well tolerated; however, potentially mediated by a reduced MCAv pulsatility and greater degree of hypocapnic-induced cerebral vasoconstriction, when comparable changes are sustained, the development of syncope is imminent.

Related Concept Videos
 01:30
Alterations in Blood Pressure
Hypertension (High blood pressure)
Hypertension occurs when blood pressure readings consistently exceed the normal range. It is diagnosed when systolic blood pressure (the top number, indicating pressure while the heart beats)...
 01:18
Disorders of the Autonomic Nervous System
Raynaud's disease, also known as Raynaud's phenomenon, is a...
 01:24
Blood Pressure Imbalances and Circulatory Shock
Blood Pressure: Hypertension and Hypotension
Normal blood pressure is 120/80 mm Hg. Elevated blood pressure is 120-129/under 80 mm Hg. Hypertension, warranting treatment at 130/80 mm Hg, is often asymptomatic and can lead to severe cardiovascular events, aneurysms, peripheral arterial disease, chronic renal disease, or cardiac...
 01:18
Hypertension and Regulation of Blood Pressure
 01:17
Measurement of Blood Pressure
 01:29
Hypertension II: Pathophysiology