Related Experiment Video
Updated: Jun 22, 2026
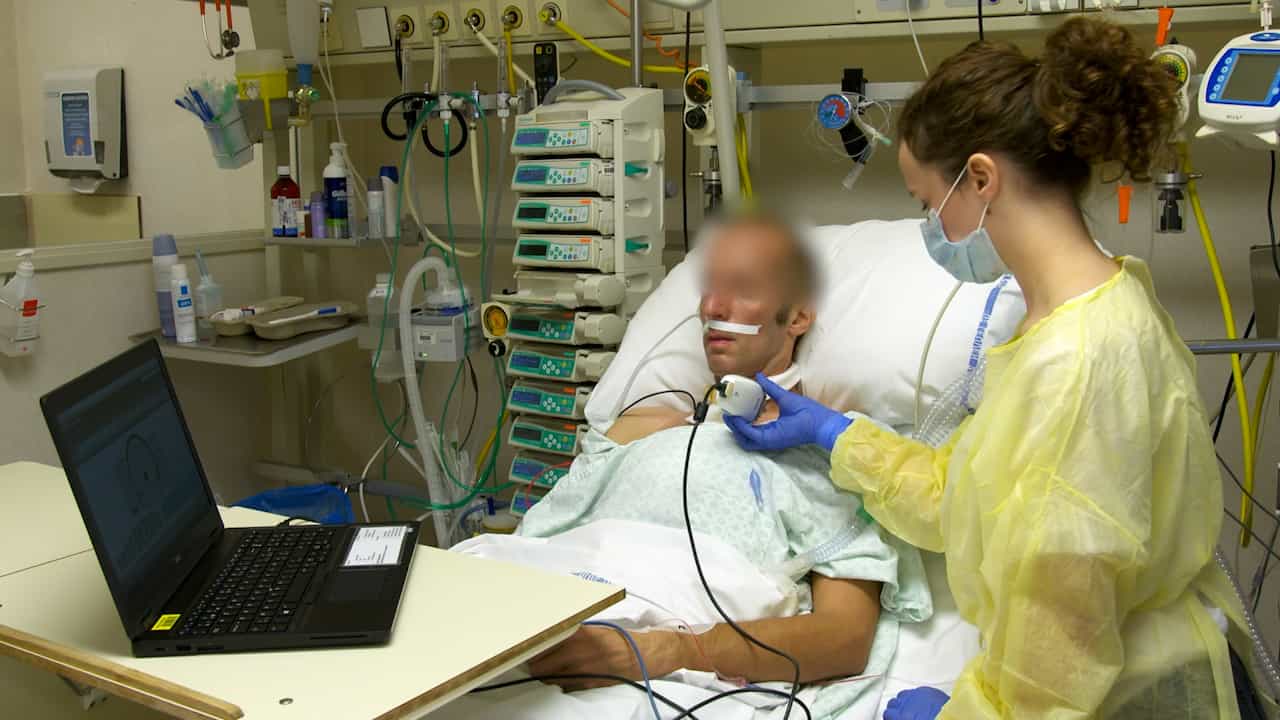

Inspiratory Muscle Training as an Adjunct to the Treatment of Weaning Failure in Critically Ill Patients: A Practical Guide
Published on: January 30, 2026
Determinants of weaning success in patients with prolonged mechanical ventilation
Annalisa Carlucci1, Piero Ceriana, Georgios Prinianakis
1Respiratory Intensive Care Unit, Fondazione S, Maugeri, IRCCS, Pavia 27100, Italy. annalisa.carlucci@fsm.it

Introduction:
Physiological determinants of weaning success and failure are usually studied in ventilator-supported patients, comparing those who failed a trial of spontaneous breathing with those who tolerated such a trial and were successfully extubated. A major limitation of these studies was that the two groups may be not comparable concerning the severity of the underlying disease and the presence of comorbidities. In this physiological study, we assessed the determinants of weaning success in patients acting as their own control, once they are eventually liberated from the ventilator.
Methods:
In 30 stable tracheotomised ventilator-dependent patients admitted to a weaning center inside a respiratory intensive care unit, we recorded the breathing pattern, respiratory mechanics, inspiratory muscle function, and tension-time index of diaphragm (TTdi = Pdisw/Pdimax [that is, tidal transdiaphragmatic pressure over maximum transdiaphragmatic pressure] x Ti/Ttot [that is, the inspiratory time over the total breath duration]) at the time of weaning failure (T0). The measurements were repeated in all the patients (T1) either during a successful weaning trial (successful weaning [SW] group, n = 16) or 5 weeks later, in the case of repeated weaning failure (failed weaning [FW] group, n = 14).
Results:
Compared to T0, in the FW group at T1, significant differences were observed only for a reduction in spontaneous breathing frequency and in TTdi (0.21 +/- 0.122 versus 0.14 +/- 0.054, P = 0.008). SW patients showed a significant increase in Pdimax (34.9 +/- 18.9 cm H2O versus 43.0 +/- 20.0, P = 0.02) and decrease in Pdisw/Pdimax (36.0% +/- 15.8% versus 23.1% +/- 7.9%, P = 0.004).
Conclusions:
The recovery of an inadequate inspiratory muscle force could be the major determinant of 'late' weaning success, since this allows the patients to breathe far below the diaphragm fatigue threshold.

Related Concept Videos
 01:29
Mechanical Ventilation I: Indication and Settings
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation (NIPPV)
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals.
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...