Vertical mobile and reducible atlantoaxial dislocation. Clinical article
Related Experiment Video
Updated: Jun 22, 2026
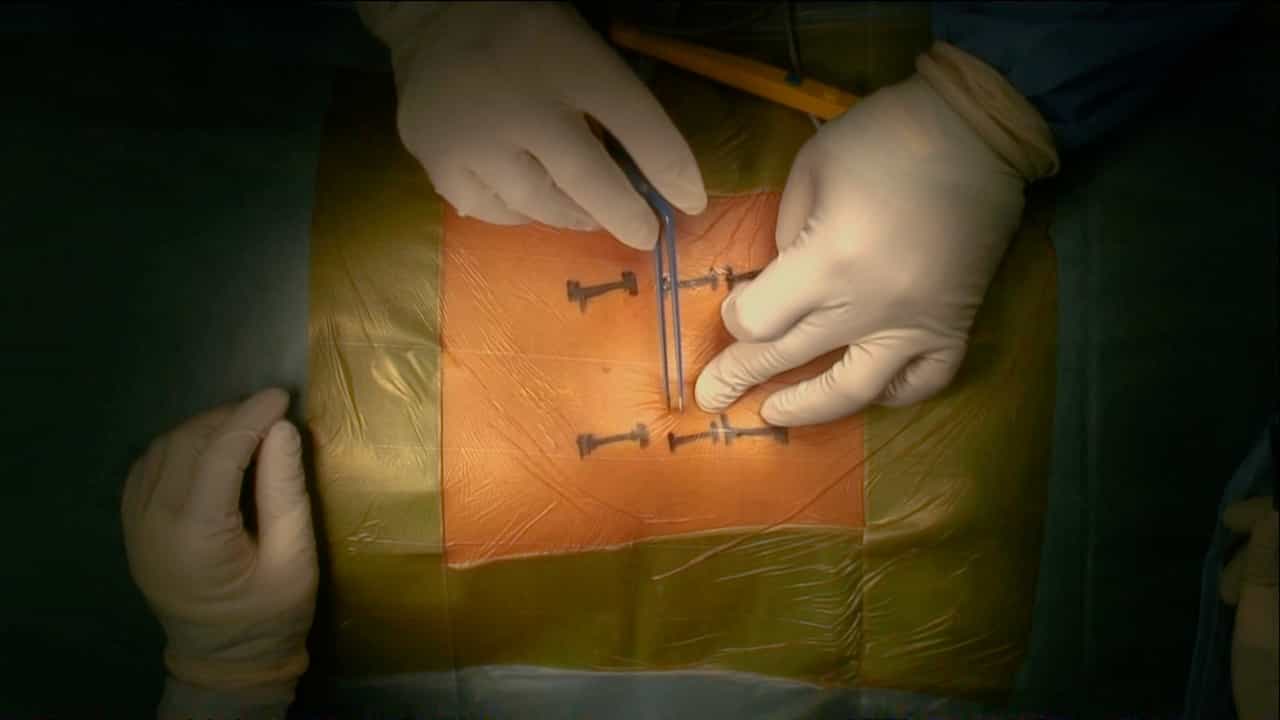
Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
Atul Goel1, Abhidha Shah, Sanjay Rajan
1Department of Neurosurgery, King Edward VII Memorial Hospital and Seth G. S. Medical College, Parel, Mumbai, India. atulgoe162@hotmail.com

Object:
The authors' experience with treatment of 8 patients with "vertical mobile and reducible" atlantoaxial dislocation is reviewed. The probable pathogenesis, radiological and clinical features, and management issues in such cases are discussed.
Methods:
Between January 2006 and March 2008, 8 patients who presented with vertical mobile and reducible atlantoaxial dislocations were treated at the Department of Neurosurgery at King Edward Memorial Hospital in Mumbai, India. The vertical atlantoaxial dislocation/basilar invagination reduced completely on extension of the neck, with no need of any cervical traction. According to the extent of superior migration of the odontoid process, and measurements based on the vertical atlantoaxial instability index, the dislocation was graded as mild, moderate, or severe. All patients were treated using the C-1 lateral mass and C-2 pars plate and screw method of fixation.
Results:
The study group was composed of 5 male and 3 female patients (mean age 24 years, age range 8-54 years). All patients presented with the physical features of short neck, torticollis, pain in the nape of the neck, and varying degrees of quadriparesis. In 6 patients there was a history of trauma prior to the onset of major neurological symptoms. The dislocation was mild in 3 cases, moderate in 1, and severe in 4. All patients had clinical neurological improvement following surgery. The follow-up duration ranged from 4 to 30 months (mean 18 months).
Conclusions:
Vertical mobile and reducible atlantoaxial dislocation is a discrete clinical entity. Abnormal inclination and incompetence of the facet joint appears to be the primary causative factor that resulted in vertical dislocation or basilar invagination. Posterior fixation in the reduced dislocation position forms the basis of treatment.
Related Concept Videos
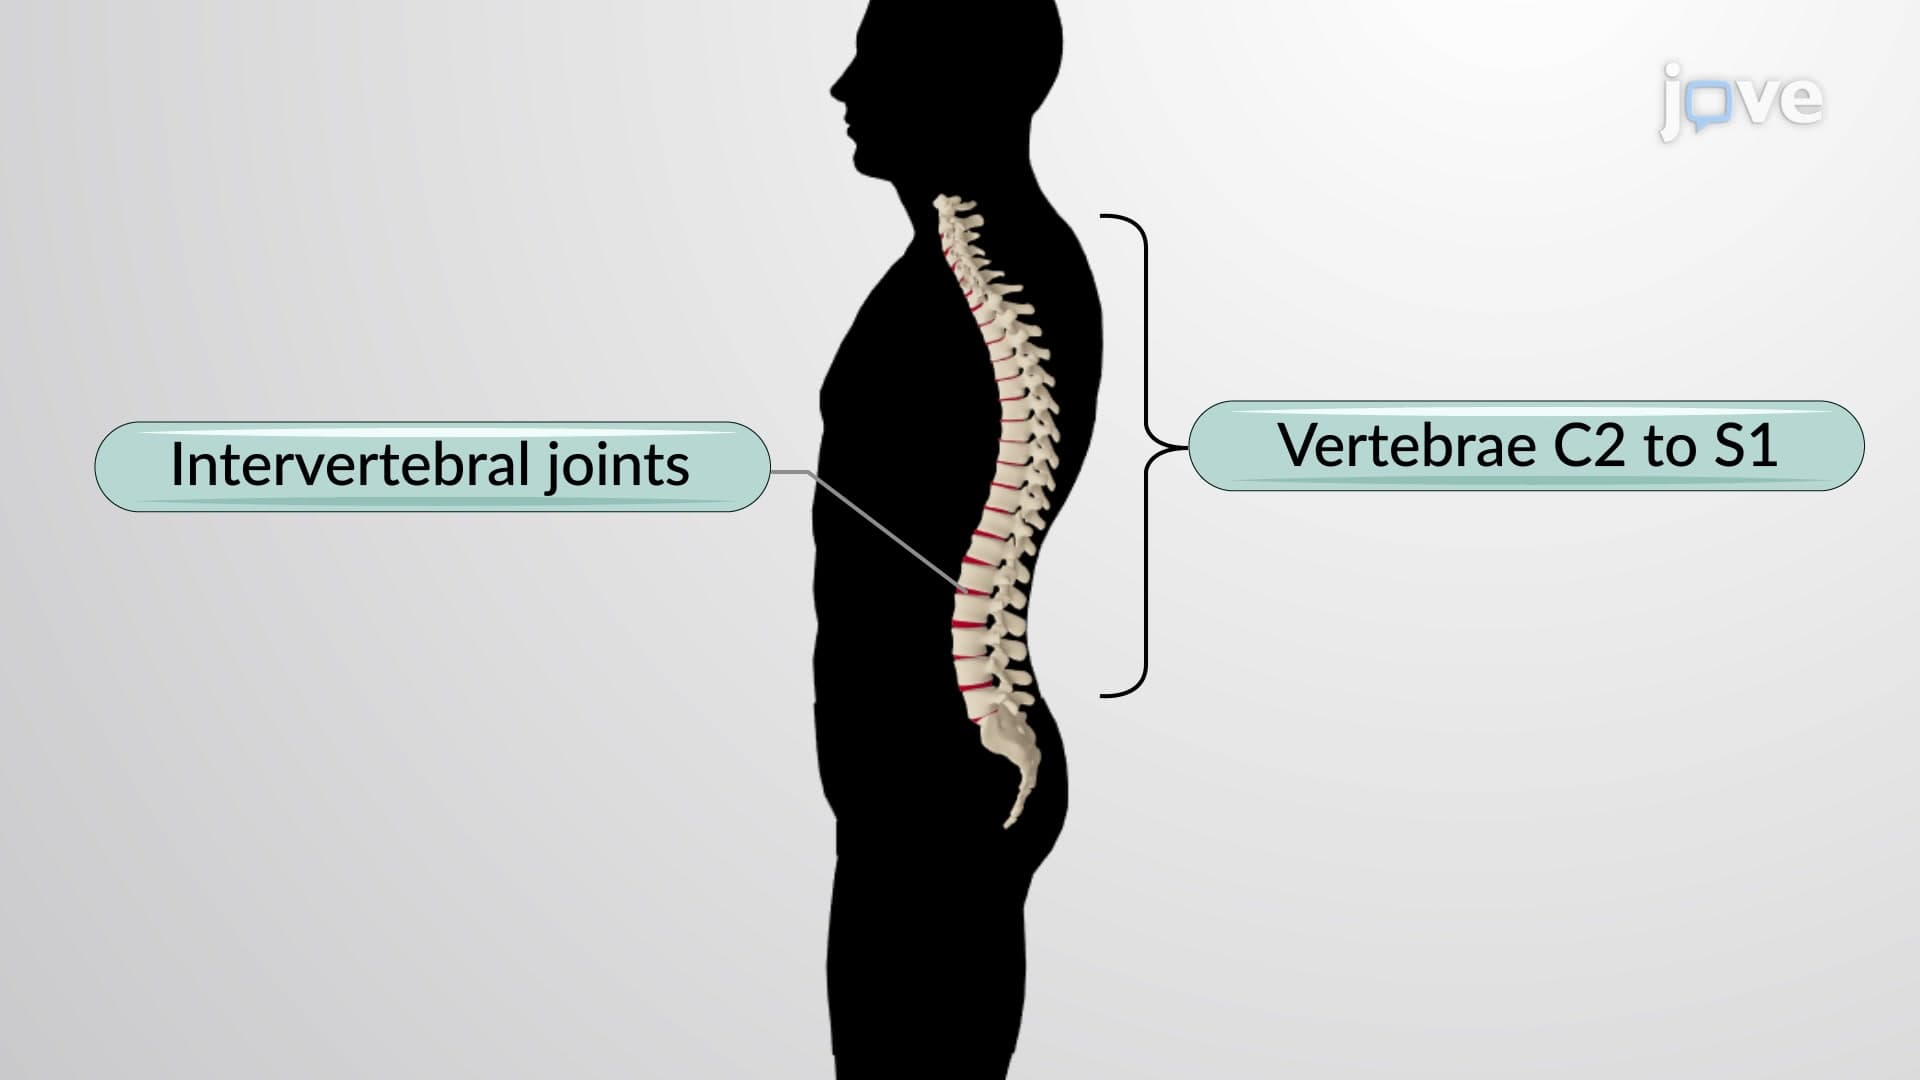 01:28
Articulations of the Vertebral Column
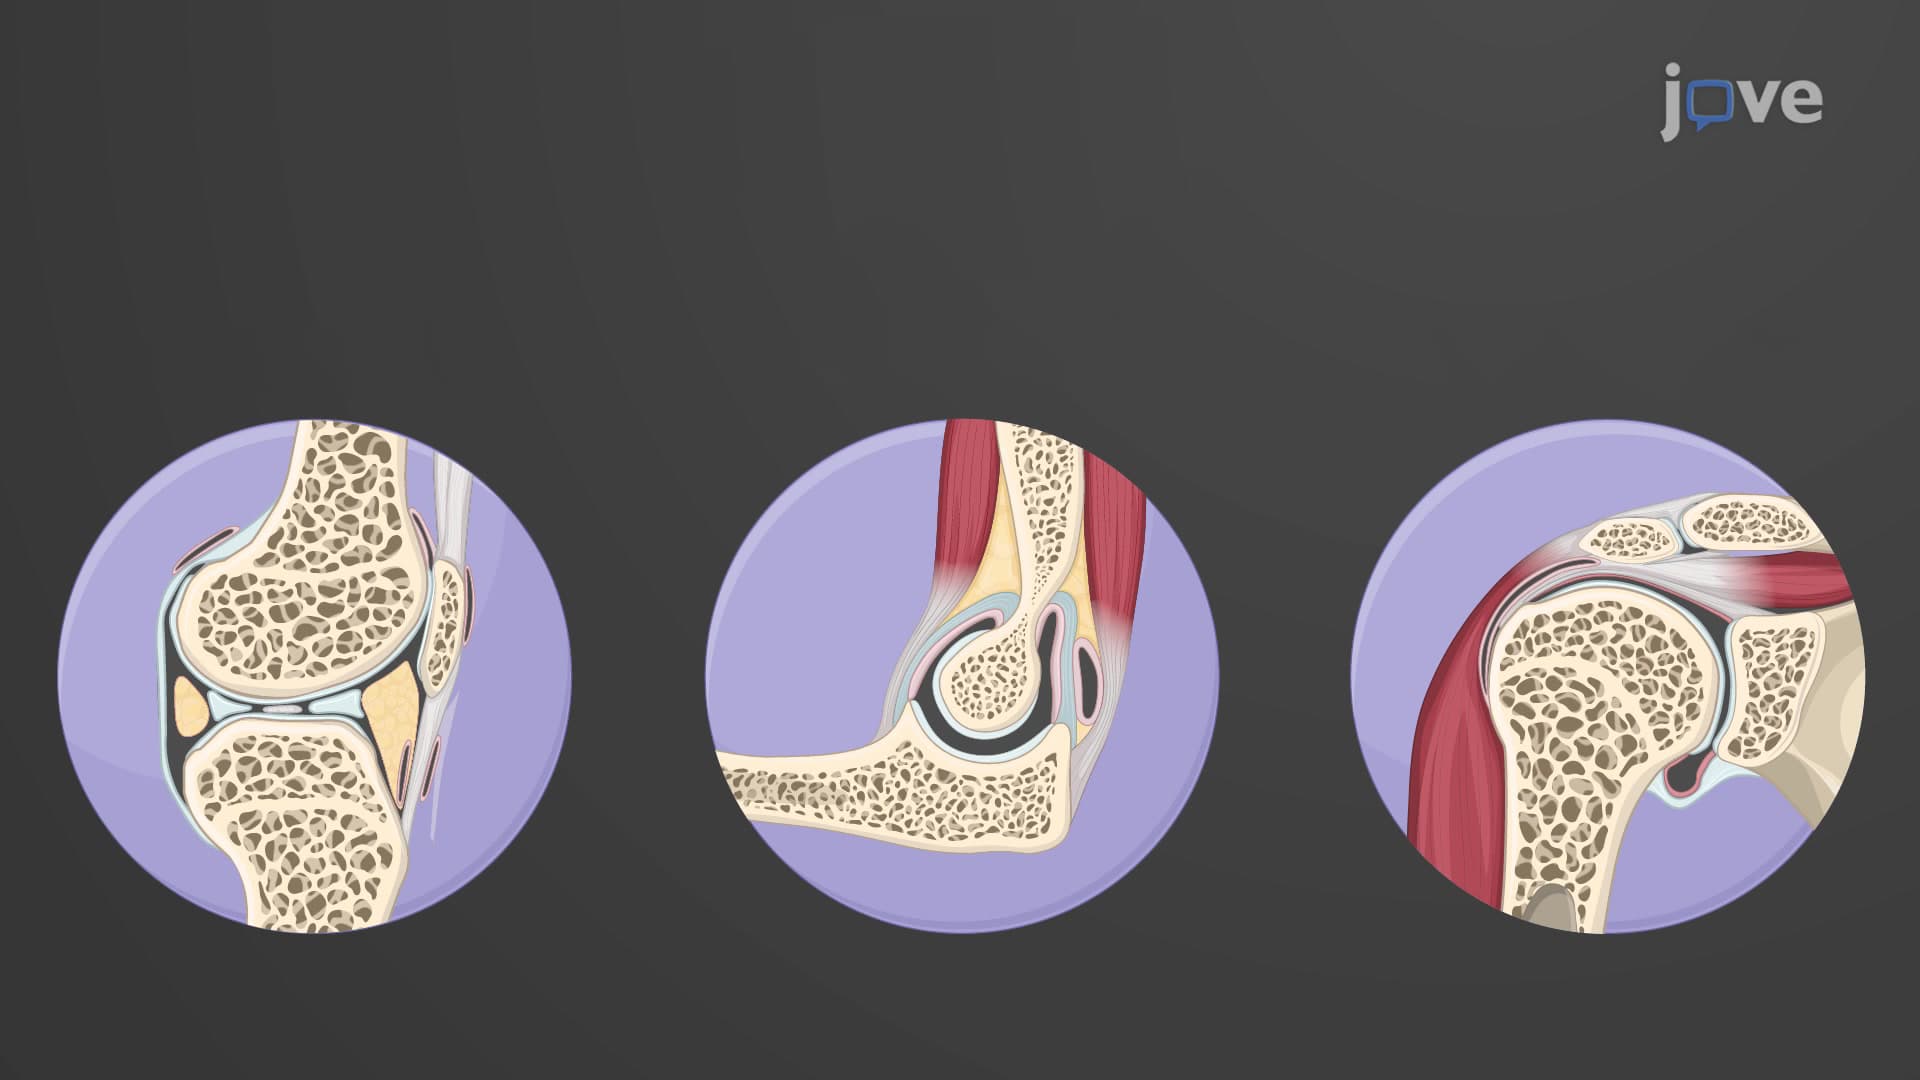 01:09
Functional Classification of Joints
The functional classification of joints is determined by the amount of mobility between the adjacent bones. Joints are functionally classified as a synarthrosis or immobile joint, an amphiarthrosis or slightly moveable joint, or as a diarthrosis, a freely moveable joint. Fibrous and cartilaginous joints can be functionally classified as either synarthroses or amphiarthroses, whereas all synovial joints are classified as diarthroses.
Synarthrosis
An immobile...