Related Experiment Video
Updated: Jun 21, 2026
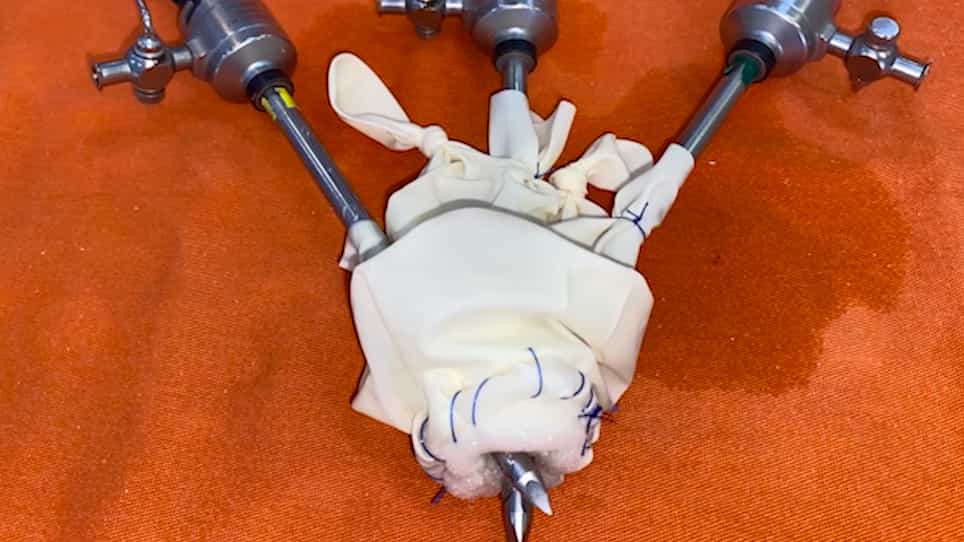

Low-Cost Single-Port (LoCoSP) Device for a Transcervical Approach in Minimally Invasive Transhiatal Esophagectomy
Published on: September 11, 2021
Transhiatal esophageal surgery for malignancy--a 7-year experience at a tertiary care hospital
Ahmad Uzair Qureshi1, Munazza Iqbal, Khalid Masud Gondal
1Department of Surgery, Mayo Hospital, Lahore. ahmed_uzairq@hotmail.com

Objective:
The aim of this study was to determine the outcomes of transhiatal esophagectomy for dysphagia for esophageal malignancy in terms of short and long-term morbidity and mortality and to determine the survival series.
Study Design:
Case series study.
Place And Duration Of Study:
South and West Surgical Ward, Mayo Hospital, Lahore, from January 2001 to December 2007.
Methodology:
All patients referred electively or admitted through OPD presenting with features of progressive dysphagia due to malignancy were included in the study. The patients were investigated for site of stricture and extent of growth into the surrounding structures. All underwent transhiatal esophagectomy and gastric tube or colon was used as the conduit to restore continuity. Patients with squamous cell variety were referred to oncology department for chemoradiotherapy postoperatively. Morbidity and in-hospital mortality were recorded.
Results:
A total of 42 patients were operated electively for malignant stricture esophagus through transhiatal approach. Site of lesion were 5 (11.9%) upper, 13 (31%) middle and 24 (58%) at lower end of esophagus. The TNM staging were stage I, IIa, IIb, III and IV in zero (0), 5 (11%), 10 (22%), 24 (57.8%) and 3 (7.1%) respectively. Mean operating time was 154 minutes and average blood loss of 371 ml. Postoperative complications included pneumothorax 16.7%, pulmonary complication (16.7%), anastomotic leakage (9.5%), wound infection (3.4%), recurrent laryngeal nerve injury (4.8%) and stricture formation (4.8%). Only 3 (7.1%) 30-day in-hospital mortality was recorded.
Conclusion:
Transhiatal esophagectomy is the surgical treatment of choice for resection of carcinoma esophagus specifically at the lower and mid-esophageal levels. The frequency of complications is lower as compared to transthoracic approach and the early stage of presentation can lead to high 5-year survival ratios.

Related Concept Videos
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure entails...
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...