Utility of the frontal plane QRS axis in identifying non-ST-elevation myocardial infarction in patients with poor R-wave progression

Laxman Prajapat1, Vignendra Ariyarajah, David H Spodick
1Department of Medicine, St. Vincent Hospital, University of Massachusetts, Worcester, MA, USA.

Abstract:
Poor R-wave progression (PRWP) is a common electrocardiographic phenomenon in which the anticipated increase in R-wave amplitude in successive precordial leads, V(1) to V(5), fails to occur. PRWP is prevalent in approximately 10% of hospitalized adult patients, predominantly in those with coronary artery disease. Debate is ongoing on its association with myocardial infarction (MI). However, studies that showed no association failed to appraise the significance of the QRS axis in relation to PRWP among such patients with MI. In our retrospective study, we consecutively identified 150 unselected adult patients with PRWP among 660 successive admissions to the general medical floors of a tertiary care teaching hospital (Saint Vincent Hospital, Worcester, Massachusetts). After excluding patients with anterior wall Q-wave MI (defined as the presence of a QS complex or Q-wave > or =1 mm deep in V(2) or V(3)), sudden unexpected death, MI after percutaneous coronary interventions or coronary artery bypass grafting during this hospitalization, Wolff-Parkinson-White syndrome, pacemakers, bundle branch blocks, and electrocardiograms that were of poor quality or affected by severe motion artifact, inconsistencies with patient identification, or errors in lead placement, 137 patients remained. The patients were then screened for non-ST-segment elevation MI (NSTEMI) during the present admission. The DePace criteria for PRWP were systematically used for all patients, and the QRS axis was calculated using limb leads based on Einthoven's equilateral triangle (normal was considered -30 degrees to 100 degrees ). Of the 137 study patients screened with PRWP, 38 had NSTEMI (25.3%). Thirty-one had a normal QRS axis (mean age +/- standard deviation 71.3 +/- 12 years), and 7 showed either right or left axis deviation (mean age +/- standard deviation 64.3 +/- 15 years). This proved to be statistically significant (p <0.0001) within this cohort of NSTEMI patients. In conclusion, PRWP determined using the DePace criteria in the presence of a normal QRS axis appears to be more significantly associated with the presence of overall MI within this cohort of NSTEMI patients.

Related Concept Videos
 01:29
Electrocardiogram
Three major waveforms are present in a typical ECG recording: the P wave, the QRS complex, and the T...
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:28
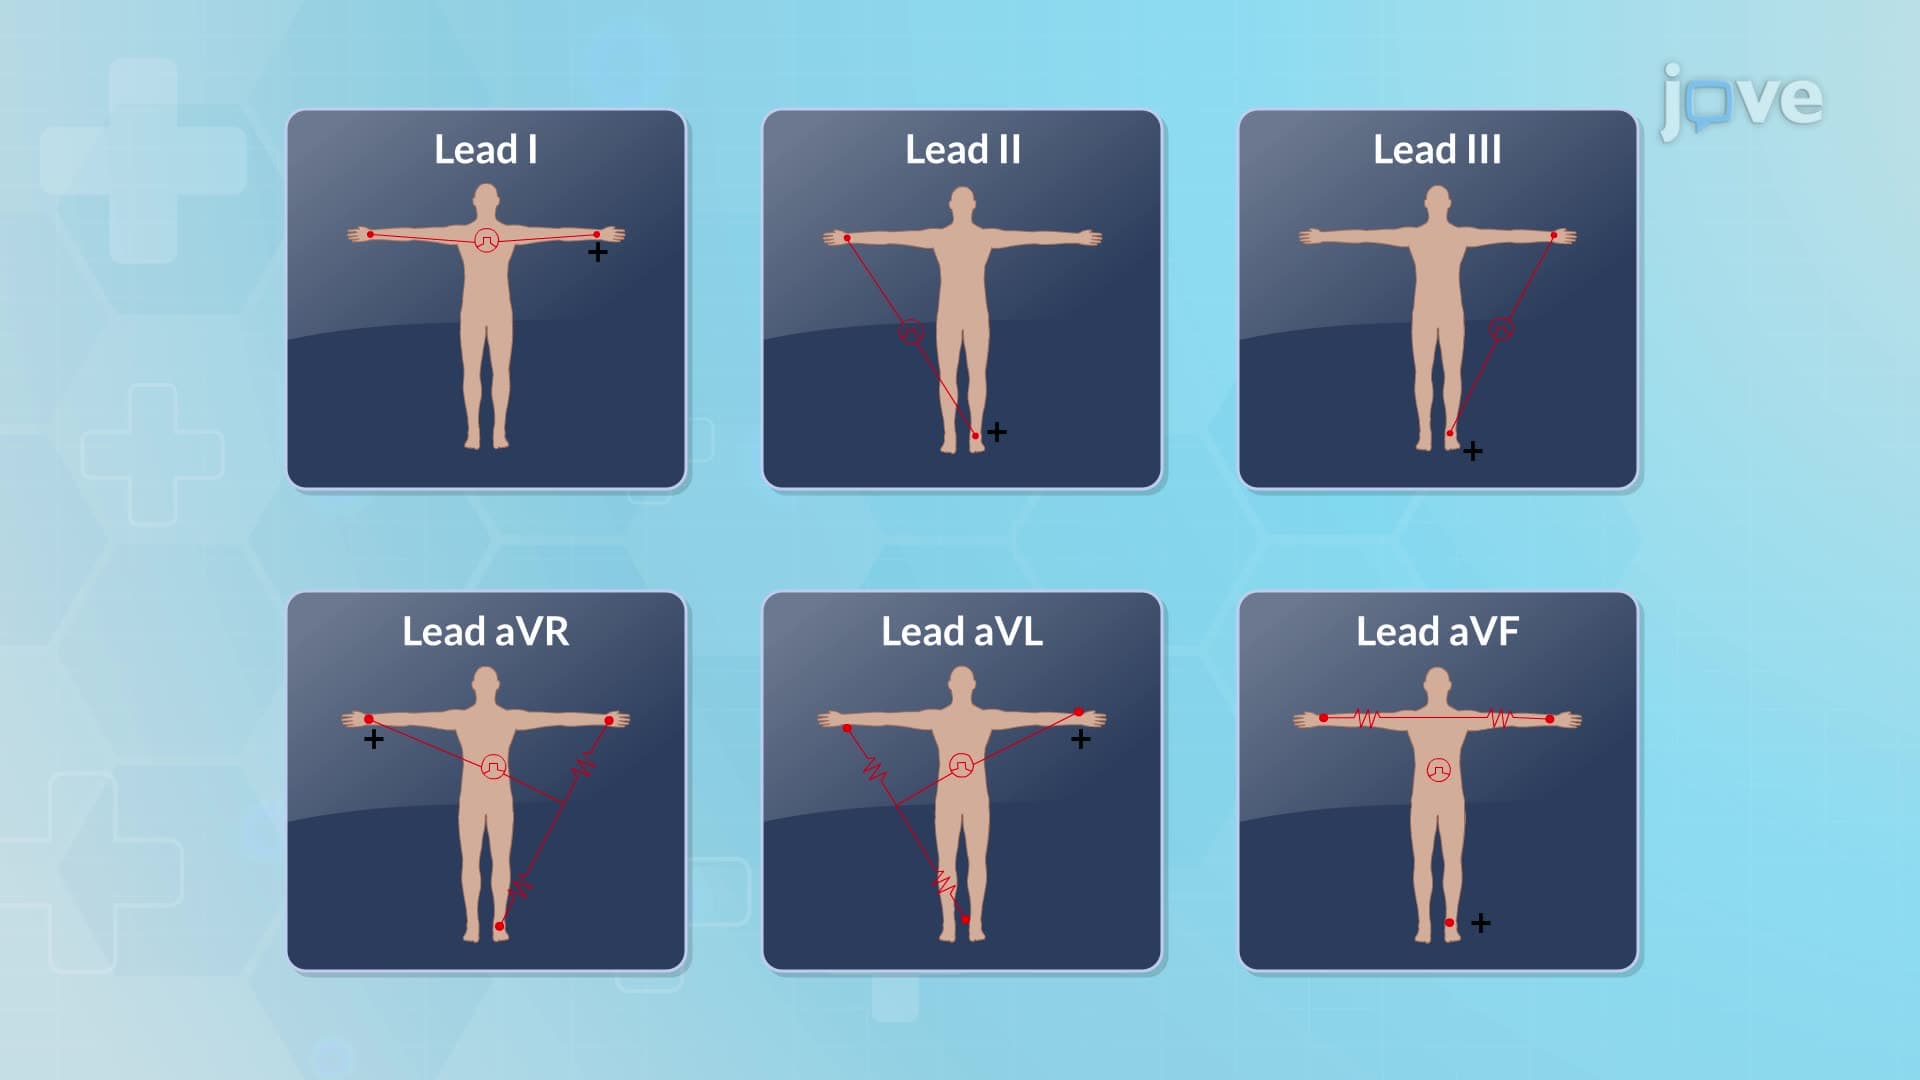
Electrocardiogram Fundamentals
An electrocardiogram (ECG) is a diagnostic tool for identifying cardiac conditions such as arrhythmias, conduction abnormalities, and myocardial ischemia.
Definition
An electrocardiogram (ECG) visualizes the heart's electrical activity by tracing the electrical movement associated with each heartbeat on a graph or monitor. As the heart beats, an electrical wave passes through it, correlating with the cardiac cycle events.
Parts of an ECG
An ECG utilizes electrodes on the skin to...
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations
 01:30
Acute Coronary Syndrome I: Introduction
 01:24
ECG Interpretation of Rhythms
Components of the Electrocardiogram
The primary components of a normal ECG waveform in Normal sinus rhythm(NSR) include the P wave, PR interval, QRS complex, ST segment, T wave, and occasionally a U wave.
ECG waveforms are divided by vertical and horizontal lines at standard intervals.
The horizontal axis measures time and rate, and the vertical axis measures amplitude or voltage. When...