Related Experiment Video
Updated: Jun 21, 2026
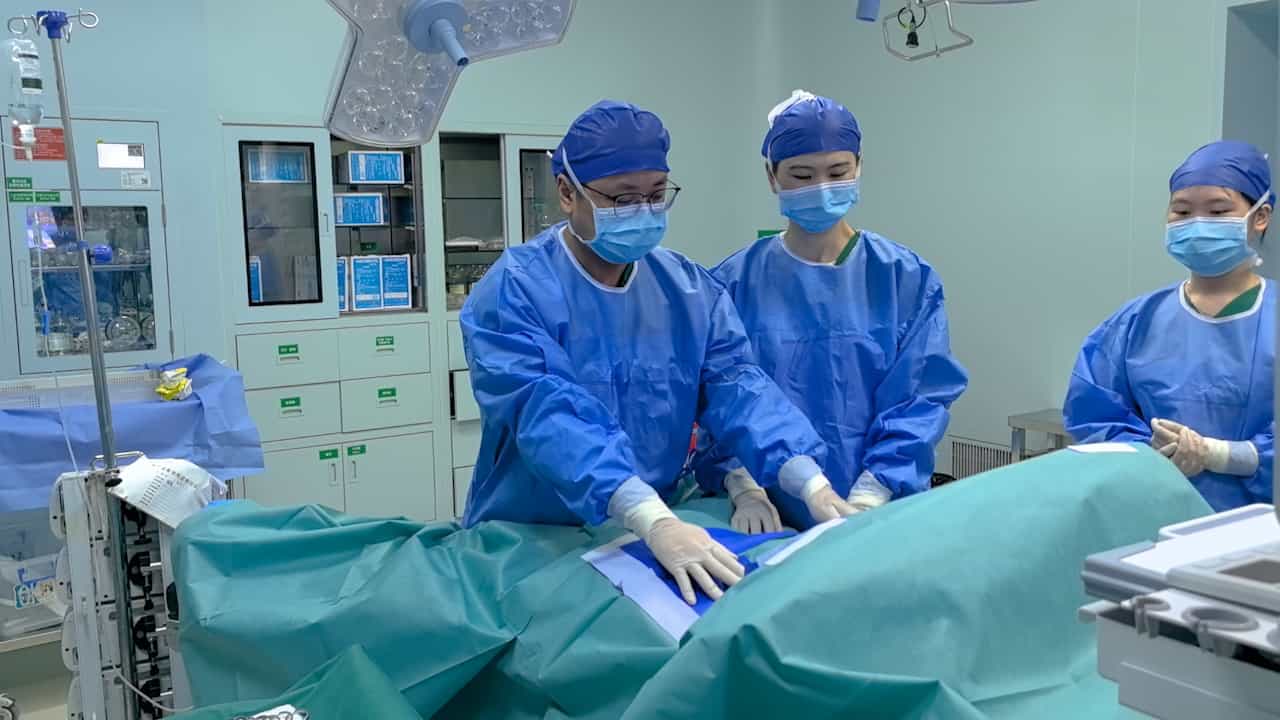

"Sun's Seven-Step Technique" for Endoscopic En-Bloc Resection of Thyroid Cancer via the Chest-Breast Approach
Published on: November 28, 2025
[Re-operation extent of primary lesion of thyroid cancer]
Wen-Bin Yu1, Nai-Song Zhang, Zong-Yuan Zeng
1Key Laboratory of Carcinogenesis and Translational Research of Ministry of Education, Department of Head and Neck Surgery, Peking University School of Oncology, Beijing Cancer Hospital & Institute, Beijing, 100142, P.R. China.

Background And Objective:
Many thyroid cancer patients need to receive second operation because of tumor residue. This study was to explore the resection extent of primary lesion in re-operation of thyroid carcinoma.
Methods:
Clinical data of 55 thyroid carcinoma patients who received re-operation were reviewed. The patients, including seven men and 48 women, were aged of 18-56. All patients received ipsilateral residual lobectomy, isthmectomy, ipsilateral anterior cervical muscle and level VI lymph node dissection. The optimal extent for radical re-resection of primary lesion was explored.
Results:
Tumor residue was proved by pathology in 29 patients, with a rate of 52.73%. Of the 29 patients, eight had primary lesion residue, seven had level VI lymph node residue, and 14 had both. Tumor cells were connected with muscle in four patients. Forty-five metastatic lymph nodes were found.
Conclusion:
Ipsilateral residual lobectomy, isthmectomy, ipsilateral anterior cervical muscle and level VI lymph node dissection is the basic re-resection extent of primary lesion for thyroid carcinoma patients.
Related Concept Videos
 01:23
The Thyroid Gland
The follicles have a central cavity lined by simple cuboidal to squamous epithelial cells called follicular cells. These cells produce the glycoprotein...
 01:25
Hyperthyroidism I: Introduction
 01:27
Hyperthyroidism II: Pathophysiology