Related Experiment Video
Updated: Jun 21, 2026


Homogeneous Time-resolved Förster Resonance Energy Transfer-based Assay for Detection of Insulin Secretion
Published on: May 10, 2018
Utility of early insulin response and proinsulin to assess insulin resistance
Amy M Jean1, Abeer Hassoun, Jennifer Hughes
1Department of Pediatrics, Division of Pediatric Endocrinology, Columbia University, New York, NY 10032, USA.

Insights
Obese children with premature adrenarche exhibit higher early insulin response (EIR) and proinsulin (PI) levels, indicating an increased risk for prediabetes and type 2 diabetes. This highlights the additive impact of obesity and premature adrenarche on metabolic health.
Area of Science:
- Pediatric Endocrinology
- Metabolic Health
- Diabetes Research
Background:
- Premature adrenarche and obesity are independently associated with metabolic dysfunction.
- Understanding their combined effects is crucial for early risk assessment in children.
Purpose of the Study:
- To investigate if obesity and premature adrenarche act additively to increase the risk of insulin resistance and beta-cell dysfunction.
- To utilize early insulin response (EIR) and proinsulin (PI) as key markers.
Main Methods:
- Prospective case-control study of 81 prepubertal children.
- Categorization into lean controls, obese controls, lean premature adrenarche, and obese premature adrenarche groups.
- Assessment of fasting glucose, insulin, proinsulin, and oral glucose tolerance tests to calculate EIR.
Main Results:
- Obese children, with or without premature adrenarche, showed significantly higher EIR.
- The obese premature adrenarche group exhibited the highest EIR and elevated fasting PI levels compared to lean counterparts.
- No significant difference was found in the fasting PI/I ratio across groups.
Conclusions:
- Obese children with premature adrenarche demonstrate a heightened risk for developing prediabetes and type 2 diabetes mellitus.
- EIR and PI serve as valuable indicators for assessing metabolic risk in this pediatric population.
- Early identification and intervention are critical for mitigating long-term metabolic complications.
Objective:
To determine whether obesity and premature adrenarche are additive events increasing the risk of insulin resistance and beta-cell failure, using early insulin response (EIR) or the insulinogenic index and proinsulin (PI) as markers.
Study Design:
This was a prospective case-control study conducted at a tertiary care academic medical center involving 81 prepubertal, predominantly Hispanic children (34 males, 47 females), classified as lean controls (4 males, 6 females; mean age, 6.5 +/- 1.2 years; mean body mass index [BMI] z-score, 0.08 +/- 0.6), obese controls (20 males, 10 females; mean age, 7.2 +/- 1.5 years; mean BMI z-score, 2.5 +/- 0.5), lean premature adrenarche (3 males, 11 females; mean age, 7.1 +/- 1.2 years; mean BMI z-score, 0.09 +/- 0.6), and obese premature adrenarche (7 males, 20 females; mean age, 7.3 +/- 1.0; mean BMI z-score, 2.2 +/- 0.4). Fasting glucose (G(0)), insulin (I(0)), PI(0), androgen levels, insulin-like growth factor 1, insulin-like growth factor binding protein 1, and lipid levels were obtained. An oral glucose tolerance test was performed. EIR was calculated as (I(30) - I(0))/(G(30) - G(0)). Between-group differences were assessed by 2-way analysis of variance, with interactions and associations explored with correlation/regression.
Results:
EIR was greater in the obese subjects with and without premature adrenarche. Combined analysis of the independent variables obesity and premature adrenarche showed that the obese premature adrenarche group had the highest EIR. The obese subjects with premature adrenarche had greater fasting PI levels than their lean counterparts. The differences in fasting PI/I ratio among the groups were not statistically significant.
Conclusions:
Using EIR and PI as markers to assess the risk of insulin resistance and impaired insulin secretion indicates that obese children with premature adrenarche may be at greater risk for the development of prediabetes and type 2 diabetes mellitus compared with their lean counterparts.

Related Concept Videos
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
 01:28
Insulin: The Receptor and Signaling Pathways
 01:16
Hormones Regulating Blood Glucose
In addition to accelerating glucose uptake and utilization, insulin has...
 01:25
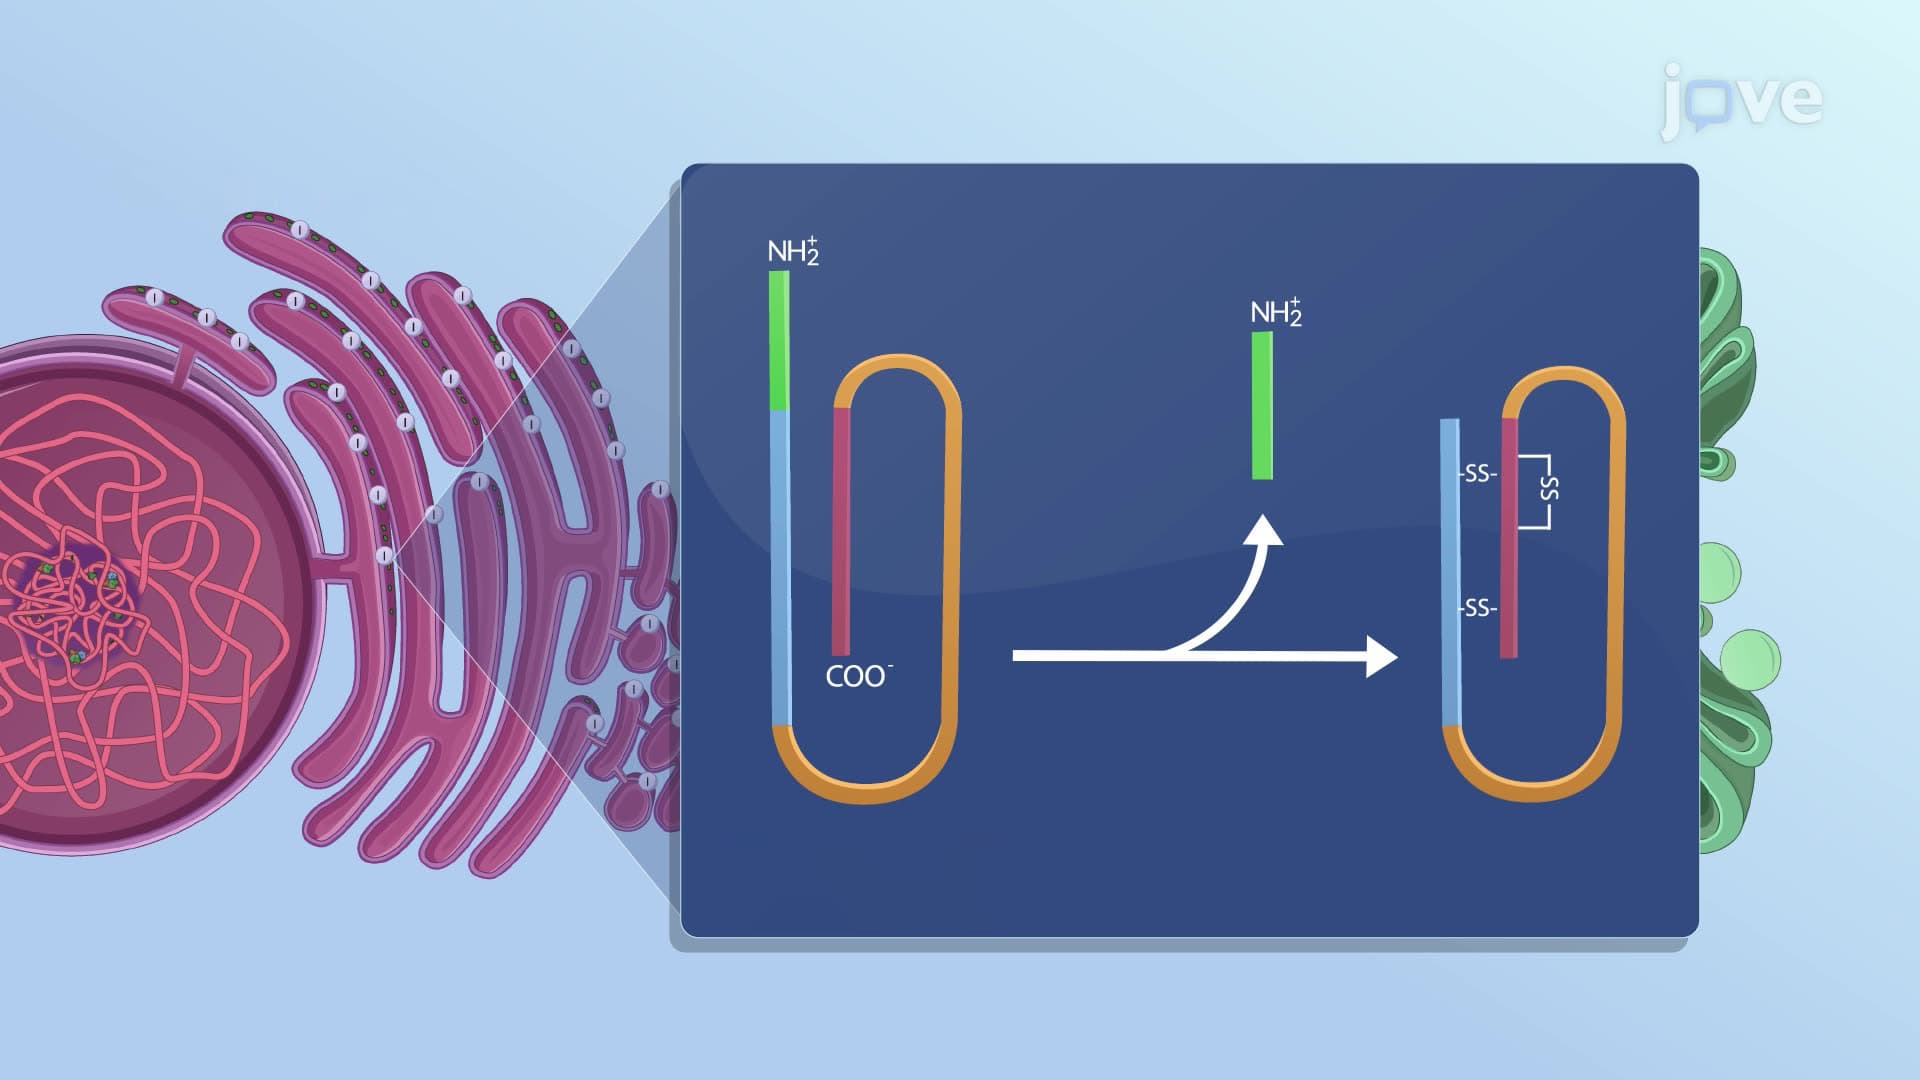
Insulin: Biosynthesis, Chemistry, and Preparation
Damage or functional impairment of β-cells inhibits insulin production, leading to diabetes. Diabetes treatment primarily uses...
 01:24
Type II Diabetes II: Pathophysiology
 01:29
Hyperglycemia