Related Experiment Video
Updated: Aug 6, 2026


A RAPID Method for Blood Processing to Increase the Yield of Plasma Peptide Levels in Human Blood
Published on: April 28, 2016
[Plasma pharmacokinetics of roxatidine in the healthy man: correlation with gastric antisecretory effect]

Abstract:
Inhibitory effects of roxatidine acetate upon human gastric secretion have been shown to be dose-related after oral administration. In order to correlate this effect with drug pharmacokinetics, blood concentration of the active metabolite, roxatidine, was assessed in 10 healthy volunteers, each receiving in random order 75, 150, 300, 600 mg of roxatidine acetate and placebo. Blood was drawn for roxatidine measurement at T 0 (time of drug intake) T 75, 90, 120, 150, 210, 240 and 300 min. Meal-induced gastric secretion was studied by intragastric titration (IGT) at 15 min intervals, from T 150 to T 240. Mean peak of blood concentration occurred at T 150 with significant correlation with the administered dosage. Gastric secretion inhibition over the 90 min of IGT correlated with peak concentration exclusively for the subpopulation with peak occurrence at T 150. Beyond the peak, decrease in roxatidine concentrations was slow, as expected from a known 6-h half-life. However, overall results showed that mean blood concentration was correlated with gastric secretion inhibition from T 180 on. The last IGT sample also correlated with the peak. Interpretation of these results would be different whether roxatidine concentration variations are appreciated as exhibiting a significant decrease or not. Infusion studies of roxatidine would be a valuable technique for further analysis and comparison of blood-concentration/efficacy relationships as compared with other H2-antagonists.
More Related Videos

Related Concept Videos
 01:14
Time Course of Drug Effect
 01:28
Acid Suppressive Drugs for Peptic Ulcer Disease: Histamine H2-Receptor Antagonists
 01:18
Pharmacokinetics in Geriatric Patients: Effect of Age on Drug Metabolism
 01:08
Effect of Hepatic Disease on Pharmacokinetics: Dose Adjustments Due to Hepatic Impairment
 01:14
Pharmacokinetic–Pharmacodynamic Relationship: Duration of Dose-Effect Relationship
 01:24
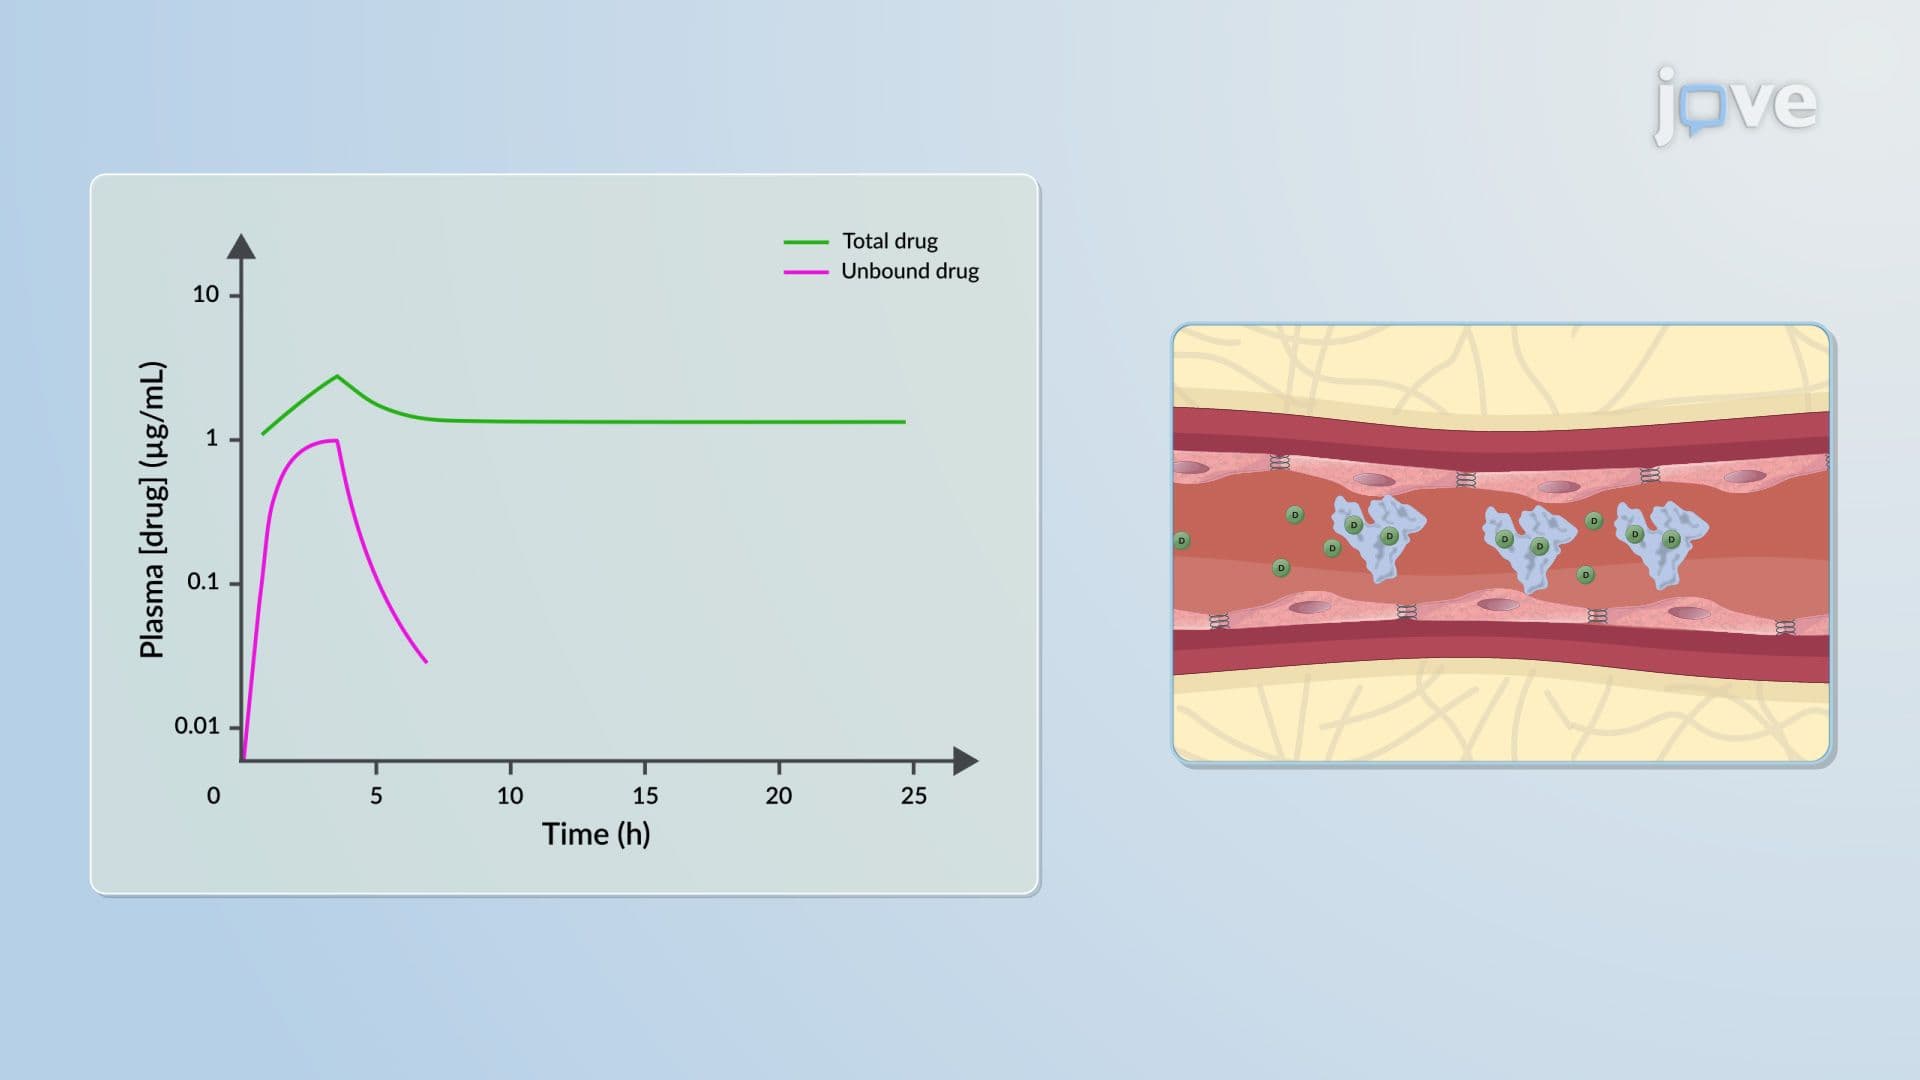
Pharmacokinetic–Pharmacodynamic Relationship: Problems