Related Experiment Video
Updated: Jun 20, 2026


A Clinical Trial Assessing the Safety, Efficacy, and Delivery of Olive-Oil-Based Three-Chamber Bags for Parenteral Nutrition
Published on: September 20, 2019
Fibre content of enteral feeds for the older child
1Dietetic Department, Birmingham Children's Hospital, Birmingham, UK. evanss21@onetel.com

Insights
Adding fibre to enteral feeds for children aged 7-12 years may improve gastrointestinal symptoms like constipation and abdominal pain. Most children still did not meet recommended fibre intake, suggesting higher levels are needed in pediatric enteral nutrition.
Area of Science:
- Pediatric Nutrition
- Gastroenterology
- Clinical Dietetics
Background:
- Lack of clinical data on fibre requirements in UK children.
- Uncertainty regarding optimal fibre profile for pediatric enteral formulae.
- Need to investigate fibre supplementation in high-energy enteral feeds for older children.
Purpose of the Study:
- To investigate the effect of fibre supplementation on gastrointestinal function in children aged 7-12 years receiving enteral feeds.
- To assess anthropometry, blood biochemistry, stool characteristics, tolerance, and oral dietary intake.
Main Methods:
- Double-blind randomised crossover study involving 25 enterally tube-fed children.
- Children received a 1.5 kcal mL(-1) formula with or without added dietary fibre (1.13 g per 100 mL) for 6 weeks each.
- Comprehensive assessments included anthropometry, blood tests, stool characteristics, tolerance, and oral intake.
Main Results:
- Higher median fibre intake (84% vs. 26% of recommended intake) with fibre-containing formula, yet most children remained below international recommendations.
- Evidence of reduced constipation, laxative reliance, and abdominal pain with fibre supplementation.
- Small feed volumes (median 800 mL day(-1)) contributed to suboptimal fibre intake.
Conclusions:
- Fibre-containing enteral formulae should be standard practice for most children on enteral feeds due to poor intake and lack of adverse effects.
- Current enteral formulae likely require higher fibre levels for older children.
- Larger trials are needed to determine optimal fibre amount and blend for pediatric enteral nutrition.
Background:
There is currently a lack of clinical data on fibre requirements in UK children. Subsequently, the ideal fibre profile for enteral formulae designed to meet the requirements of older children is unknown. The present study aimed to investigate the effect of fibre supplementation on gastrointestinal function of children aged 7-12 years (or weight 21-45 kg) receiving an age-specific high-energy enteral feed.
Methods:
In this double-blind randomised crossover study, 25 home enterally tube-fed children with a range of medical conditions (including cystic fibrosis, neurological conditions, liver transplant and bone marrow transplant) were given a 1.5 kcal mL(-1) formula with or without added dietary fibre (1.13 g per 100 mL). Each formula was taken for 6 weeks, followed by 6 months on the second randomly assigned formula. Anthropometry, blood biochemistry, stool characteristics, tolerance and oral dietary intake were assessed.
Results:
Despite a higher median fibre intake on the fibre-containing formula (84% versus 26% of recommended intake; P = 0.003), most children did not meet existing international recommendations for fibre as a result of small feed volumes (median 800 mL day(-1); 9 g fibre day(-1)). There was some evidence of reduced constipation, laxative reliance and abdominal pain on the fibre-containing formula.
Conclusions:
Given the poor fibre intakes and absence of adverse effects, the use of fibre-containing formulae should become standard practice for the majority of children on enteral feeds. Larger trials in children are required to further evaluate the effect of amount and blend of fibre in enteral formulae for older children. However, it is likely that current formulae require higher levels of fibre.
Related Concept Videos
 01:15
Enteral Nutrition II: Nasointestinal and Gastrostomy Feeding
Nasointestinal Feeding
Nasointestinal feeding involves placing a tube through...
 01:26
Enteral Nutrition I: Orogastric and Nasogastric Feeding
Orogastric (OG) and nasogastric (NG) feeding are two standard methods used for enteral nutrition. Enteral nutrition is often preferred over...
 01:18
Routes of Drug Administration: Enteral
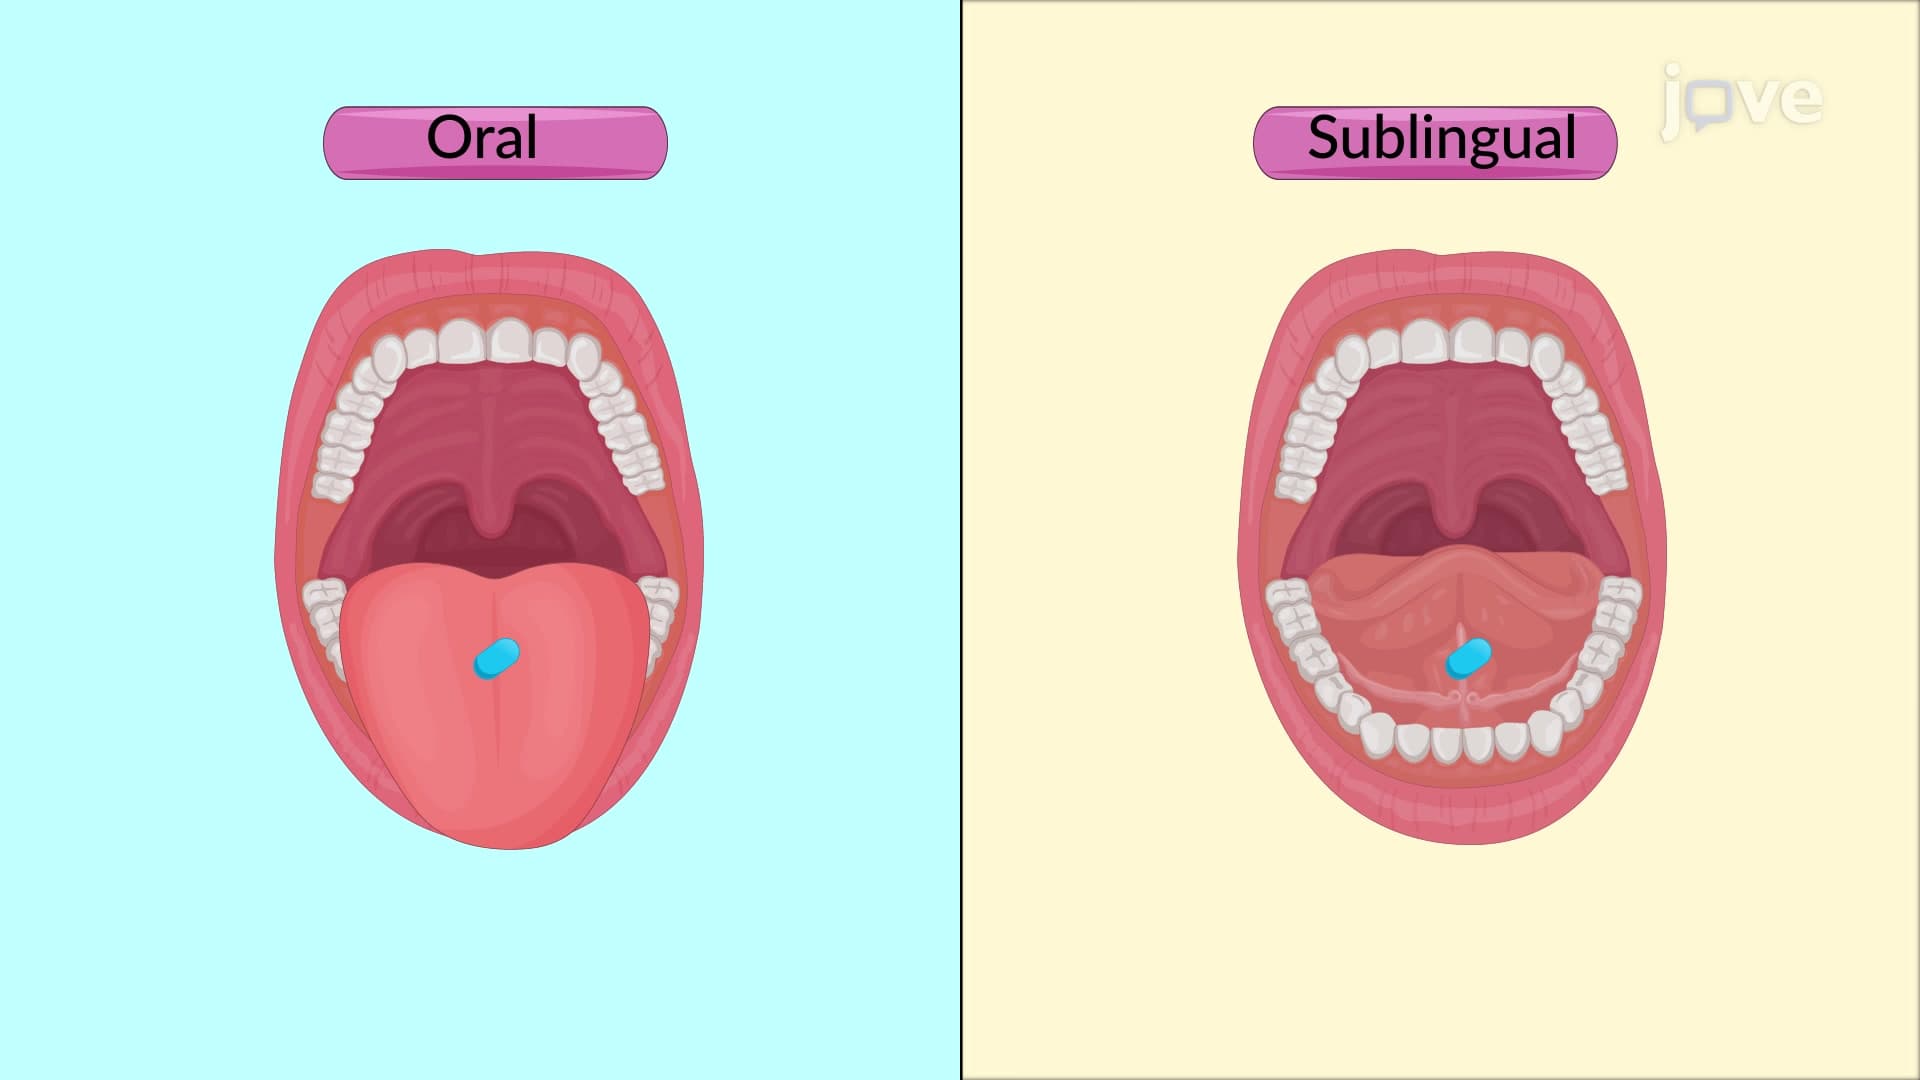
Enteral administration involves drug administration via the mouth in two ways: orally or sublingually.
Unlike sublingually drugs, drugs that are taken orally pass through the gastrointestinal (GI) tract and get metabolized by the liver. Once metabolized, the drug is absorbed into the systemic circulation, reaching different body parts via the bloodstream. However, while passing through the stomach,...
 01:18
Drug Delivery: Enteral Route
Drugs in...
 01:19
The Effect of Aging on Tissues
 01:23
Renewal of Intestinal Stem Cells