Related Experiment Video
Updated: Jun 20, 2026

Treatment with Locking Intramedullary Nailing for Intertrochanteric Fracture of the Femur Utilizing a New Awl with a Distal Positioner
Published on: June 6, 2025
[Angle-stable intramedullary nailing of proximal humerus fractures with the PHN (proximal humeral nail)]
Jochen Blum1, Matthias Hansen, Pol Maria Rommens
1Klinik für Unfall-, Hand- und Wiederherstellungschirurgie, Klinikum Worms - Akademisches Lehrkrankenhaus der Universität Mainz, Mainz, Germany. Jochen.blum@klinikum-worms.de

Objective:
Stable fixation of two- and three-part fractures of the proximal humerus through minimally invasive operative technique and rapid bone healing as well as restoration of original anatomy. Early functional training with the goal of restoration of former mobility and daily activities.
Indications:
Unstabile two- and three-part fractures of the proximal humerus (AO classification: 11-A2, 11-A3, 11-B1, 11-B2, 11-B3). Subcapital nonunion of the humerus. Pathologic fractures.
Contraindications:
Pediatric fractures of the proximal humerus. Fractures of the proximal humerus types 11-C2 und 11-C3 according to the AO classification. Active local infection, e.g., after former operation.
Surgical Technique:
Closed reduction. Anterior acromial incision, splitting of the deltoid muscle and the rotator cuff. Opening of the medullary canal with the awl. Nail introduction. Spiral blade introduction in cannulated technique through stab incision. Distal interlocking through aiming device, angle-stable blocking of nail and blade through end cap.
Postoperative Management:
Postoperative fixation in Gilchrist sling until 2nd postoperative day; then physiotherapy respecting fracture type and stability, local swelling, patient's age and compliance, and concomitant injuries.
Results:
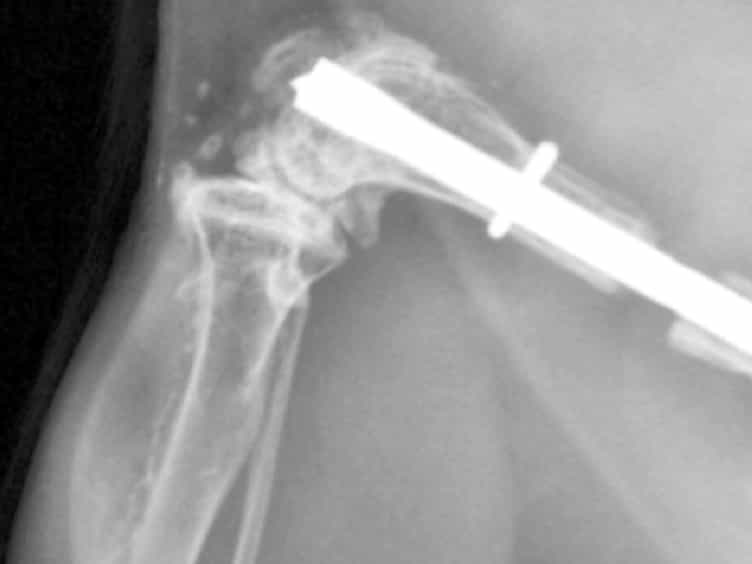
151 proximal humeral fractures were treated with a proximal humeral nail (PHN). 108 patients could be followed up 1 year postoperatively. Significant complications were perforation of the articular surface through bolts or blades (n = 8), implant-related pain (n = 10), fragment dislocation (n = 2), nonunion (n = 2), humeral head necrosis (n = 3), and superficial infection (n = 1). 1 year after the operation, the Constant-Murley Score showed a median value of 75.3 in the injured shoulder and of 89.9 in the uninjured shoulder. The DASH (Disability of the Arm, Shoulder and Hand) Score was 5.9 preoperatively and 9.3 at 1 year postoperatively. The worst results regarding the Constant-Murley Score as well as the DASH Score were found in C-type fractures.
Related Concept Videos
 01:19
Bones of the Upper Limb: Humerus
 01:15
Bones of the Upper Limb: Ulna
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the procedure...
 01:09
Bones of the Upper Limb: Radius
The radius has a nail-shaped head, and a short...