Related Experiment Video
Updated: Jun 20, 2026


Cheek Injection Model for Simultaneous Measurement of Pain and Itch-related Behaviors
Published on: September 27, 2019
Physical interventions and injection techniques for reducing injection pain during routine childhood immunizations:
Anna Taddio1, A Lane Ilersich, Moshe Ipp
1Division of Pharmacy Practice, Leslie Dan Faculty of Pharmacy, University of Toronto, Toronto, Ontario, Canada. anna.taddio@utoronto.ca

Insights
Minimize childhood vaccine pain with simpler techniques. Sitting children up, skin stroking, and rapid injections reduce discomfort during immunizations, improving the experience for children and parents.
Area of Science:
- Pediatrics
- Pain Management
- Immunology
Background:
- Vaccine injections are a primary cause of iatrogenic pain in children.
- Increasing vaccination schedules raise concerns about adequate pain management.
- Physical interventions and injection techniques offer cost-effective, time-efficient pain reduction strategies.
Purpose of the Study:
- To systematically review the effectiveness of physical interventions and injection techniques for reducing vaccine injection pain in children.
- To identify evidence-based methods for improving the pediatric immunization experience.
Main Methods:
- Systematic review of randomized controlled trials (RCTs) and quasi-RCTs.
- Searched MEDLINE, EMBASE, CINAHL, and Cochrane Central Register.
- Included children aged 0-18 years, assessing pain via validated self-reports or observer ratings.
- Analyzed effects of vaccine formulation, child position, injection site, skin stimulation, vaccine order, and injection technique.
Main Results:
- Certain vaccine formulations (e.g., Priorix) caused less pain than others.
- Sitting children up or holding infants showed a trend toward reduced pain.
- Skin stroking near the injection site significantly reduced pain.
- Sequential injection of vaccines was less painful when specific vaccines were administered first.
- Rapid intramuscular injection without aspiration was associated with significantly less pain.
Conclusions:
- Vaccine injection pain can be decreased through specific strategies.
- Utilizing less painful vaccine formulations and optimal child positioning are recommended.
- Techniques like skin stroking and rapid, non-aspirated intramuscular injections effectively reduce pain.
- Strategic sequencing of multiple vaccines during a single visit can minimize overall discomfort.
Background:
Vaccine injections are the most common reason for iatrogenic pain in childhood. With the steadily increasing number of recommended vaccinations, there has been a concomitant increase in concern regarding the adequacy of pain management. Physical interventions and injection techniques that minimize pain during vaccine injection offer an advantage over other techniques because they can be easily incorporated into clinical practice without added cost or time. Their effectiveness, however, has not previously been studied using a systematic approach.
Objective:
The purpose of this review was to determine the effectiveness of physical interventions and injection techniques for reducing pain during vaccine injection in children.
Methods:
MEDLINE, EMBASE, CINAHL, and the Cochrane Central Register of Controlled Trials databases were searched to identify randomized controlled trials (RCTs) and quasi-RCTs that determined the effect of physical interventions and injection techniques on pain during injection of vaccines in children 0 to 18 years of age, using validated child self-reported pain or assessments of child distress or pain made by others (parent, nurse, physician, observer). We sought to determine the effects of: (1) different formulations of the same vaccine; (2) position of the child during injection; (3) intramuscular versus subcutaneous injection; (4) cooling of the skin at the injection site with ice before injection; (5) stroking the skin or applying pressure close to the injection site before and during injection; (6) order of vaccine injection when 2 vaccines were administered sequentially; (7) simultaneous versus sequential injection of 2 vaccines; (8) vaccine temperature; (9) aspiration before injection; (10) anatomic location of injection; (11) aspects of the needle (gauge, length, angle of insertion, speed of injection); and (12) combinations of these interventions. All meta-analyses were performed using a fixed-effects model.
Results:
Nineteen RCTs involving 2814 infants and children (0-18 years of age) were included in the systematic review. One study included children >or=16 years and adults (n = 150). Interventions with positive findings are summarized here. In 2 trials that used child self-reports of pain during administration of measles-mumps-rubella vaccine (total, 680 children with complete data), the Priorix vaccine caused less pain than the M-M-R(II) vaccine (standardized mean difference [SMD], -0.66; 95% CI, -0.81 to -0.50; P < 0.001). In 3 trials (404 children), the number needed to treat (NNT) with Priorix to prevent 1 child from crying was 3.2 (95% CI, 2.6-4.2). In 4 trials (281 infants and children), sitting children up or having parents hold infants appeared to cause less pain than the supine position, but the difference was not statistically significant; however, significant heterogeneity was found among the studies, and a qualitative approach was used for data analysis. A benefit was observed for 3 of the 4 studies; the SMD ranged from -0.4 to -0.8 (P < 0.05 for all analyses). The negative findings observed for the remaining study may have been the result of methodologic heterogeneity. Stroking the skin close to the injection site before and during injection reduced pain in 1 trial (66 children; SMD, -0.53; P = 0.03). One study (120 children) found that when diphtheria-polio-tetanus-acellular pertussis-Haemophilus influenzae type b (DPTaP-Hib; Pentacel) and pneumococcus (Prevnar) were injected sequentially during the same office visit, observer- and parent-reported pain scores were lower when DPTaP-Hib was injected first (SMD, -0.40 and -0.57, respectively; P
Conclusions:
Pain during immunization can be decreased by: (1) injecting the least painful formulation of a vaccine; (2) having the child sit up (or holding an infant); (3) stroking the skin or applying pressure close to the injection site before and during injection; (4) injecting the least painful vaccine first when 2 vaccines are being administered sequentially during a single office visit; and (5) performing a rapid intramuscular injection without aspiration.
Related Concept Videos
 01:28
Parenteral Drug Delivery Systems: Injectables, Implants, and Infusion Devices
 01:29
Drug Delivery: Parenteral Route
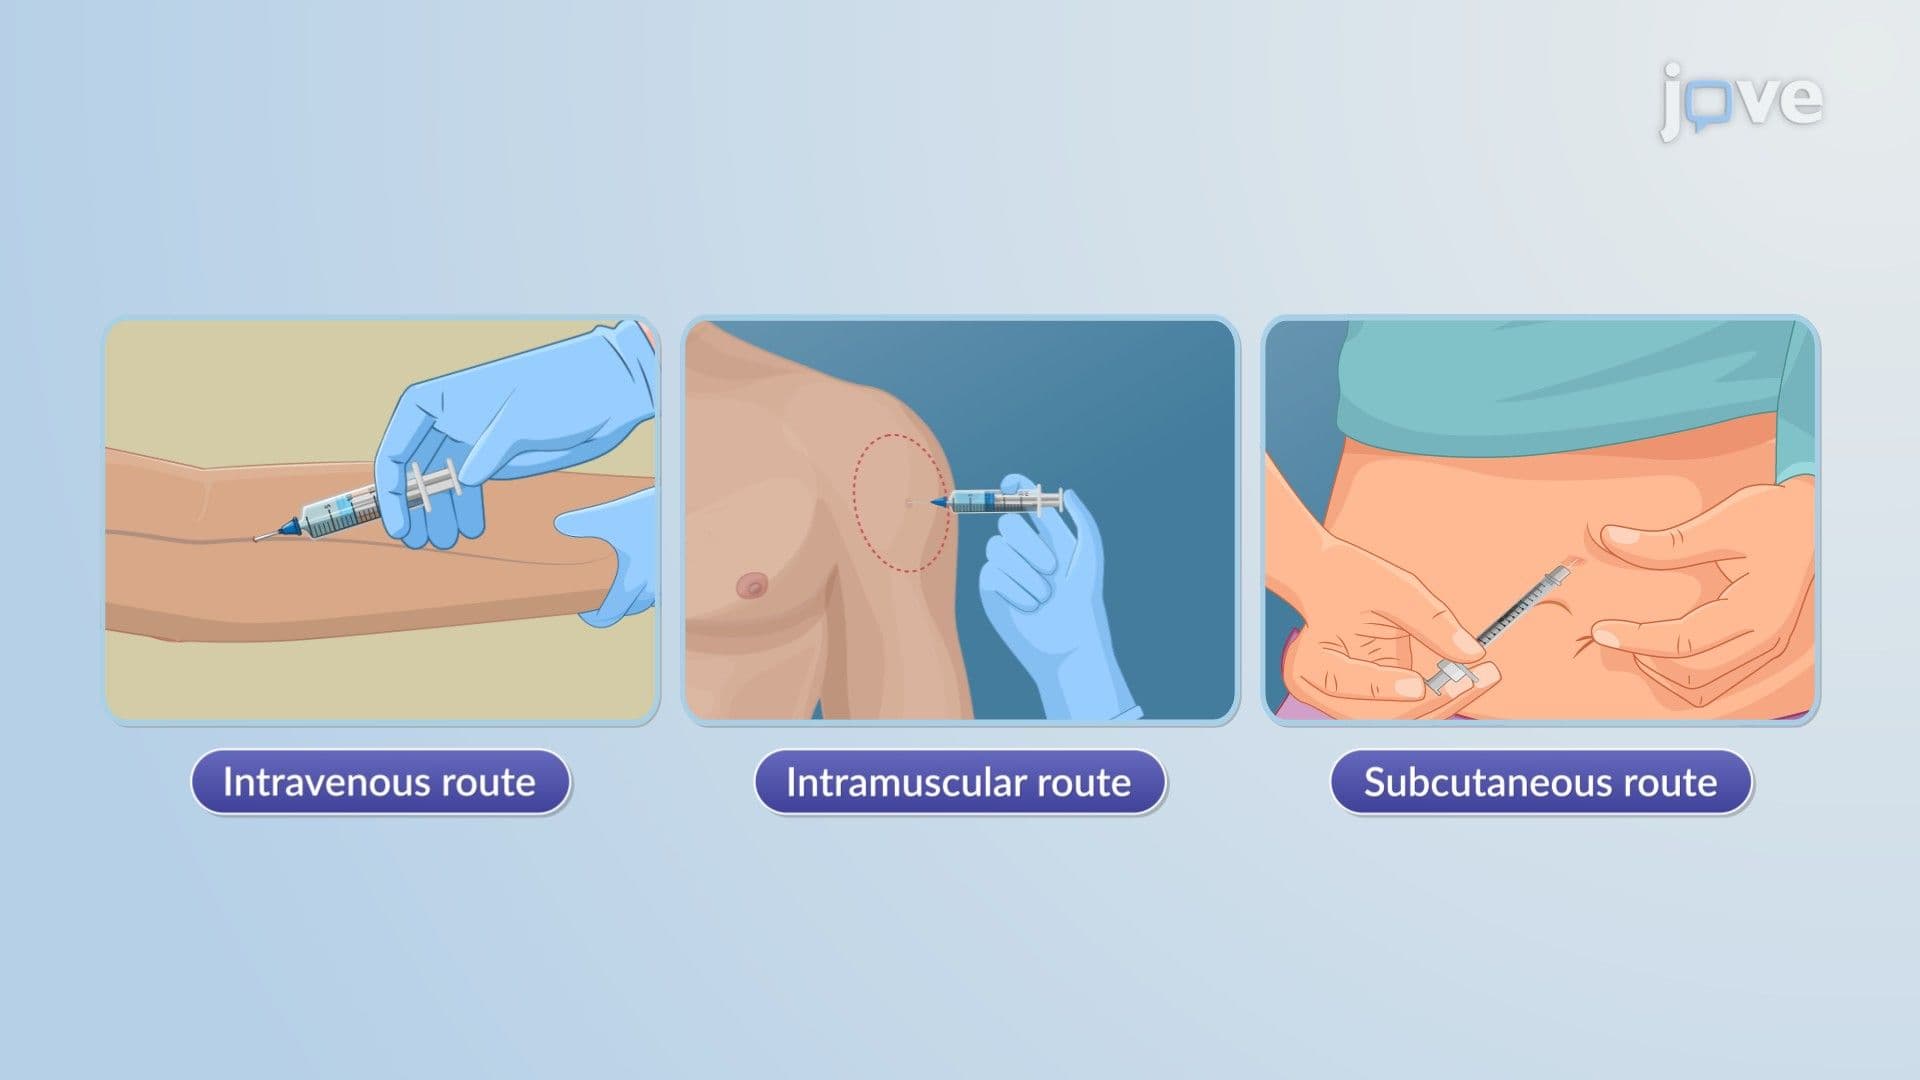
There are three primary parenteral routes: intravenous (IV), intramuscular (IM), and subcutaneous (SC). The IV route introduces the drug directly into the bloodstream, ensuring immediate action. The IM route...
 01:22
Drug Delivery: Miscellaneous Routes
Oral inhalation and nasal sprays swiftly transfer drugs across the respiratory epithelium's mucosal layer. Inhaled glucocorticoids and bronchodilators directly target lung conditions such as asthma, while fluticasone nasal spray mitigates allergic rhinitis.
Transdermal patches transport drugs through the...
 01:22
Methods of reducing fever
Pharmacological Methods of Reducing Fever:
 01:25
Routes of Drug Administration: Parenteral
The intravenous route (IV) of drug administration can be further categorized into two types. The bolus injection administers the entire dose rapidly, while an intravenous infusion slowly delivers smaller doses steadily.
The IV route is often...
 01:21
Drug Accumulation During Multiple Dosing: Repetitive IV Injections