A practical approach to benzodiazepine discontinuation
Related Experiment Video
Updated: Aug 15, 2026

A Novel Method of Drug Administration to Multiple Zebrafish (Danio rerio) and the Quantification of Withdrawal
Published on: November 12, 2014
1Department of Psychiatry, Georgetown University School of Medicine, Washington, D.C.

Abstract:
Non-medical use of benzodiazepines is rare among patients with anxiety disorders. Numerous studies have found that non-medical use, or abuse, of benzodiazepines occurs usually among patients with histories of alcohol and drug abuse--those who use those drugs to get "high". This article distinguishes between medical and non-medical use of benzodiazepines in clinical practice, and offers practical approaches to discontinuation of benzodiazepine treatment for both medical and non-medical users of those medicines. The major barrier to clear thinking about the abuse of benzodiazepines is the confusion of "addiction" and "withdrawal". Addiction means high, unstable dosing outside medical and social boundaries for "recreational" purposes, loss of control over use, and continued use despite clear evidence of harm. Alcoholism and heroin addiction are typical examples of addiction (Kalant, 1989). In contrast, withdrawal is a pharmacological consequence of discontinuation of a substance on which a person has become dependent. Many drug-addicted people have only minor withdrawal symptoms when they stop drug use. Many medical patients, with no evidence of addiction, have withdrawal symptoms when they stop treatment, especially when they stop abruptly (e.g. surgical patients using narcotic analgesics and epileptics using benzodiazepines or barbiturates in their treatment). Addiction to benzodiazepines, in the sense of loss of control over use and continued despite harm, is virtually limited to people with pre-existing drug or alcohol abuse, while withdrawal symptoms after prolonged daily use are common among medical users of benzodiazepines. The serious nature of both drug abuse and anxiety disorders is not emphasized sufficiently during medical school or in the professional literature. The distress and disability from which both groups of patients and their families suffer is profound. Fortunately, both drug abuse and anxiety patients receive tremendous benefit from successful treatments, both pharmacological and nonpharmacological (DuPont, 1986a; DuPont, 1984). This article discusses the use of benzodiazepines in two distinct populations--drug abusers and patients with anxiety disorders--and helps clinicians distinguish between the use of benzodiazepines in the two groups. The central distinction made in this article is reflected in the common use of the words "drugs" and "medicines". The former term often denotes non-medical substance use, while the latter term refers to traditional pharmacotherapy.
Related Concept Videos
 01:14
CNS Depressants: Barbiturates and Benzodiazepines
 01:26
Anxiolytic Drugs: Overview
Primary Types of Anxiolytic Drugs
1. Benzodiazepines:
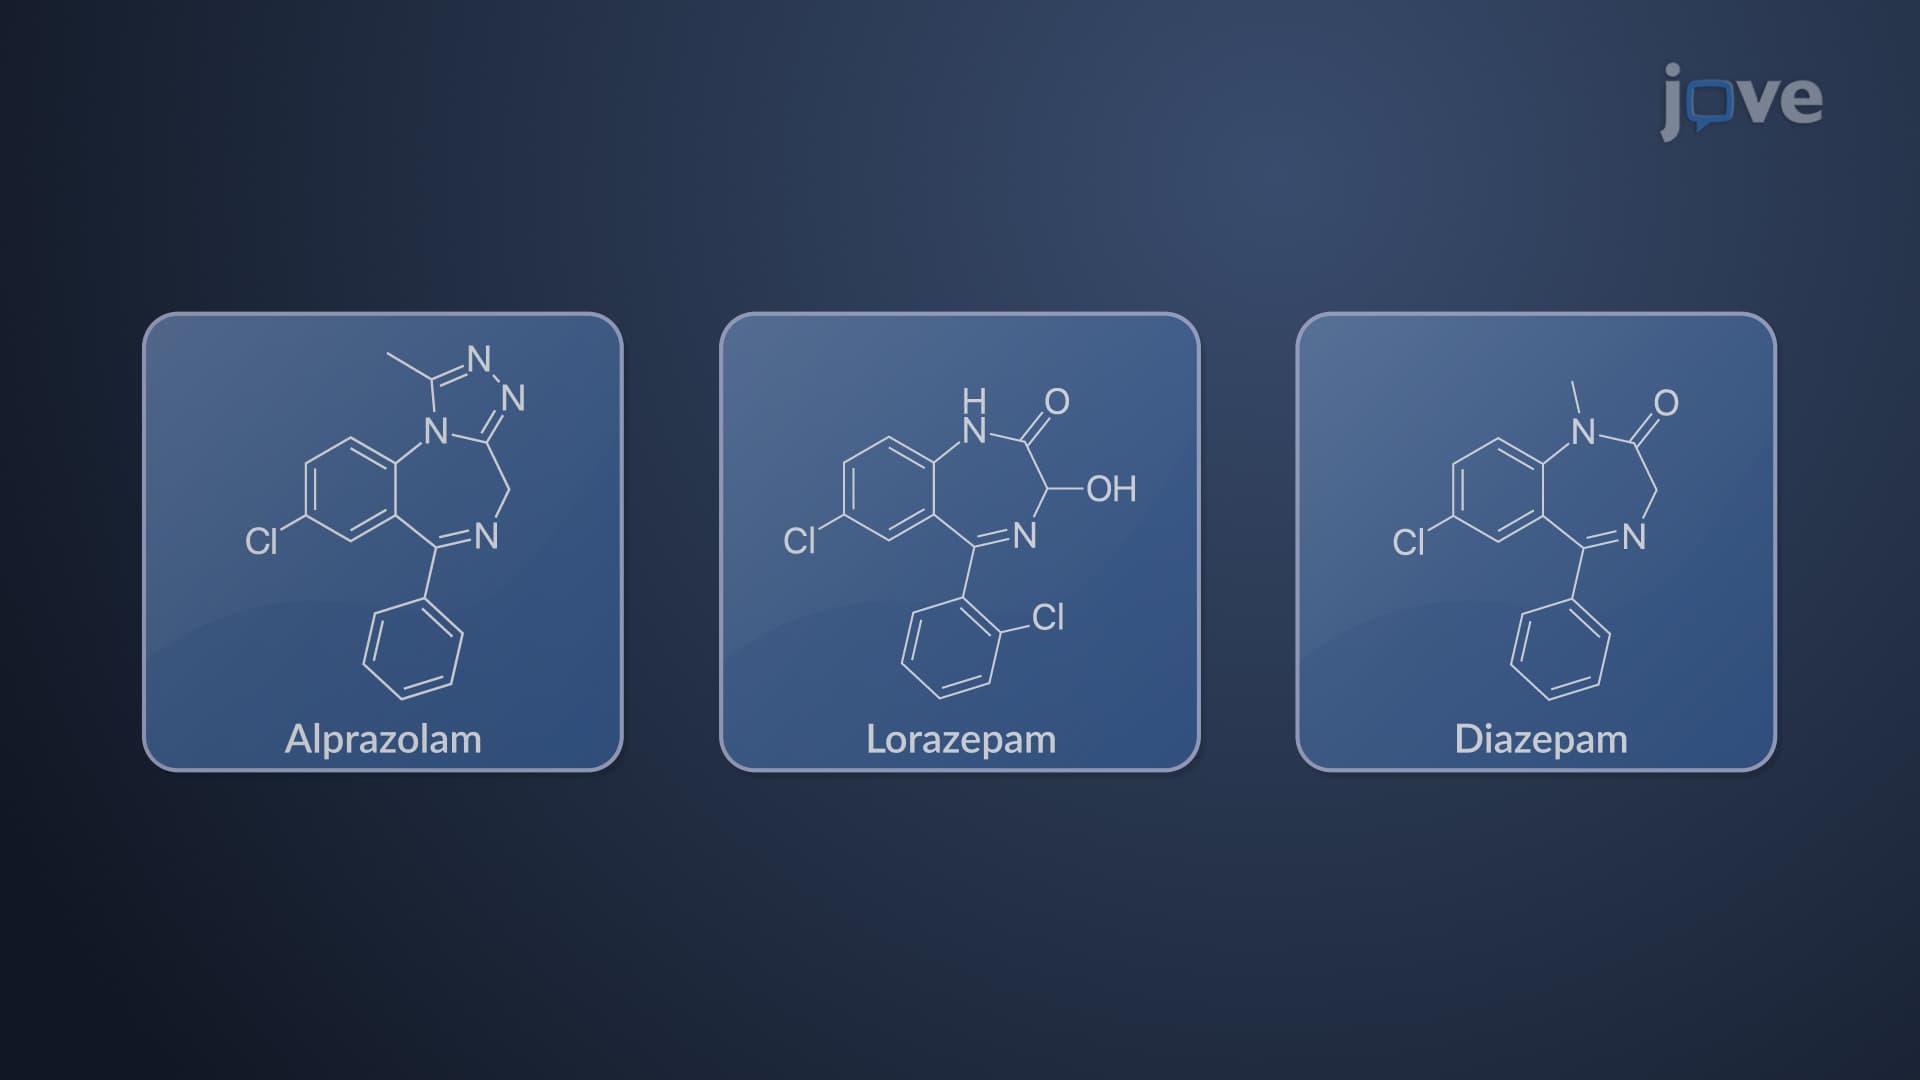
Benzodiazepines bind to the GABA-A receptor in the brain, enhancing GABA's interaction. This action reduces neurotransmission, effectively blocking anxiety-associated limbic circuitry.
 01:29
Anxiolytic Drugs: Benzodiazepines and Buspirone
 01:23
Sedatives and Hypnotics: Overview
Sedative-hypnotics are categorized into barbiturates, benzodiazepines (BZDs), and non-benzodiazepines or Z-drugs. These drugs work by suppressing central nervous system activity, and this suppression is dose-dependent. Older sedative medications, like barbiturates, follow a linear curve in...
 01:19
Management of Insomnia
 01:19
Sedatives and Hypnotics Drugs: Benzodiazepines
Benzodiazepines work by enhancing the effects of the inhibitory neurotransmitter GABA. They bind to the GABAA receptor, increasing its affinity for GABA, which opens chloride...