Related Experiment Video
Updated: Jun 19, 2026
Endoscopic Approach for Colloid Cyst Resection
Published on: May 23, 2025
Limits of endoscopic treatment of sylvian arachnoid cysts in children
Federico Di Rocco1, Syril R James, Thomas Roujeau
1Department of Paediatric Neurosurgery, Hôpital Necker-Enfants Malades, University Paris V René Descartes, 75015 Paris, France.

Insights
Endoscopic surgery for sylvian arachnoid cysts in children is safe and effective, resolving symptoms. Long-term stoma patency requires further evaluation, but endoscopic re-opening is successful.
Area of Science:
- Pediatric Neurosurgery
- Minimally Invasive Surgery
- Neuroendoscopy
Background:
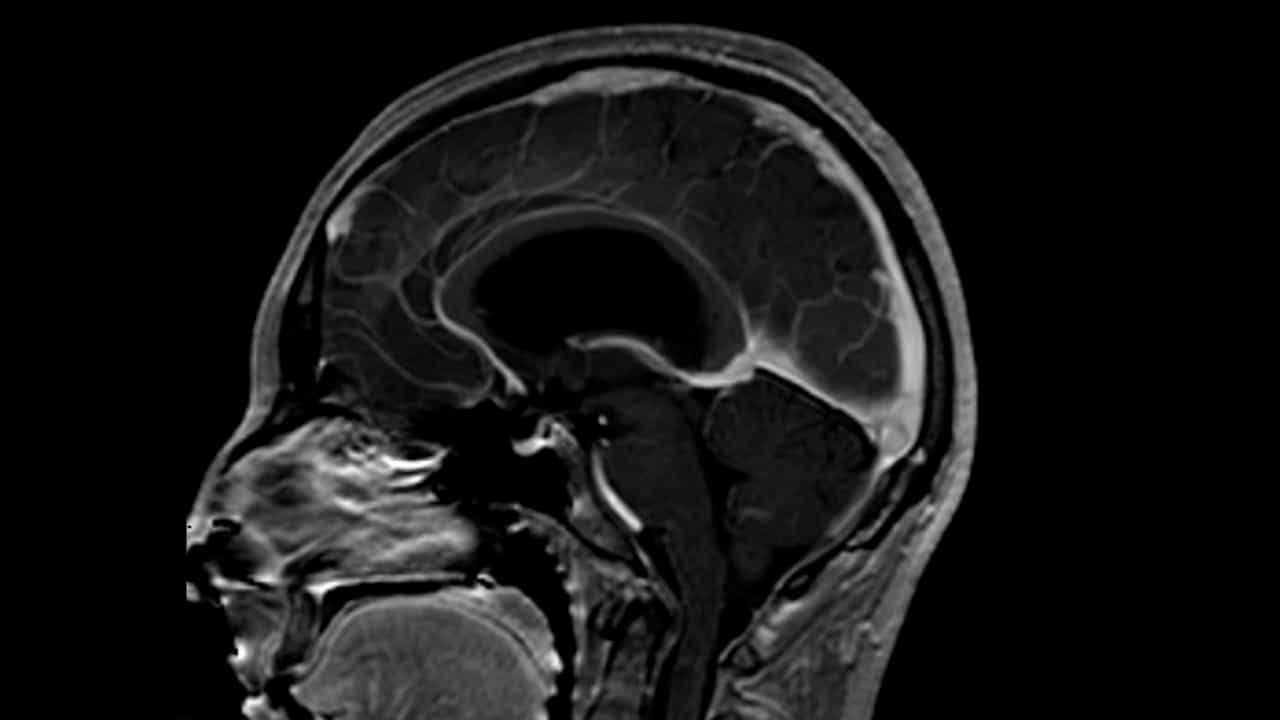
- Sylvian arachnoid cysts are a common neurosurgical condition in children.
- Optimal surgical management remains a subject of debate.
- Endoscopic techniques offer a minimally invasive alternative.
Purpose of the Study:
- To evaluate the safety and efficacy of a purely endoscopic approach for sylvian arachnoid cysts in pediatric patients.
- To identify the limitations and potential complications of this endoscopic technique.
Main Methods:
- Seventeen pediatric patients with temporo-sylvian arachnoid cysts underwent a purely temporal endoscopic approach.
- Procedures focused on cysto-cisternostomy to relieve mass effect.
Main Results:
- Successful endoscopic cysto-cisternostomy was achieved in all patients, with multiple stomies created in 13.
- Preoperative symptoms resolved in all cases.
- Complications included one instance of venous bleeding and two cases of symptomatic subdural collections requiring temporary shunts. Two recurrences were noted due to stoma closure, successfully managed with repeat endoscopy.
Conclusions:
- Endoscopic management of sylvian arachnoid cysts in children is safe and effective in resolving symptoms.
- The procedure allows for effective fenestration into basal cisterns.
- Long-term efficacy of the stoma requires continued assessment, though endoscopic revision is feasible.
Introduction:
The optimal surgical management of sylvian arachnoid cysts is debated. We present our experience in children who were treated endoscopically, focusing on the limits and complications of this approach.
Materials And Methods:
Seventeen children with a temporo-sylvian arachnoid cyst have been treated using a purely temporal endoscopic approach.
Results:
In all but one case, the recognition of anatomical landmarks was obtained at the insertion of the endoscope. In one child, the orientation and opening of the basal cisterns were more difficult due to the thickness and opacity of the membranes. Nevertheless, it was possible to perform the cysto-cisternostomy endoscopically in all children with several stomies in 13. In one child, a venous bleeding occurred. There were no other intraoperative complications. There were no postoperative cerebrospinal fluid leaks. In two patients, a symptomatic subdural collection developed which required a transient subdural-peritoneal shunt. No subdural collection was noted on a delayed follow-up (mean, 23 months). Preoperative symptoms related to the mass effect exerted by the cyst resolved in all children. Two children presented a recurrence, 12 and 20 months after endoscopic surgery, respectively. At the redo-endoscopy, the stomies were found to be closed. Their reopening resulted in the disappearance of the symptoms.
Conclusions:
An endoscopic approach can be used safely in the management of sylvian arachnoid cysts. An effective opening of the deep arachnoid membranes into the basal cisterns could be performed in all patients with the resolution of the preoperative symptoms. However, the long-term efficacy of the stoma needs to be assessed.