Related Experiment Video
Updated: Jun 19, 2026
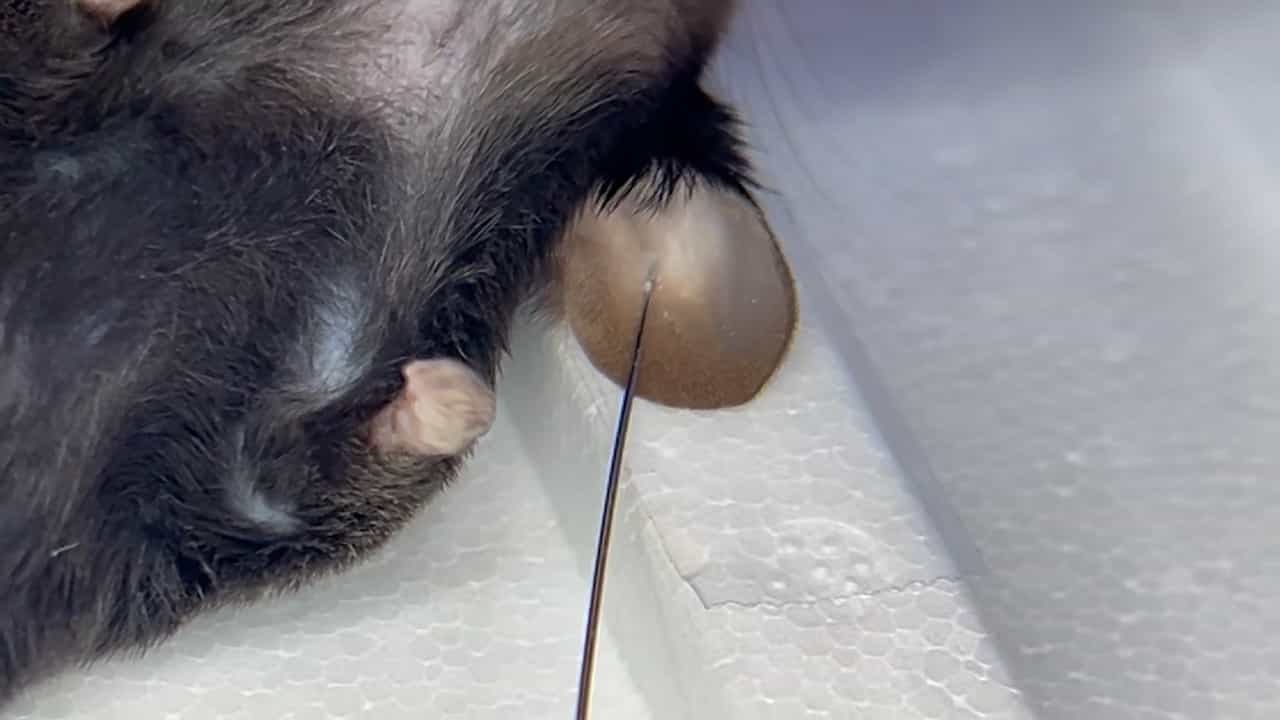

Intradermal Inoculation of Mycobacterium avium in the Mouse Ear
Published on: July 3, 2025
Intrathoracic nontuberculous mycobacterial infections in otherwise healthy children
Alexandra F Freeman1, Kenneth N Olivier, Thomas T Rubio
1SAIC-Frederick, Inc, NCI-Frederick, Frederick, Maryland 27102, USA. freemaal@mail.nih.gov

Background:
Nontuberculous mycobacterial (NTM) infection is typically associated with lymphadenitis in immune competent children, and disseminated disease in children with immune deficiencies. Isolated pulmonary NTM disease is seen in cystic fibrosis, and is increasingly recognized in immunocompetent elderly women, where it is associated with an increased incidence of cystic fibrosis transmembrane regulator (CFTR) mutations. Thoracic NTM infection has been reported rarely in otherwise healthy children. We aimed to determine whether otherwise healthy children with pulmonary NTM disease had immunologic abnormalities or CFTR mutations. Clinical presentations of five otherwise healthy children with pulmonary NTM were reviewed. Immunologic studies were performed including a complete blood cell count (CBC), flow cytometric lymphocyte phenotyping and IFN-gamma receptor expression, in vitro cytokine stimulation, and serum immunoglobulin levels. Mutational analysis was performed for CFTR. The children ranged in age from 12 months to 2.5 years at diagnosis. Four presented with new onset wheezing or stridor failing bronchodilator therapy. One child was asymptomatic. Endobronchial lesions and/or hilar lymph nodes causing bronchial obstruction were identified in all patients. Mycobacterium avium complex was cultured from four patients, and Mycobacterium abscessus from one patient. All patients were successfully treated with anti-mycobacterial therapy with or without surgery. No definitive immunologic abnormalities were identified. No clinically significant mutations were found in CFTR. Pulmonary NTM infection should be considered in otherwise healthy young children presenting with refractory stridor or wheezing with endobronchial lesions or hilar lymphadenopathy. It does not appear to be associated with recognized underlying immune deficiency or CFTR mutations.

Related Concept Videos
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:28
Pulmonary Tuberculosis II
Here is a detailed explanation of its pathophysiology:
Transmission: The process begins when a person inhales droplet nuclei containing M. tuberculosis. These are typically released into the air when an individual with pulmonary or...
 01:26
Pulmonary Tuberculosis IV
Several diagnostic approaches are used to detect TB. The conventional method is the Tuberculin Skin Test (TST), also known as the Mantoux test. However, this method has...
 01:31
Pulmonary Tuberculosis III
The first classification is based on the development of the disease, and it includes the following categories:
 01:23
Tuberculosis
 01:28
Pulmonary Tuberculosis V
Latent tuberculosis infection occurs when TB bacteria are present in a person's body, but are not causing illness or symptoms. It is not contagious, and preventive treatment is crucial to avoid the progression...