Related Experiment Video
Updated: Jun 19, 2026

The Immediate Partial Removal of Cumulus-Oocyte Complexes: A Refined Approach for Rapid Observation of In Vitro Fertilization
Published on: October 18, 2024
New outpatient subclassification system for American Fertility Society Classes V and VI uterine anomalies
Giampietro Gubbini1, Attilio Di Spiezio Sardo, Daniela Nascetti
1Department of Obstetrics and Gynaecology, Hospital Madre Fortunata Toniolo, Bologna, Italy.

Study Objective:
To produce and validate a simple, systematic and reproducible subclassification system for uterine anomalies previously classified by the American Ferility Society as Class V and VI to achieve a precise definition of each uterine anomaly, confirm the feasibility and safety of surgical correction of the anomalies, determine the type of hysteroscopic treatment, and provide a standard by which patient selection, treatment, and reproductive outcomes can be compared between centers.
Design:
Descriptive study (Canadian Task Force Classification III).
Setting:
Department of obstetrics and gynecology of a private clinic (hospital).
Patients:
Eighty-nine patients undergoing office hysteroscopy to assess partial or complete "double" uterine cavity.
Interventions:
All patients underwent 3-dimensional ultrasound. Data from hysteroscopy and untrasonography were combined to produce a geometric model comprising uterine septum length (Z variable) and fundus depth (Y variable) through which a new subclassification of the uterine anomalies was elaborated.
Measurement And Main Results:
One patient with a bicornuate uterus detected at ultrasonography was excluded from the study. The remaining 88 patients were classified according to our subclassification system. Seventy-three patients categorized as having Z 2 cm or greater (septum intersecting one-third of the uterine cavity or more) and Y more than 0 cm (normal or straight uterine fundus) underwent resectoscopic metroplasty without laparoscopic control. Twelve patients categorized as A1 (normal uterine fundus and septum < or =0.5 cm) underwent office metroplasty. Two patients categorized as B1 (straight fundus and septum < or =0.5 cm) and 1 categorized as C1 (concave fundus and septum < or =0.5 cm) were not considered candidates for surgery. Second-look hysteroscopy confirmed complete removal of the septum in the 12 patients who underwent office metroplasty (100%) and in 70 of 73 patients (96%) who underwent resectoscopic metroplasty. Comparison of these data with data retrospectively obtained in 596 women who had undergone traditional resectoscopic metroplasty under laparoscopic control did not demonstrate any significant difference in success and complication rates.
Conclusion:
Our outpatient subclassification system may address a precise diagnosis and a thorough categorization of patients with a partial or complete double uterine cavity, enabling safe and effective metroplasty without use of laparoscopy.
Related Concept Videos
 01:24
In Vitro Fertilization
The IVF process begins with ovarian stimulation, during which reproductive endocrinologists prescribe hormonal medications to stimulate the ovaries to produce multiple eggs instead of the single...
 01:07
Teratogenicity
 01:28
Infertility in Females
Endometriosis, a condition characterized by abnormal growth of endometrial...
 01:24
Disorders of the Female Reproductive System
 01:30
Heart Failure IV: Classification and Diagnostic Evaluation
 01:16
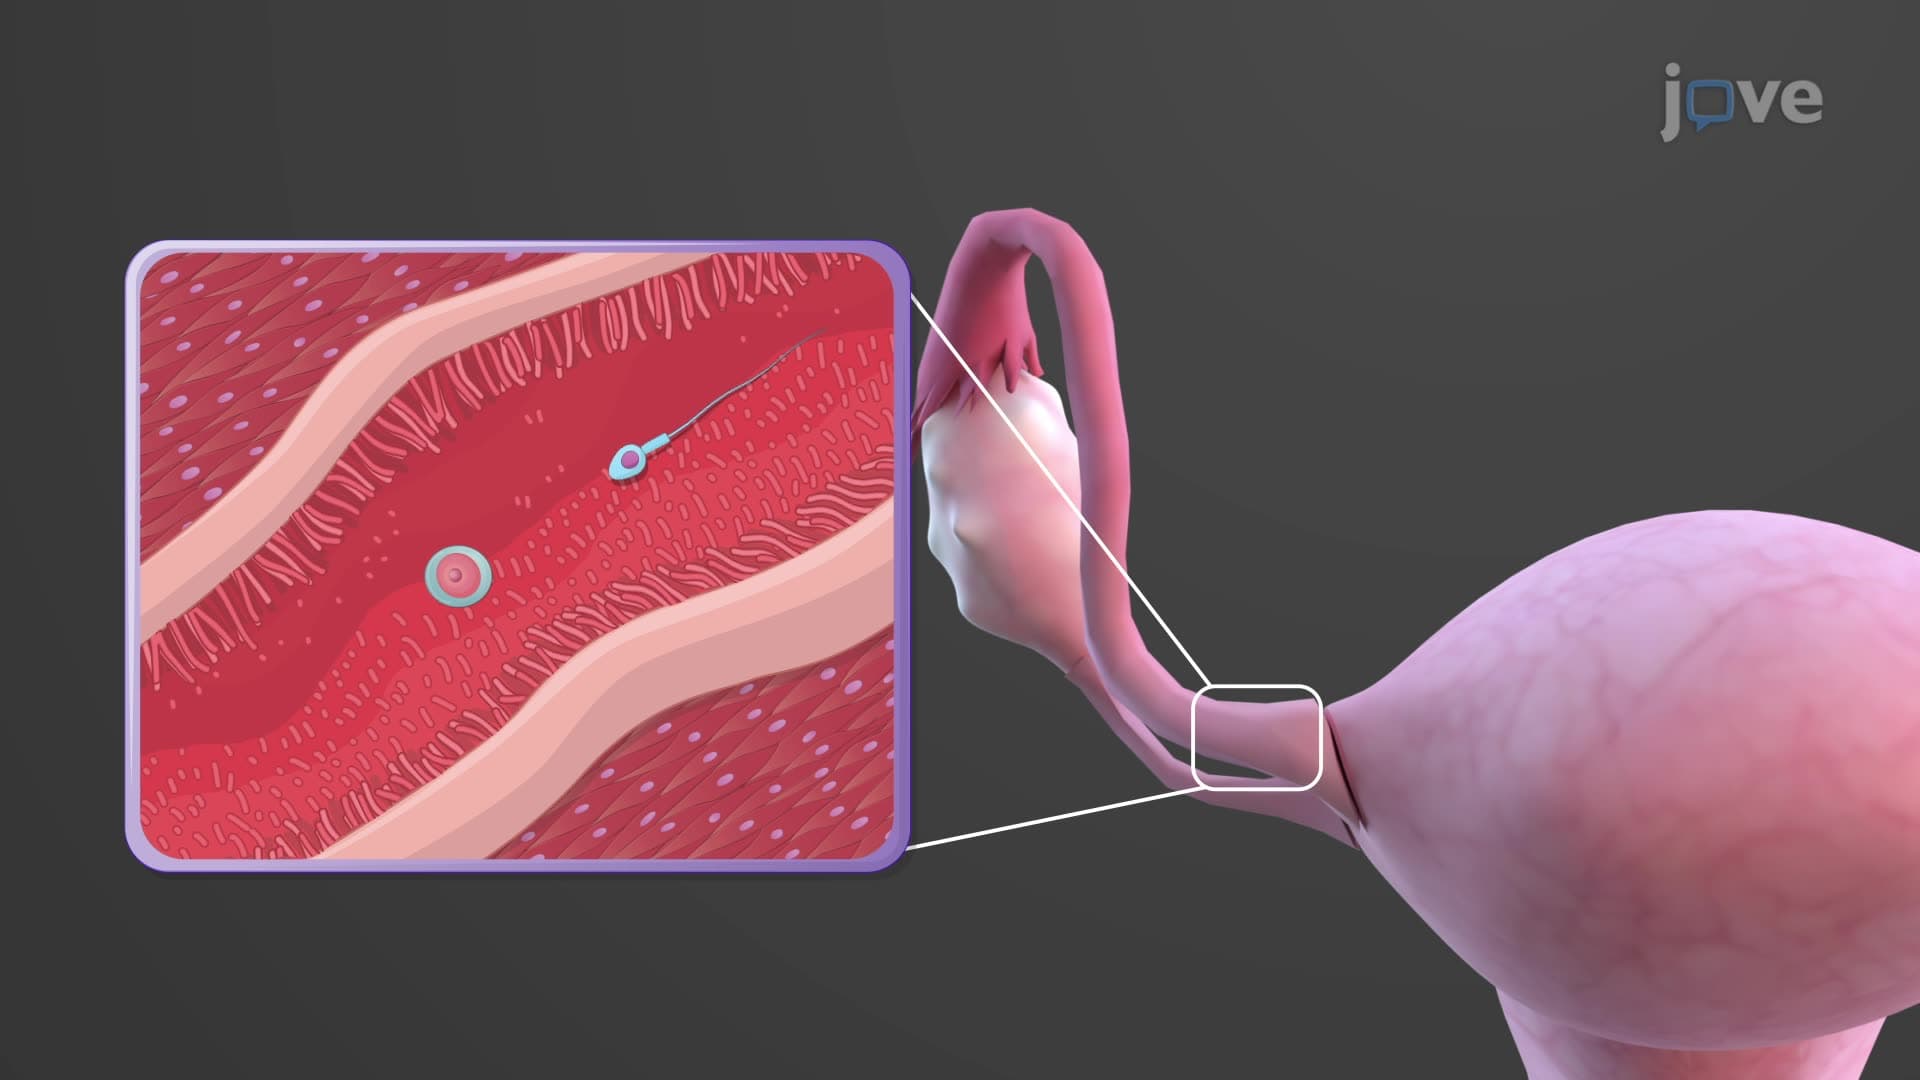
Uterine Tubes