Related Experiment Video
Updated: Sep 6, 2026


Cytotoxic Efficacy of Photodynamic Therapy in Osteosarcoma Cells In Vitro
Published on: March 18, 2014
The pharmacology of intravenous and oral etoposide
1Mater Misericordiae Hospital, Dublin, Ireland.

Abstract:
The epipodophyllotoxin derivative etoposide (VP-16) has been in widespread use both alone and in combination chemotherapy for the past decade. It has phase-specific cytotoxicity that acts in the last S and G2 phases of the cell cycle. Although its mode of action is not certain, it appears to act by causing breaks in DNA by interaction with DNA-topoisomerase II or by the formation of free radicals. Most studies show biexponential decay after the intravenous (IV) administration of etoposide. Approximately 30% to 70% of administered etoposide is excreted, with approximately 45% present in the urine. Etoposide is available in oral and IV preparations. It is highly schedule-dependent, with once-daily doses (e.g., for 5 to 8 days every 21 days) giving results superior to intermittent administration. The bioavailability of oral etoposide is approximately 50%, but its absorption is not linear with increasing dose (e.g., greater than 200 mg/d, bioavailability decreases). Factors influencing the bioavailability of oral etoposide include patient status, concurrent medications, hepatic and renal function, and nausea and vomiting. In numerous clinical trials, etoposide has demonstrated excellent activity against a range of tumors, including small cell lung cancer (SCLC), malignant lymphomas, gestational trophoblastic tumors, Ewing's and soft tissue sarcomas, and germ cell tumors, with more modest activity in other tumors (e.g., non-SCLC). Although few comparative studies have been carried out, available data suggest that oral etoposide administered daily during 5 to 8 days is similar to the IV preparation in range of activity. In a study of 53 elderly patients with SCLC treated with etoposide (200 mg/d for five times), there was a response rate of 79% and a median survival of 9.5 months. These results were similar to those achieved with more intensive IV regimens. Several studies of chronic oral etoposide (50 mg/m2/d for 21 times) have been reported recently. Responses were observed in SCLC and germ cell tumors among patients who had relapsed after standard etoposide-containing regimens. These data suggest that etoposide may be a "new" drug when given in this schedule. The high response rates with oral etoposide suggest that oral administration may be substituted for IV administration. This substitution may allow for greater flexibility in chemotherapeutic administration, less hospitalization, and more acceptable toxicity.


Related Concept Videos
 01:25
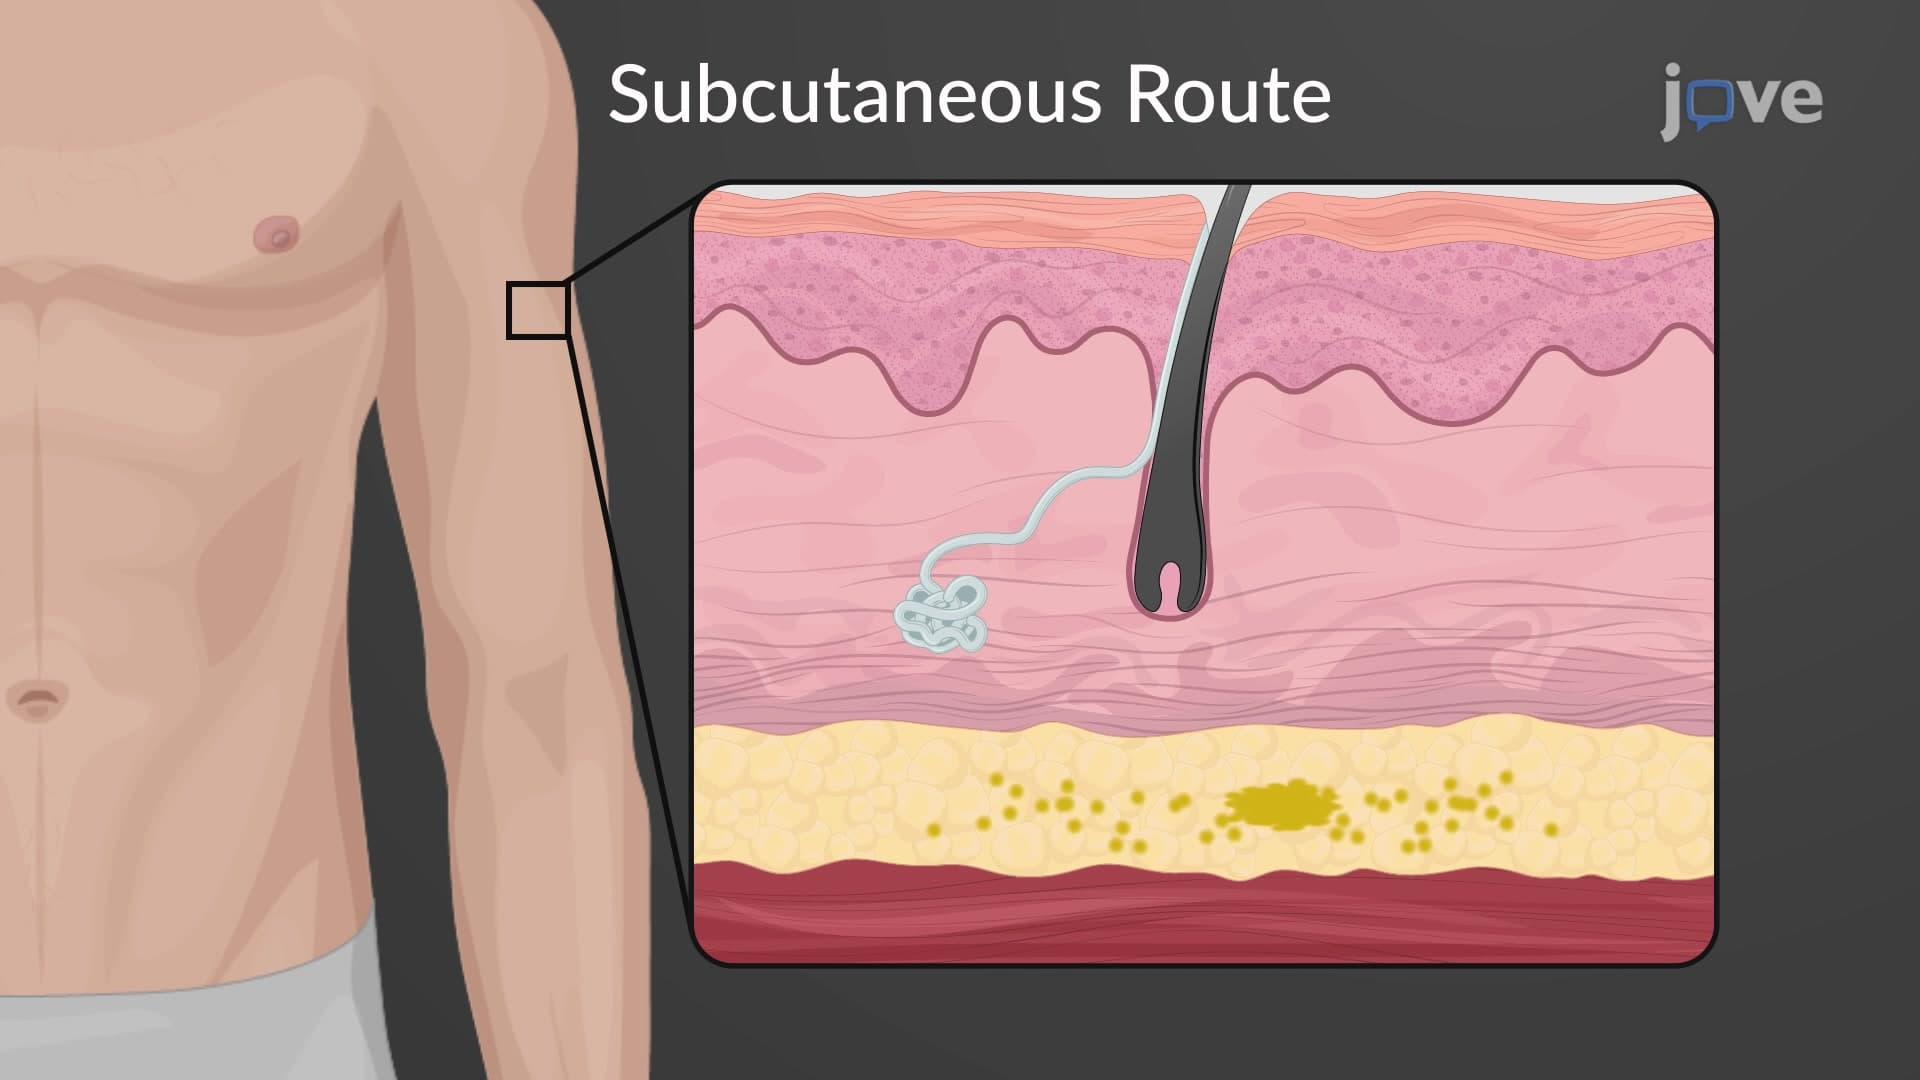
Routes of Drug Administration: Parenteral
The intravenous route (IV) of drug administration can be further categorized into two types. The bolus injection administers the entire dose rapidly, while an intravenous infusion slowly delivers smaller doses steadily.
The IV route is often...
 01:24
Parenteral Anesthetics: Overview
 00:59
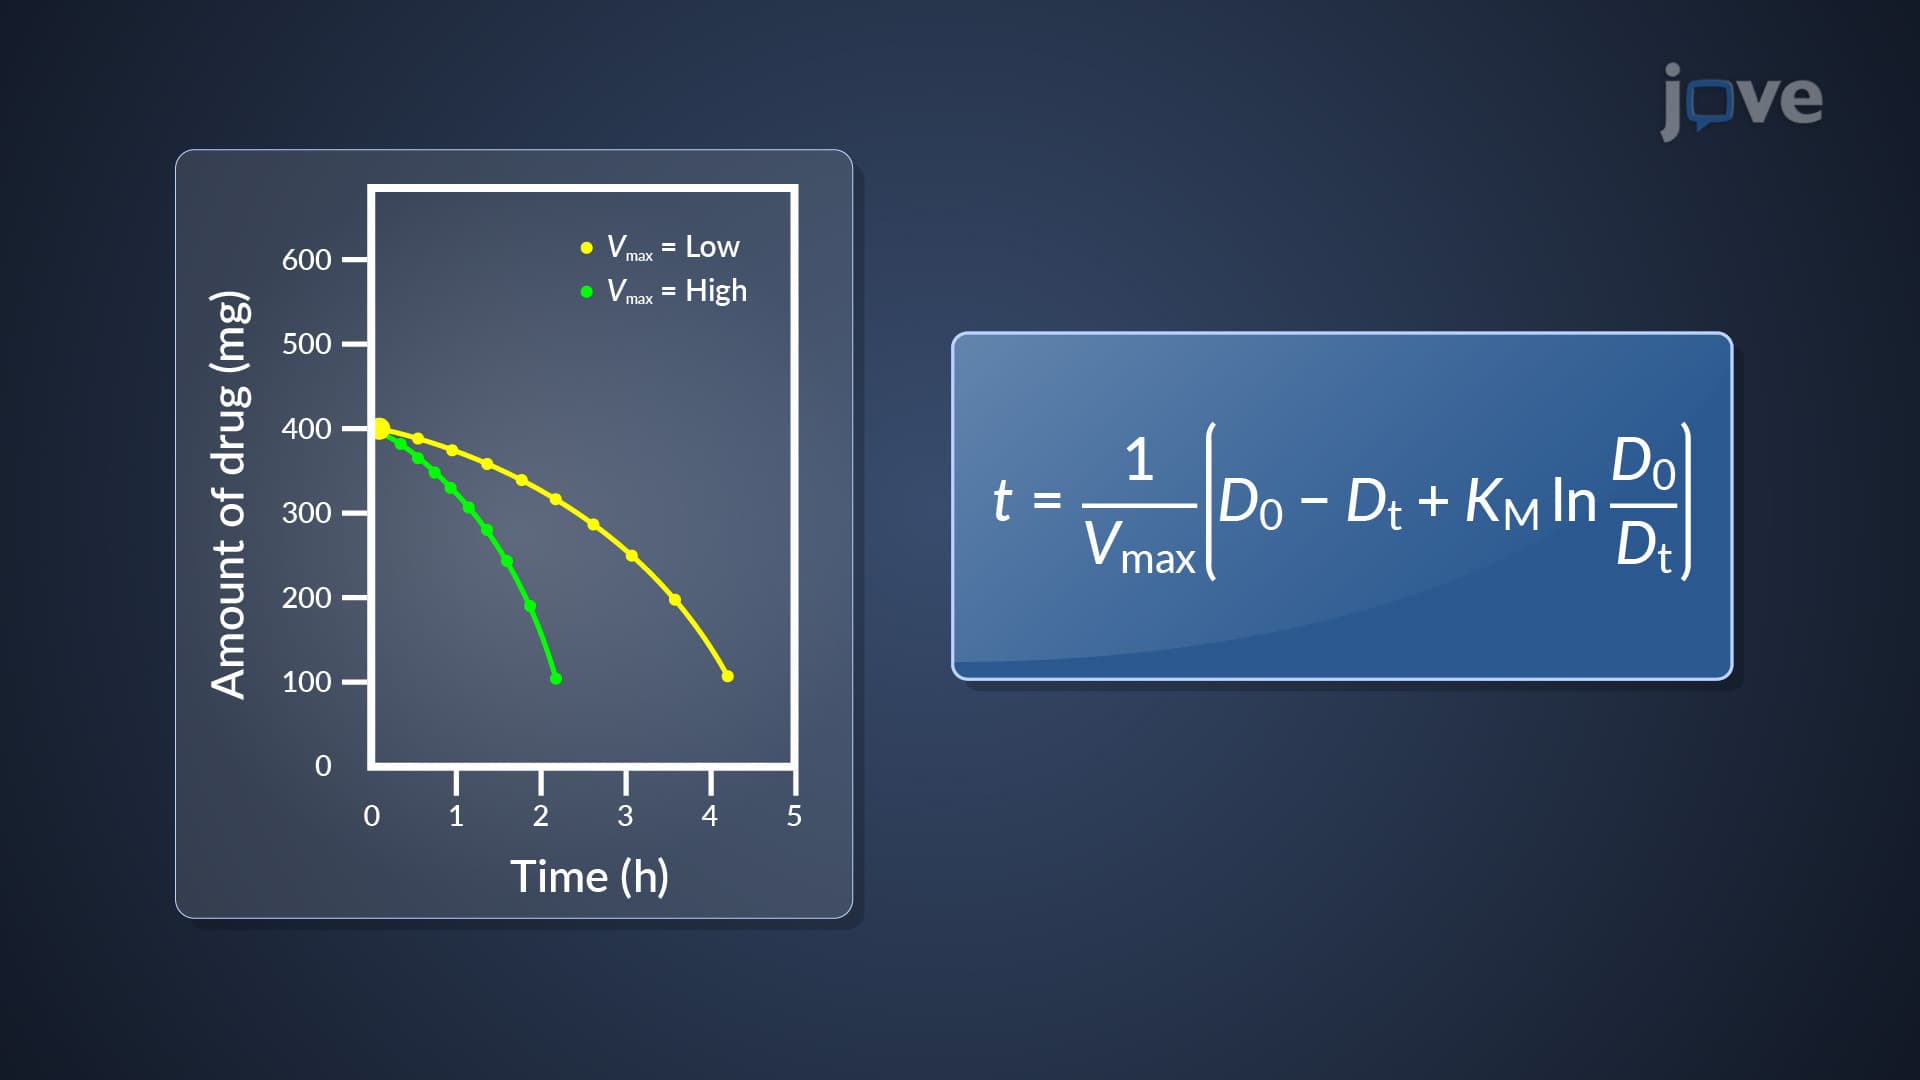
Nonlinear Pharmacokinetics: Drug Elimination for IV Bolus Injection
Following the administration of a single intravenous (IV) bolus injection, we can determine the concentration of the drug in the plasma at any given time. This calculation is achieved using a specific equation that integrates the values of Vmax and KM.
We can also...
 01:24
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:28
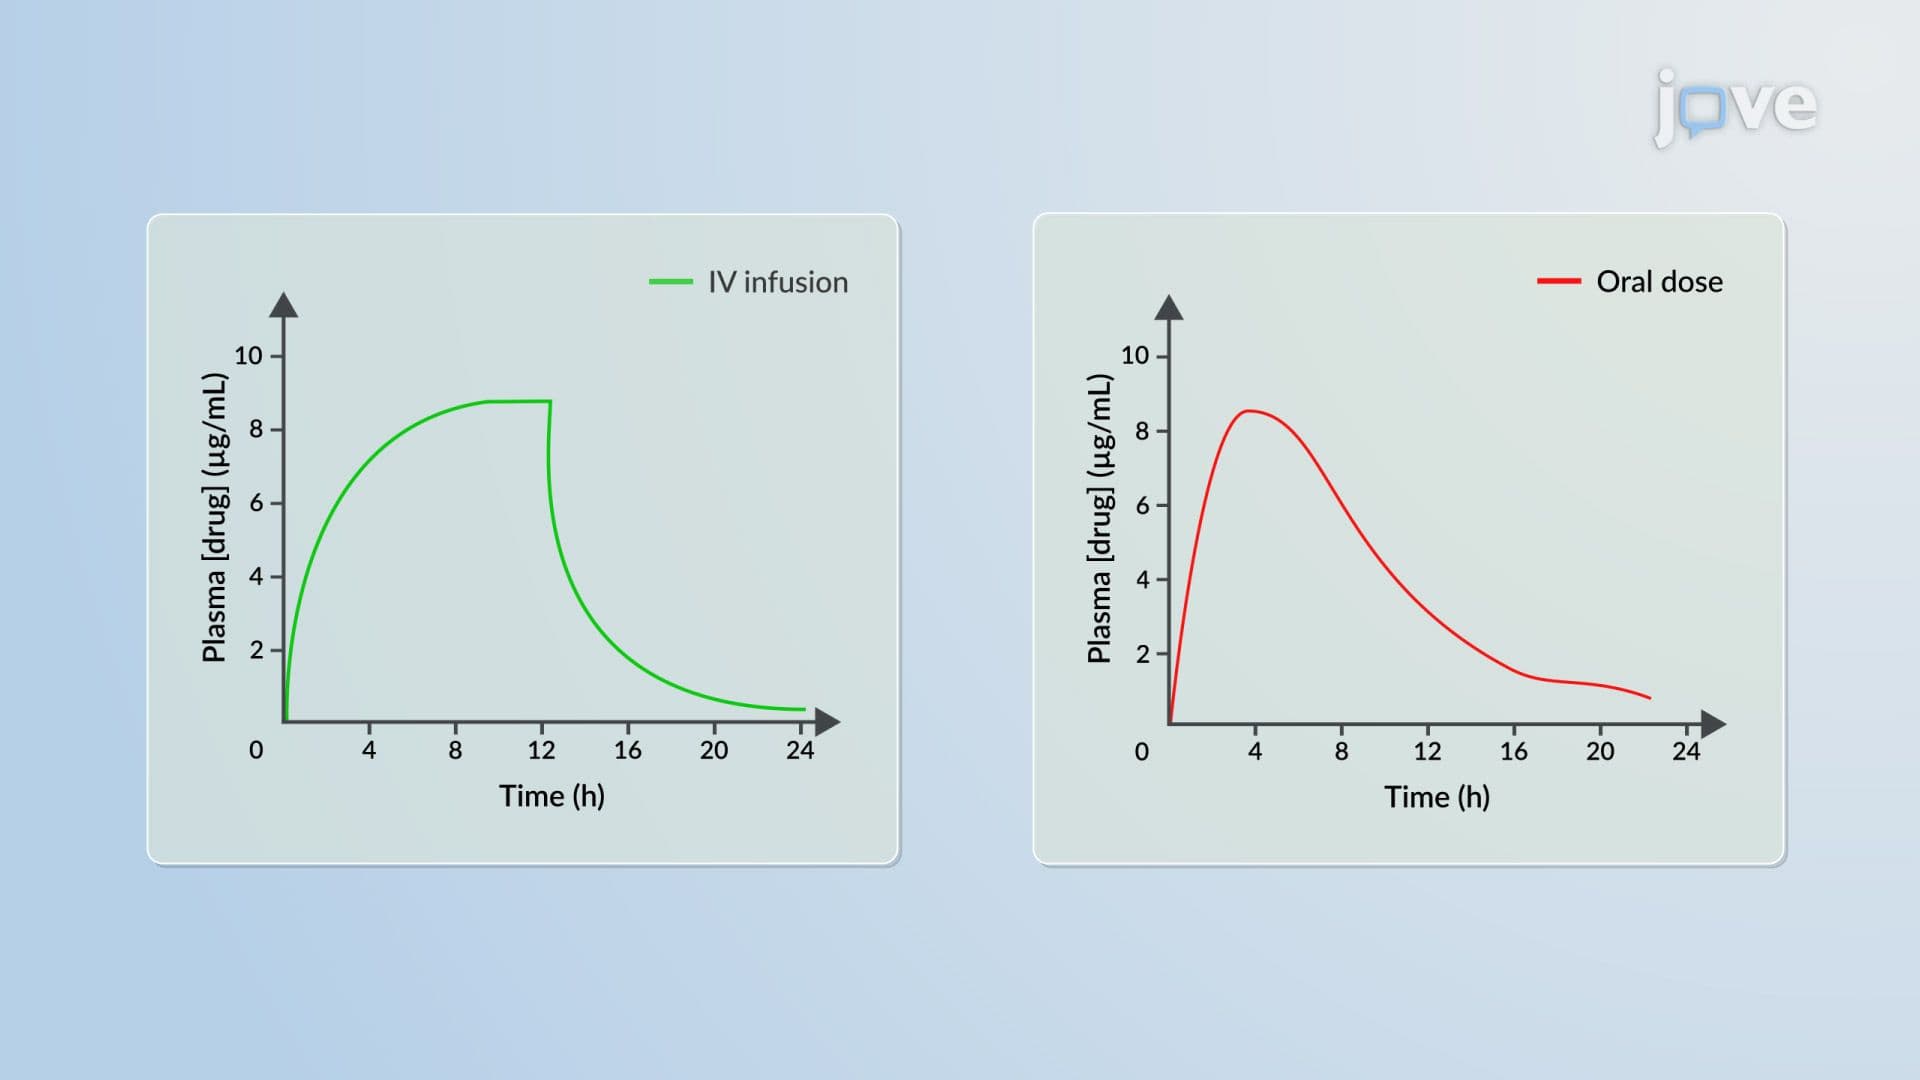
IV Infusion to Oral Dosing: Conversion Methods
 01:26
Pharmaceutical Poisoning: Treatment Strategies