Related Experiment Video
Updated: Jun 19, 2026
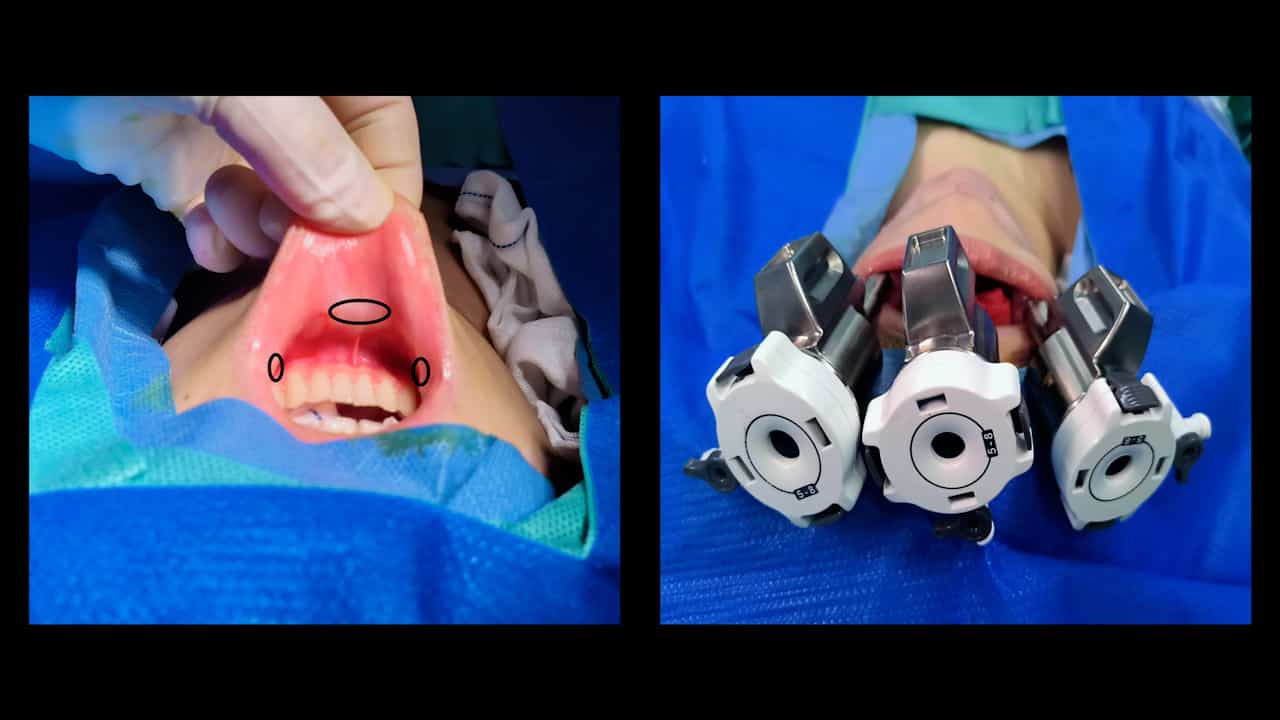

Identification and Protection of the Recurrent Laryngeal Nerve during Transoral Robotic Thyroidectomy
Published on: October 24, 2025
[Unilateral laryngeal immobility after surgery of the thyroid gland]
O Laccourreye1, D Malinvaud, M Ménard
1Service d'oto-rhino-laryngologie et de chirurgie cervicofaciale, université Paris-V--Descartes, hôpital européen Georges-Pompidou, AP-HP, 20-40, rue Leblanc, 75015 Paris, France. ollivier.laccourreye@egp.aphp.fr

Background:
The authors studied a cohort of 154 patients with unilateral vocal cord paresis following thyroidectomy, analyzing the pathogenesis, symptomatology, spontaneous evolution, and management of this complication.
Objective:
This retrospective study distinguished between vocal cord paresis due to recurrent laryngeal nerve injury or due to injury of the cricoarytenoid articulation. We assessed the influence multiple variables on therapeutic management. The results and complications of currently-employed surgical techniques to remedy unilateral vocal cord paresis were defined.
Patients And Methods:
Injury to the recurrent laryngeal nerve was the cause of vocal cord paresis in 98% of cases; injury to the cricoarytenoid articulation accounted for only 2% of cases. When the recurrent laryngeal nerve had not been actually transected, spontaneous recovery of vocal cord function occurred in 36% of cases. No spontaneous recovery was noted when the nerve had been divided. The interval to recovery of cord function ranged from 2 to 15 months (median: 4 months). Spontaneous recovery of vocal cord function had occurred in 90% of these patients by the 9th postoperative month. Three factors significantly influenced the decision to perform a median transposition of the injured vocal cord: known transection of the recurrent laryngeal nerve, the interval to consultation with an ENT specialist, and the severity of dysphonia. Medial transposition of the injured vocal cord resulted in an immediate improvement in the quality of voice and speech with no major complications.
Conclusion:
Unilateral vocal cord paresis occurring after thyroidectomy is not always symptomatic and is not uniformly due to injury of the recurrent laryngeal nerve. Management does not always require surgical reintervention. The practical and medico-legal consequences of these injuries are discussed.

Related Concept Videos
 01:21
Larynx
Anatomy of the Larynx
The larynx consists of various components, including cartilage, muscles, and vocal cords. Its structure includes three large unpaired cartilages—the thyroid, cricoid, and epiglottis—and three smaller paired cartilages—the arytenoids, corniculates, and...
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:23
The Thyroid Gland
The follicles have a central cavity lined by simple cuboidal to squamous epithelial cells called follicular cells. These cells produce the glycoprotein...
 01:12
The Hyoid Bone
 01:22
Trachea
Anatomical Features:
Location: About half of the trachea is situated in the neck, anterior to the esophagus, and extends from the larynx (at the level of the...