Related Experiment Video
Updated: Jun 18, 2026


Quantifying Acute Changes in Renal Sympathetic Nerve Activity in Response to Central Nervous System Manipulations in Anesthetized Rats
Published on: September 11, 2018
Differential effects of oral beta blockade on cardiovascular and sympathetic regulation
S P Beloka1, S Gouveia, M Gujic
1Department of Cardiology, Erasmus Hospital, Université Libre de Bruxelles, Brussels, Belgium. sbeloka@gmail.com

Abstract:
In patients with hypertension, beta blockade decreases muscle sympathetic nerve activity (MSNA; micrographic technique) expressed in burst frequency (burst/min) but does not affect MSNA expressed in burst incidence (burst/100 heart beats), because reductions in blood pressure (BP) upon each diastole continue to deactivate the arterial baroreceptors, but at a slower heart rate (HR). We studied the effects of oral beta blockade on MSNA and baroreflex sensitivity (BRS) in normal participants. Bisoprolol (5 mg, 1 week) was administered in 10 healthy young adults, using a double-blind, placebo-controlled, randomized cross-over study design. The beat-to-beat mean RR interval (RR) and systolic blood pressure (SBP) series were analyzed by power spectral analysis and power computation over the very low frequency (VLF), low frequency, and high frequency (HF) bands. Baroreflex sensitivity was computed from SBP and RR cross-analysis, using time and frequency domain methods. Bisoprolol increased RR (P < .0005), decreased mean SBP and diastolic blood pressure values (P < .01), did not change the SBP and RR powers, except for RR power in VLF (P < .02) and SBP power in HF (P < .03). The MSNA variability (P > .13) and respiratory pattern (P = .84) did not change from placebo to bisoprolol condition. The bisoprolol-induced bradycardia was associated with higher burst/100 heart beats (P < .05) and bisoprolol did not affect burst/min (P = .80). Time domain BRS estimates were increased after bisoprolol (P < .05), while frequency domain ones did not change (P > .1). Oral bisoprolol induces differential effects on sympathetic burst frequency and incidence in normal participants. Peripheral sympathetic outflow over time is preserved as a result of an increased burst incidence, in the presence of a slower HR. Unchanged BP and HR and MSNA variability suggests that the larger burst incidence is not due to sympathetic activation.
Related Concept Videos
 01:27
Adrenergic Antagonists: Pharmacological Actions of β-Receptor Blockers
 01:28
Antihypertensive Drugs: Types of β-Blockers
 01:22
Heart Failure Drugs: β-Blockers
 01:25
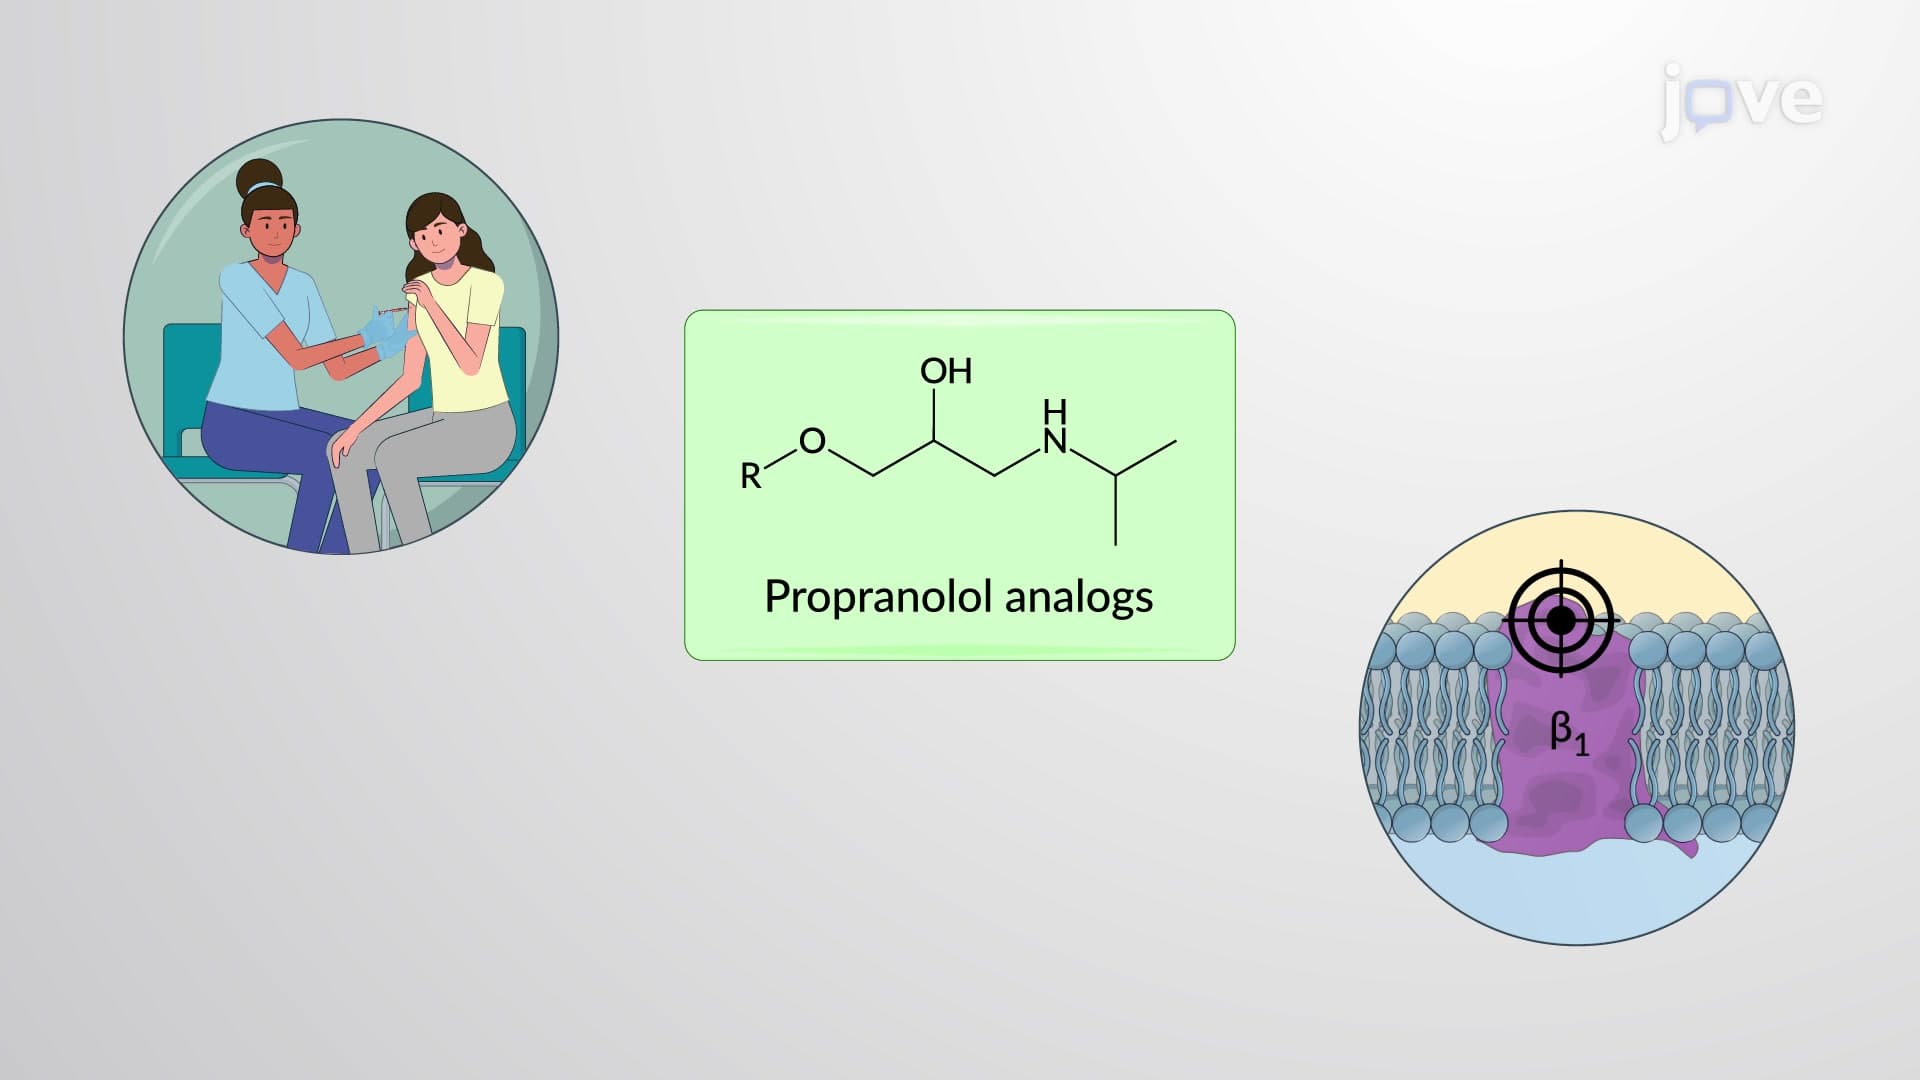
Adrenergic Antagonists: Chemistry and Classification of β-Receptor Blockers
 01:31
Adrenergic Antagonists: ɑ and β-Receptor Blockers
 01:17
Antihypertensive Drugs: Action of β1 Blockers