Related Experiment Video
Updated: Jun 18, 2026


The Rigid Tube as an Alternative in Controlling the Problematic Airway
Published on: June 6, 2020
Effect of cricoid force on airway calibre in children: a bronchoscopic assessment
R W M Walker1, R Ravi, K Haylett
1Royal Manchester Children's Hospital, Central Manchester NHS Foundation Trust, Oxford Road, Manchester M13 9WL, UK. robert.walker@cmft.nhs.uk

Insights
Cricoid force (CF) can obstruct a child's airway, even at forces below the recommended 30 N. Lower forces are needed for younger children to prevent airway compression.
Area of Science:
- Anesthesiology
- Pediatric Airway Management
- Emergency Medicine
Background:
- Cricoid force (CF) application during emergency inductions can lead to airway obstruction.
- Effective airway management in children requires understanding the forces that compromise the subglottic airway.
Purpose of the Study:
- To investigate the effect of cricoid force (CF) on the subglottic airway caliber in children.
- To determine the objective force required to cause significant subglottic airway compression in pediatric patients.
Main Methods:
- Studied 30 pediatric patients (3 months to 15 years) undergoing procedures requiring tracheal intubation.
- Assessed the impact of CF on subglottic airway dimensions.
- Objectively measured the force causing ≥50% distortion/compression of the subglottic airway.
Main Results:
- A linear relationship was observed between patient age/weight and the required CF.
- The mean force for airway compression was 10.5 N.
- Compressive forces ranged from 5 N in infants (<1 year) to 15-25 N in teenagers.
Conclusions:
- Significant subglottic airway compression in children can occur with forces well below the previously recommended 30 N.
- Age and weight are critical factors influencing the force needed to compress a child's airway.
- Current recommendations for CF may be excessive and pose a risk of airway compromise in pediatric patients.
Background:
Cricoid pressure or to be more exact cricoid force (CF) can cause airway obstruction and subsequent difficulty with airway management during an emergency induction.
Methods:
We studied 30 children with an age range of 3 months to 15 yr who presented for routine bronchoscopy or other surgical procedures requiring tracheal intubation. We looked at the effect of CF on the calibre of the subglottic airway and objectively measured the force which caused 50% or greater distortion/compression of the subglottic airway.
Results:
There was a linear relationship between both age and weight and CF. No patient suffered any adverse effects. Overall, the mean force required to compress the airway was 10.5 N. However, this force could be as low as 5 N in children <1 yr of age, and up to between 15 and 25 N in teenagers.
Conclusions:
Forces well below the recommended value of 30 N will cause significant compression/distortion of the airway in a child.
Related Concept Videos
 01:30
Assessment of Airway, Skin Color, and Use of Accessory Muscles
Introduction
The initial evaluation of a patient's respiratory system...
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:23
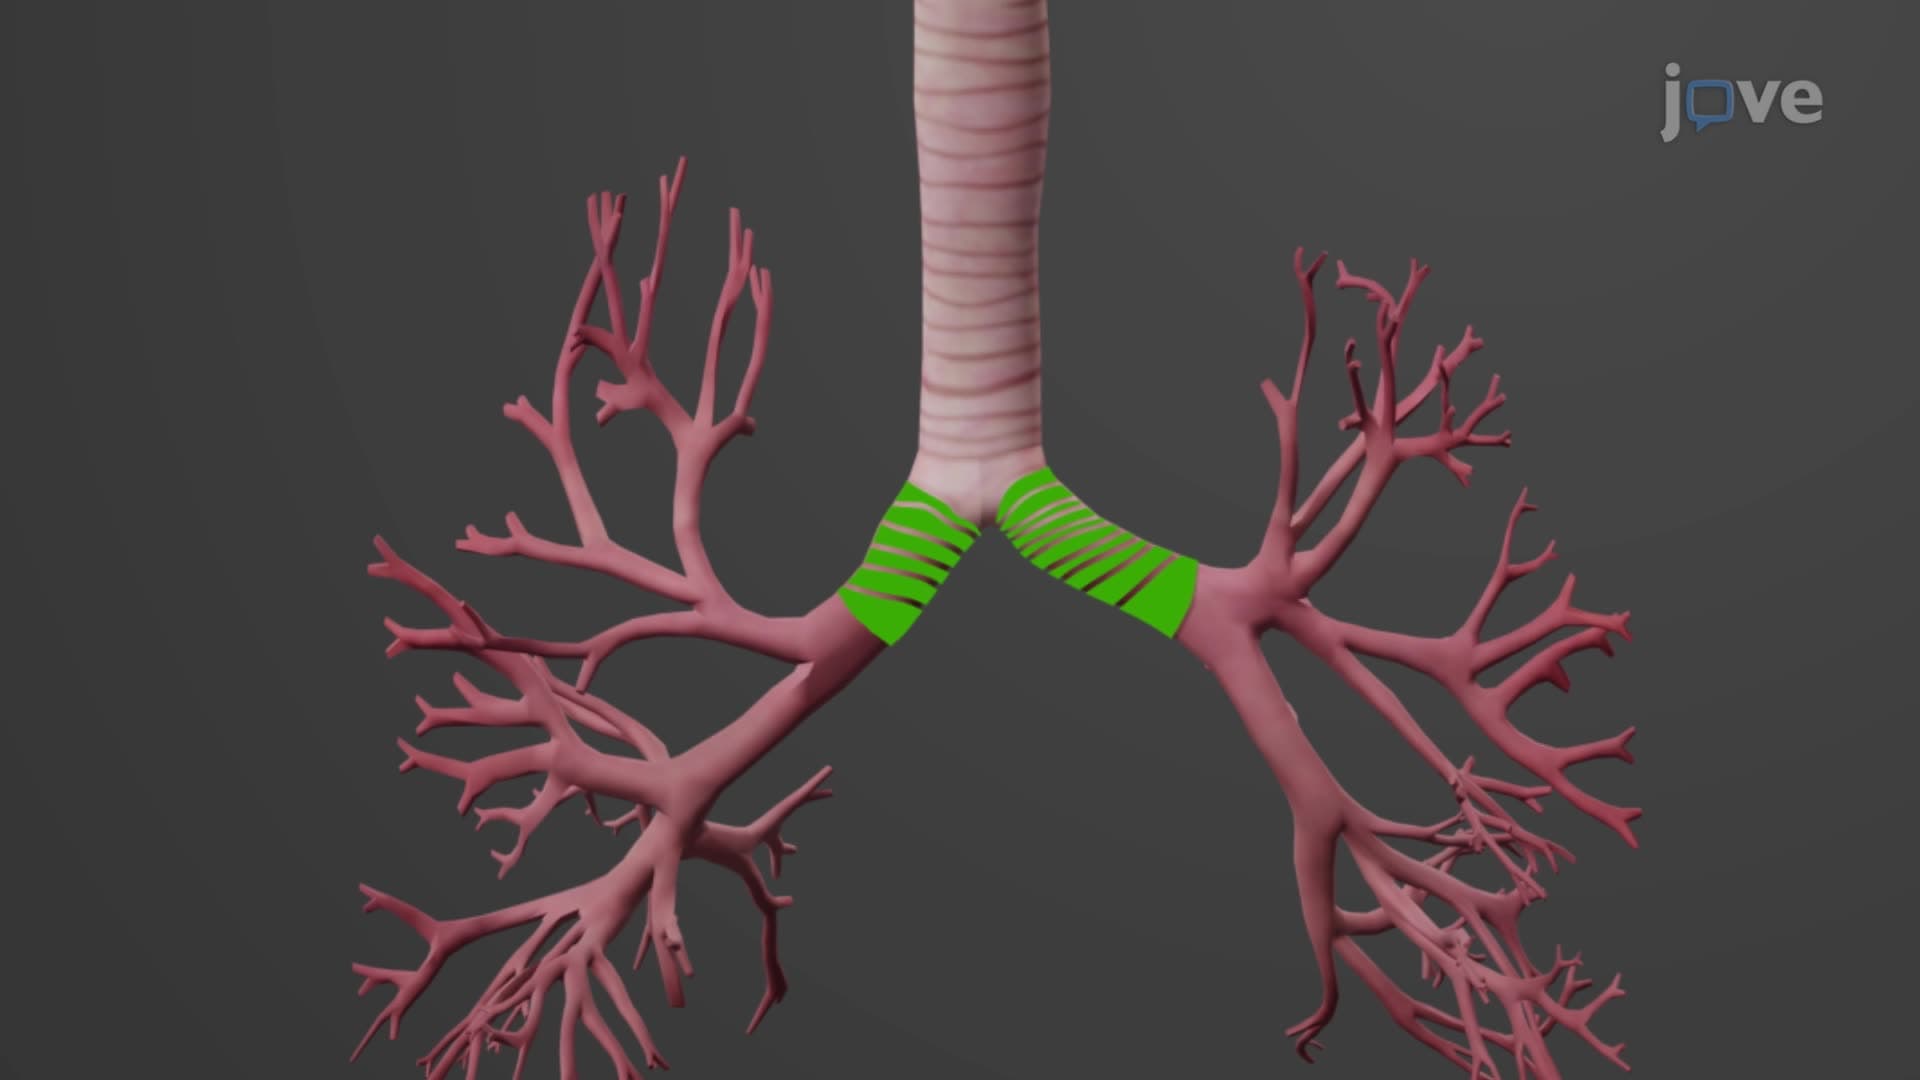
The Bronchial Tree
The trachea, commonly known as the windpipe, is a tube that connects the larynx (voice box) to the bronchi. At a point called the carina, it bifurcates into two primary bronchi. The right primary bronchus is wider, shorter, and more vertical than the left primary...
 01:24
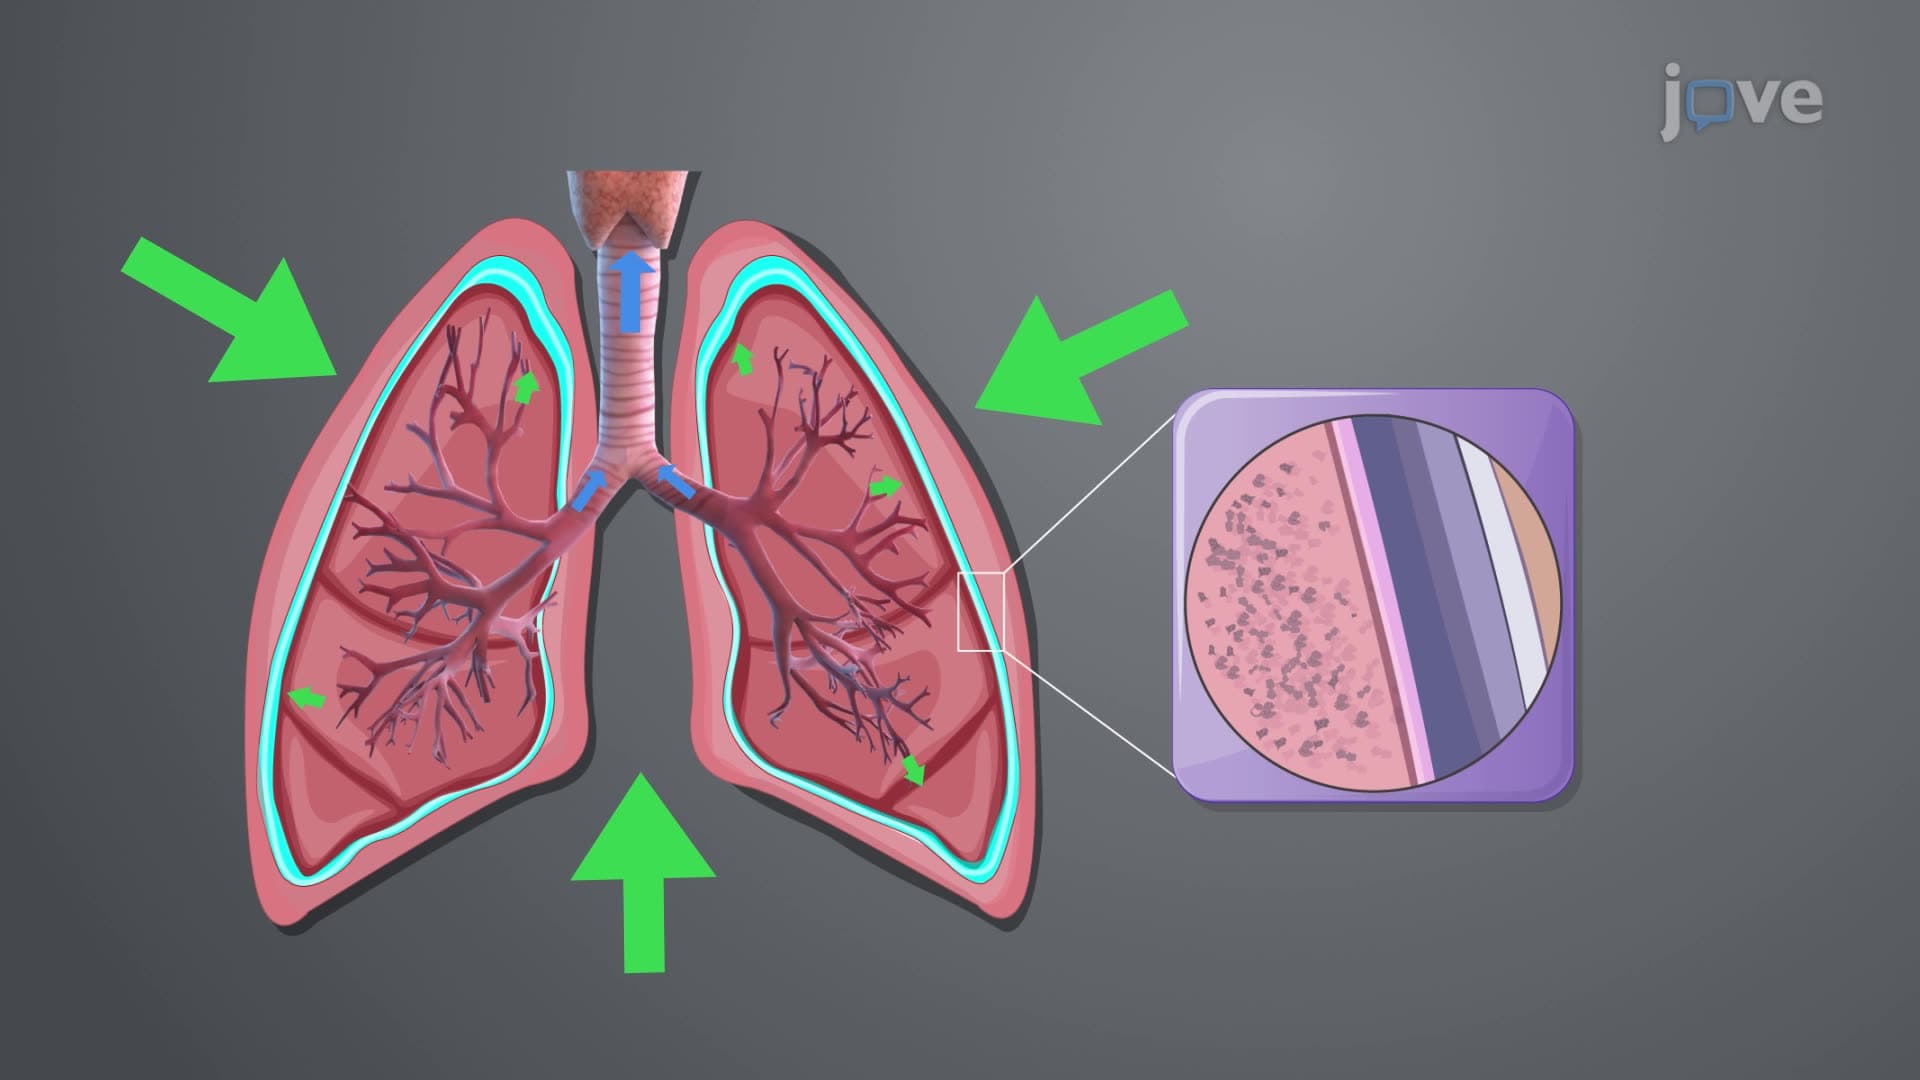
Pressure Relationships in Thoracic Cavity
Breathing Mechanisms
Both intra-alveolar and intrapleural pressures rely on specific lung properties. The ability to breathe—allowing air to enter the lungs during...
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:27
Physical Assessment of the Respiratory Tract II: Inspection
Chest Configuration
The chest configuration can...