Related Experiment Video
Updated: Jun 17, 2026


Murine Ileocolic Bowel Resection with Primary Anastomosis
Published on: October 29, 2014
Intestinal intussusception
1Physicians Regional Medical Center, Medical Surgical Specialists, Naples, FL 34119, USA. susan.cera@pmc.hma.org

Insights
Intussusception, or bowel telescoping, differs in children and adults. Pediatric cases are often idiopathic and treated nonoperatively, while adult intussusception requires surgery due to lead points, posing diagnostic challenges.
Area of Science:
- Gastroenterology
- Pediatric Surgery
- Surgical Oncology
Background:
- Intussusception involves bowel telescoping, with distinct causes and management in pediatric versus adult patients.
- Pediatric intussusception is frequently idiopathic, often ileocolic, linked to developmental and infectious factors.
- Adult intussusception typically arises from a lead point (mucosal, intramural, or extrinsic) causing bowel invagination.
Purpose of the Study:
- To delineate the differing etiologies, diagnostic approaches, and treatment strategies for intussusception in pediatric and adult populations.
- To highlight the diagnostic challenges and controversial intraoperative management in adult intussusception.
- To contrast the standardized nonoperative approach in children with the surgical necessity in adults.
Main Methods:
- Review of existing literature on pediatric and adult intussusception.
- Comparative analysis of diagnostic modalities and treatment outcomes.
- Examination of etiological factors, including lead points in adults and idiopathic causes in children.
Main Results:
- Pediatric intussusception commonly presents as ileocolic and is managed with nonoperative reduction (air/contrast enemas).
- Adult intussusception is associated with a lead point, necessitating surgical intervention.
- Diagnosis in adults is challenging preoperatively, and intraoperative management remains a subject of debate.
Conclusions:
- Intussusception management requires distinct strategies based on patient age due to differing underlying causes and diagnostic considerations.
- Early diagnosis and appropriate intervention are crucial for both pediatric and adult intussusception.
- Further research may clarify optimal intraoperative management for adult intussusception.
Abstract:
Intussusception is defined as the invagination of one portion of the bowel into an immediately adjacent portion. Etiology, symptoms, diagnosis, and treatment are different in the pediatric and adult populations. In the pediatric population, most cases are idiopathic and result in the common scenario of ileocolic intussusception. Factors involved in causation include anatomic features of the developing gastrointestinal tract and infectious influences. In adults, the intussusceptum is typically the result of a mucosal, intramural, or extrinsic lead point that acts as a focal area of traction pulling the proximal portion of bowel into the peristalsing distal portion. The diagnosis and management in the pediatric population is relatively standardized with nonoperative reduction via air or contrast enemas attempted first. In the adult population, intussusception presents a preoperative diagnostic challenge; although surgical intervention is mandatory, intraoperative management remains controversial.


Related Concept Videos
 01:29
Intestinal Obstruction I: Introduction
 01:07
Intestinal Obstruction II: Pathophysiology
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:09
Large Intestine
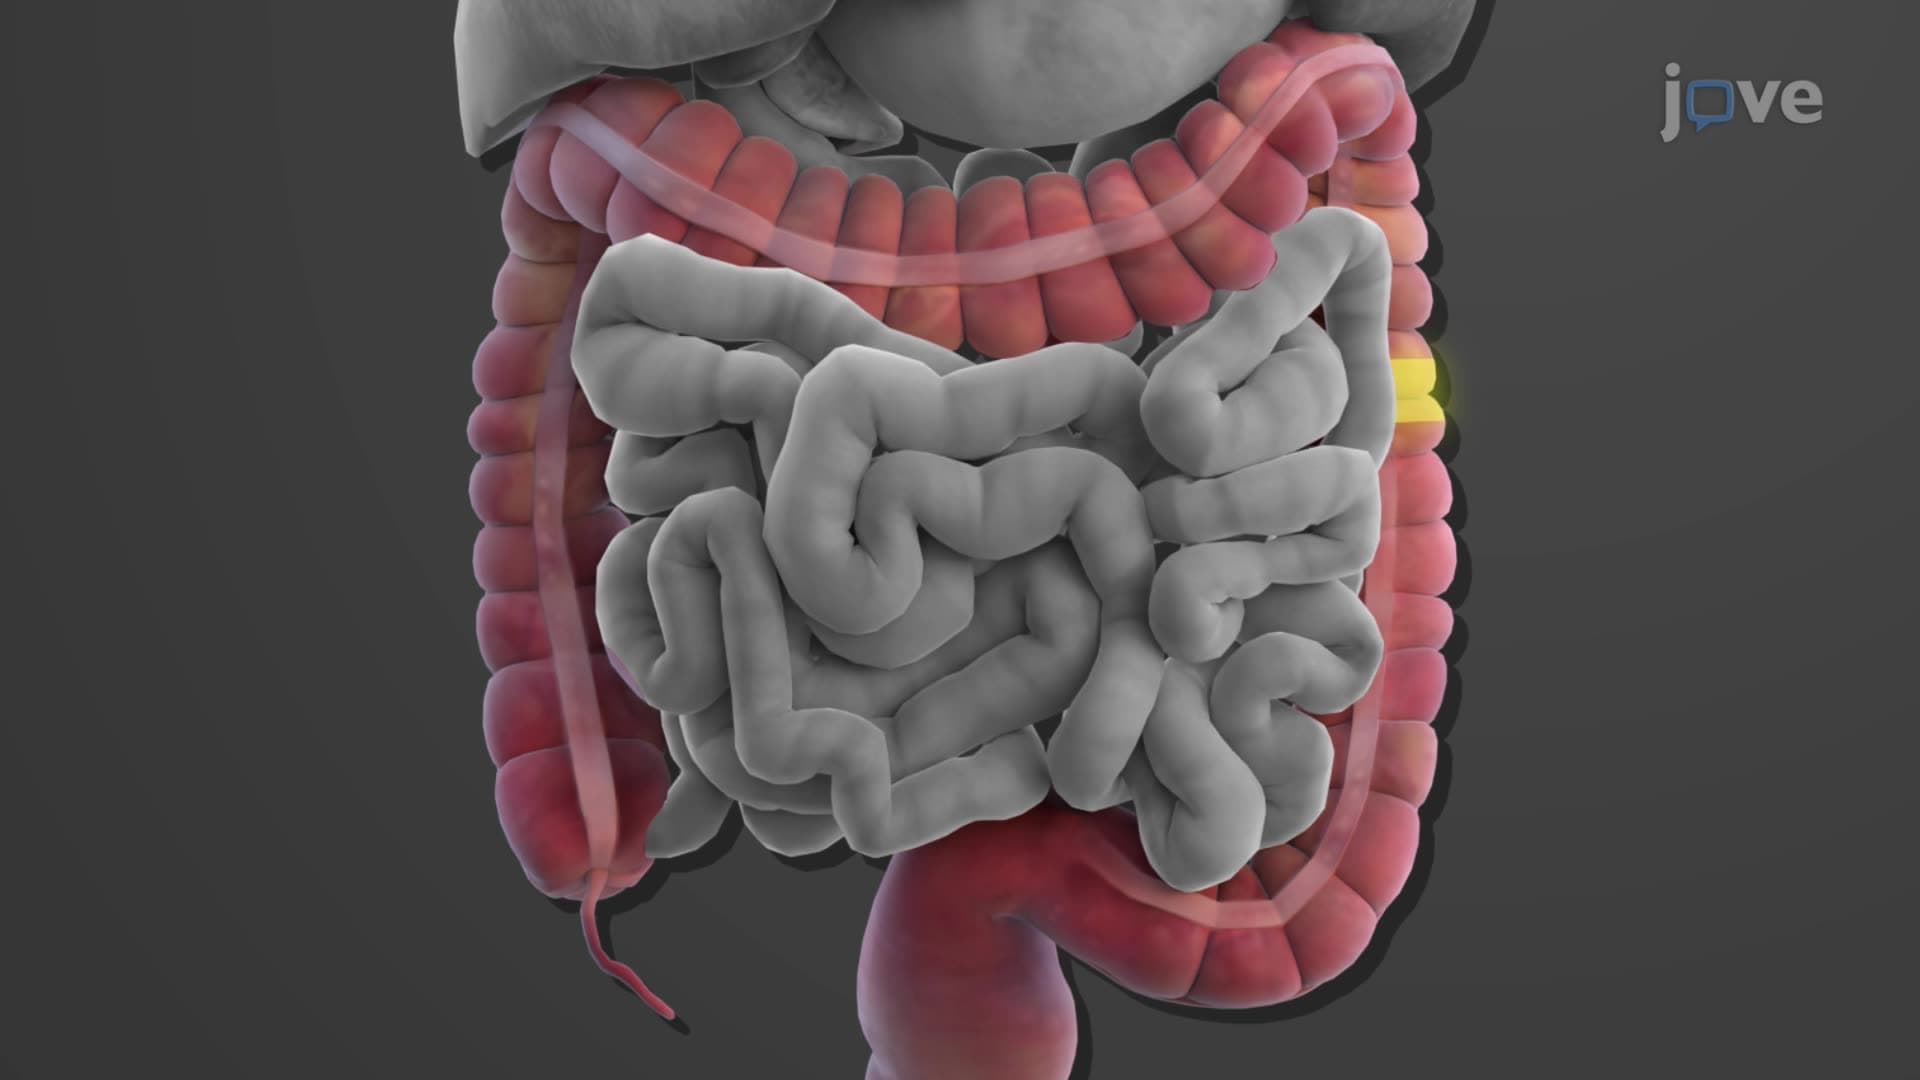
The ileocecal sphincter, a mucous membrane fold, guards the opening from the ileum to the large intestine. This valve permits material from the small intestine to pass into the large intestine. Attached to the ileocecal valve is the cecum. This small pouch, approximately 6 cm long, has a twisted, coiled tube known as...
 01:23
Anatomy of the Intestines
Small Intestines
The small intestine is an ~7 meter-long tube with an inner diameter of just 2.5 cm. Since most nutrients are absorbed here, the inner lining of the small...
 01:26
Inflammatory Bowel Disease I: Introduction