Related Experiment Video
Updated: Jun 16, 2026
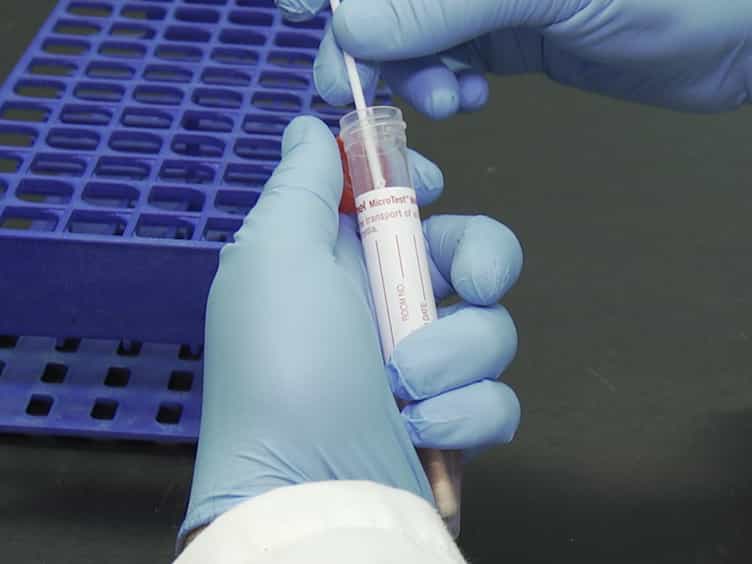

Rapid Molecular Detection and Differentiation of Influenza Viruses A and B
Published on: January 30, 2017
Performance of a rapid influenza test in children during the H1N1 2009 influenza a outbreak
Andrea T Cruz1, Gail J Demmler-Harrison, A Chantal Caviness
1Baylor College of Medicine, 6621 Fannin St, Suite A210, MC 1-1481, Houston, TX 77030, USA. acruz@bcm.edu

Insights
Rapid influenza diagnostic tests (RIDTs) show poor sensitivity but high specificity for H1N1 detection in children. A negative RIDT result does not rule out H1N1 infection in pediatric patients.
Area of Science:
- Pediatric Infectious Diseases
- Diagnostic Accuracy Studies
- Virology
Background:
- Influenza A H1N1 virus poses a significant threat to pediatric populations.
- Accurate and rapid diagnostic tools are crucial for timely clinical management of influenza in children.
- Rapid influenza diagnostic tests (RIDTs) offer potential for quick point-of-care diagnosis.
Purpose of the Study:
- To assess the diagnostic performance of a specific RIDT (BinaxNOW) for detecting H1N1 2009 influenza A virus in pediatric respiratory samples.
- To compare the RIDT's accuracy against established methods: real-time reverse-transcriptase polymerase chain reaction (rRT-PCR) and viral culture.
- To determine the sensitivity, specificity, and likelihood ratios of the RIDT in a pediatric cohort.
Main Methods:
- A cross-sectional diagnostic-accuracy study was conducted at a tertiary care children's hospital.
- Respiratory samples from pediatric patients with known RIDT, rRT-PCR, and viral culture results were analyzed.
- Statistical analysis included calculation of sensitivity, specificity, and likelihood ratios (LRs) using rRT-PCR and viral culture as reference standards.
Main Results:
- Out of 3030 specimens, the RIDT demonstrated an overall sensitivity of 45% and specificity of 98.6% when compared to rRT-PCR.
- Positive and negative likelihood ratios were 32.9 and 0.56, respectively, indicating high accuracy for positive results.
- RIDT sensitivity was notably higher in infants and children younger than 2 years compared to older children.
Conclusions:
- The RIDT exhibits excellent specificity but limited sensitivity for H1N1 detection in pediatric respiratory samples.
- A positive RIDT result strongly suggests H1N1 infection in children, while a negative result cannot exclude it.
- Empiric antiviral therapy should be considered for high-risk pediatric patients with influenza-like illness and negative RIDT results during peak influenza seasons.
Objective:
To evaluate the performance of a rapid influenza diagnostic test (RIDT) in detecting H1N1 2009 influenza A virus in respiratory samples from pediatric patients in comparison to that of real-time reverse-transcriptase polymerase chain reaction (rRT-PCR) and viral culture. Methodology. This was a cross-sectional diagnostic-accuracy study conducted at a tertiary care children's hospital. Patients for whom the RIDT (BinaxNOW [Binax, Inc, Portland, ME]), viral culture, and rRT-PCR results were known were included. Sensitivity, specificity, and likelihood ratios (LRs) were calculated.
Results:
A total of 3030 specimens had RIDT results paired with both rRT-PCR and viral culture results. With rRT-PCR as the reference, overall test sensitivity was 45% (95% confidence interval [CI]: 43.3%-46.3%) and specificity was 98.6% (95% CI: 98.1%-99%). Positive and negative LRs were 32.9 (95% CI: 22.9-45.4) and 0.56 (95% CI: 0.54-0.58), respectively. RIDT sensitivity was significantly higher in young infants and children younger than 2 years than in older children. Using viral culture as the reference standard, RIDT sensitivity was 55.5% (95% CI: 51.9%-95.6%) and specificity was 95.6% (95% CI: 95%-96.1%). The positive and negative LRs were 12.6 and 0.47, respectively.
Conclusions:
The RIDT had relatively poor sensitivity but excellent specificity in this consecutive series of respiratory specimens obtained from pediatric patients. Although a positive RIDT result was highly accurate in predicting infection with influenza type A H1N1 2009 in children, a negative RIDT result did not preclude a child having H1N1. Therefore, for children at high risk with influenza-like illnesses during high-prevalence periods of influenza, empiric initiation of antiviral therapy should be considered for patients with a negative RIDT result.


