Related Experiment Video
Updated: Jun 16, 2026

Ultrasound-guided Botulinum Toxin-A Injections: A Method of Treating Sialorrhea
Published on: November 9, 2016
Botulinum neurotoxin type A injections for vaginismus secondary to vulvar vestibulitis syndrome
Laura Bertolasi1, Emma Frasson, Jee Yun Cappelletti
1From the Department of Neurological Sciences and Vision, Section of Clinical Neurology, University of Verona, Italy; Departments of Neurology and Management Control, ULSS15 Cittadella Hospital, Padua, Italy; and Centre of Gynaecology and Medical Sexuology, San Raffaele Resnati Hospital, Milan, Italy.

Objective:
To investigate whether botulinum neurotoxin type A improves vaginismus and study its efficacy with repeated treatments.
Methods:
Outpatients were referred because standard cognitive-behavioral and medical treatment for vaginismus and vulvar vestibular syndrome failed. From this group, we prospectively recruited consecutive women (n=39) whose diagnostic electromyogram (EMG) recordings from the levator ani muscle showed hyperactivity at rest and reduced inhibition during straining. These women were followed for a mean (+/-standard deviation) of 105 (+/-50) weeks. Recruited patients underwent repeated cycles of botulinum neurotoxin type A injected into the levator ani under EMG guidance and EMG monitoring thereafter. At enrollment and 4 weeks after each cycle, women were asked about sexual intercourse; underwent EMG evaluation and examinations to grade vaginal resistance according to Lamont; and completed a visual analog scale (VAS) for pain, the Female Sexual Function Index Scale, a quality-of-life questionnaire (Short-Form 12 Health Survey), and bowel and bladder symptom assessment.
Results:
At 4 weeks after the first botulinum neurotoxin type A cycle, the primary outcome measures (the possibility of having sexual intercourse, and levator ani EMG hyperactivity) both improved, as did the secondary outcomes, Lamont scores, VAS, Female Sexual Function Index Scales, Short-Form 12 Health Survey, and bowel-bladder symptoms. These benefits persisted through later cycles. When follow-up ended, 63.2% of the patients completely recovered from vaginismus and vulvar vestibular syndrome, 15.4% still needed reinjections (censored), and 15.4% had dropped out.
Conclusion:
Botulinum neurotoxin type A is an effective treatment option for vaginismus secondary to vulvar vestibular syndrome refractory to standard cognitive-behavioral and medical management. After patients received botulinum neurotoxin type A, their sexual activity improved and reinjections provided sustained benefits.
Level Of Evidence:
III.

Related Concept Videos
 01:22
Botulism
 01:26
Directly Acting Muscle Relaxants: Dantrolene and Botulinum Toxin
The binding of dantrolene to the RYR1...
 01:31
Skeletal Muscle Relaxants: Therapeutic Uses
 01:29
Spasmolytic Agents: Chemical Classification
A major class of centrally acting spasmolytics is the α2-agonist, such as tizanidine. These drugs bind to α2-adrenoceptors, inhibiting the release of the excitatory neurotransmitter glutamate. They also promote...
 01:24
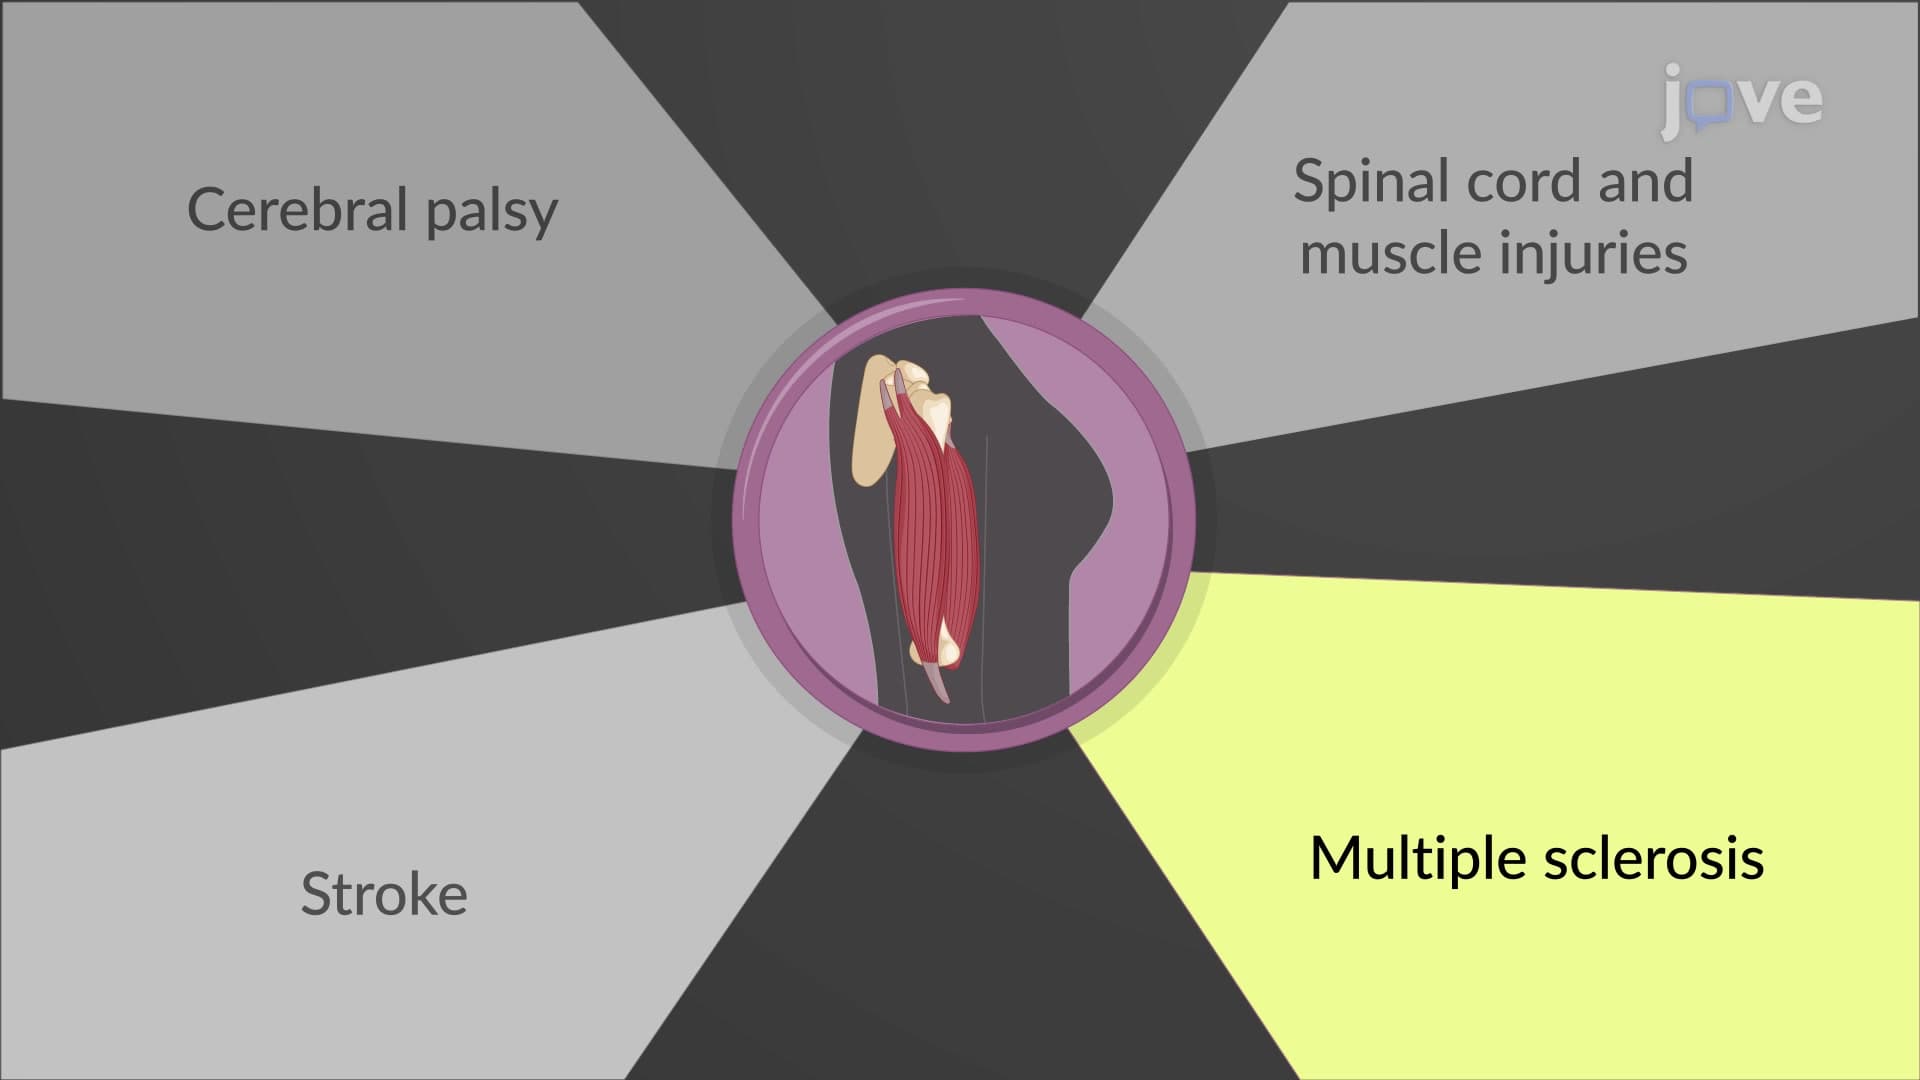
Centrally Acting Muscle Relaxants: Therapeutic Uses
Centrally acting drugs are classified into spasmolytic and antispasmodic drugs. Spasmolytic drugs such as baclofen, diazepam, and tizanidine inhibit spinal motor neurons and decrease muscle tone. Spasmolytic drugs are administered for severe and chronic spasms due to multiple sclerosis, cerebral palsy, stroke, and spinal cord and muscle injuries. However,...
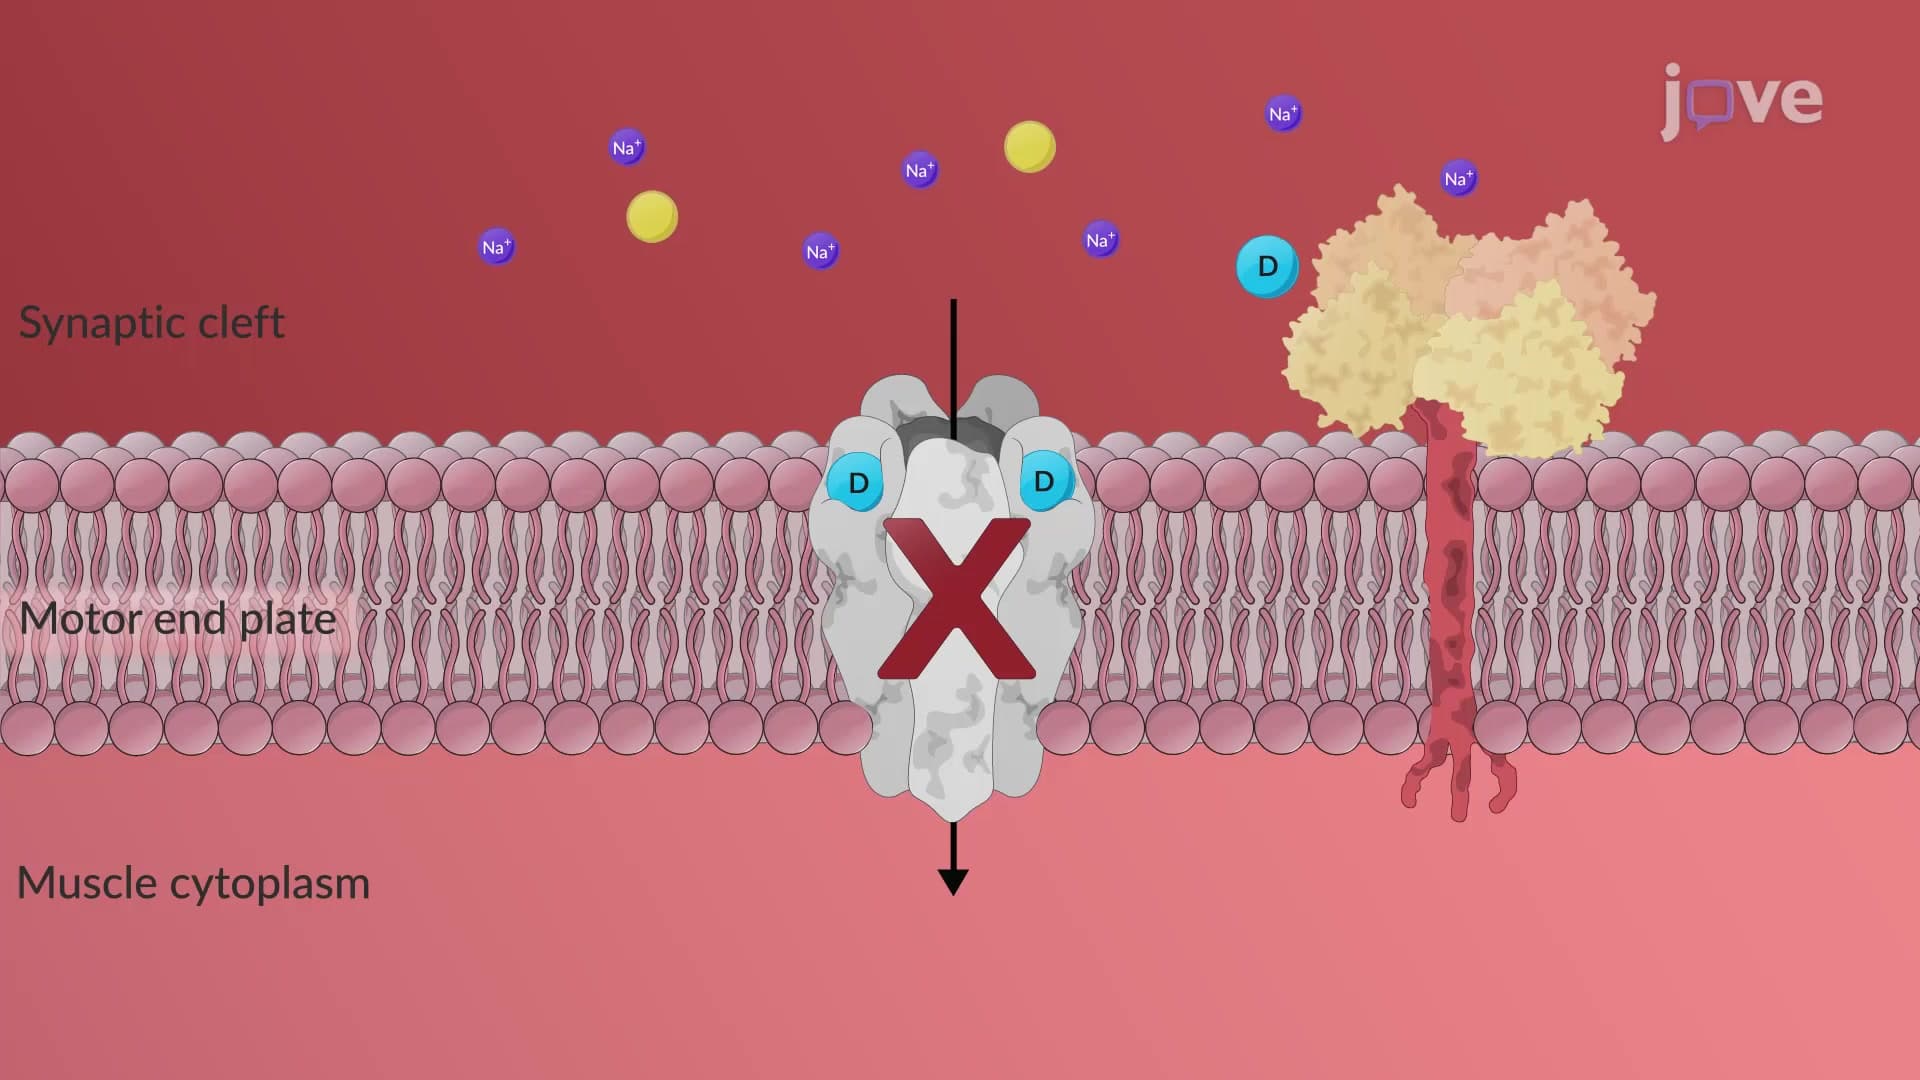 01:17
Nondepolarizing (Competitive) Neuromuscular Blockers: Mechanism of Action
Competitive antagonists prevent acetylcholine from binding to its receptor, inhibiting membrane depolarization. Without conformational changes or intrinsic...