Related Experiment Video
Updated: Jun 15, 2026
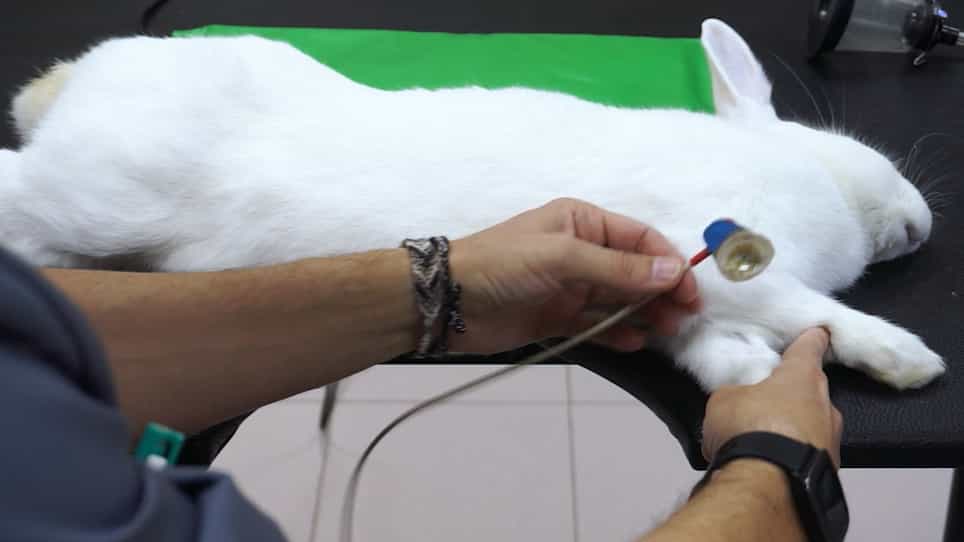

Transthoracic Echocardiographic Examination in the Rabbit Model
Published on: June 1, 2019
Cardiac lymphatic obstruction impairs left ventricular function and increases plasma endothelin-1 and angiotensin II
1Department of Cardiology, Liaocheng People's Hospital, Liaocheng City, Shandong Province, PR China.

The treatment of end-stage heart failure can include heart transplantation. During this procedure, cardiac lymphatics are disrupted, which has been demonstrated in animal models to alter left ventricular function, and this compromise itself can cause an increase in endothelin-1 and angiotensin II. We undertook a study in rabbits to assess the effect of cardiac lymphatic obstruction on left ventricular function and plasma levels of endothelin-1 and angiotensin II. Sixty-three New Zealand white rabbits were divided into study (n = 41) and control (n = 22) groups. Plasma levels of endothelin and angiotensin II were measured before, and at 3, 7, 14, 30, 90 and 180 days following the obstruction of cardiac lymphatic vessels. Left ventricular function was assessed by echocardiography. Six months following the surgery, 18 study and 6 control animals survived. In the study group, a significant decrease was seen in left ventricular ejection fraction within the first three months following the lymphatic obstruction (0.76 +/- 0.04 vs 0.72 +/- 0.01, p < 0.01). Levels of plasma endothelin-1 and angiotensin II were elevated following ligation of cardiac lymphatic vessels with a peak between 3-7 days following lymphatic obstruction (all p < 0.05). Plasma endothelin-1 and angiotensin II began to decline 14 days after lymphatic obstruction and returned to almost baseline levels in 6 months. The left ventricular ejection fraction, plasma endothelin-1 and angiotensin in the control group remained unchanged (all p > 0.05). We conclude that cardiac lymphatic obstruction reduces left ventricular function in the first three months following obstruction. Cardiac lymphatic obstruction also increases plasma levels of endothelin-1 and angiotensin II. The clinical significance of these transitory changes requires further investigation.
The treatment of end-stage heart failure can include heart transplantation. During this procedure, cardiac lymphatics are disrupted, which has been demonstrated in animal models to alter left ventricular function, and this compromise itself can cause an increase in endothelin-1 and angiotensin II. We undertook a study in rabbits to assess the effect of cardiac lymphatic obstruction on left ventricular function and plasma levels of endothelin-1 and angiotensin II. Sixty-three New Zealand white rabbits were divided into study (n = 41) and control (n = 22) groups. Plasma levels of endothelin and angiotensin II were measured before, and at 3, 7, 14, 30, 90 and 180 days following the obstruction of cardiac lymphatic vessels. Left ventricular function was assessed by echocardiography. Six months following the surgery, 18 study and 6 control animals survived. In the study group, a significant decrease was seen in left ventricular ejection fraction within the first three months following the lymphatic obstruction (0.76 +/- 0.04 vs 0.72 +/- 0.01, p < 0.01). Levels of plasma endothelin-1 and angiotensin II were elevated following ligation of cardiac lymphatic vessels with a peak between 3-7 days following lymphatic obstruction (all p < 0.05). Plasma endothelin-1 and angiotensin II began to decline 14 days after lymphatic obstruction and returned to almost baseline levels in 6 months. The left ventricular ejection fraction, plasma endothelin-1 and angiotensin in the control group remained unchanged (all p > 0.05). We conclude that cardiac lymphatic obstruction reduces left ventricular function in the first three months following obstruction. Cardiac lymphatic obstruction also increases plasma levels of endothelin-1 and angiotensin II. The clinical significance of these transitory changes requires further investigation.
Related Concept Videos
 01:29
Heart Failure II: Pathophysiology
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send blood...
 01:22
Mitral Stenosis I: Introduction