Related Experiment Video
Updated: Jun 15, 2026


Generation of Hypoparathyroid Rats via Carbon-Nanoparticle-Assisted Parathyroidectomy
Published on: July 14, 2023
Influence of morbid obesity on parathyroidectomy outcomes in primary hyperparathyroidism
Susan C Pitt1, Rajarajan Panneerselvan, Rebecca S Sippel
1Section of Endocrine Surgery, Department of Surgery, University of Wisconsin, Madison, WI, USA.

Background:
We sought to evaluate the influence of morbid obesity in patients undergoing parathyroidectomy for primary hyperparathyroidism (pHPT).
Methods:
All patients with pHPT who underwent parathyroidectomy at a single institution between July 2002 and October 2008 were included. Body mass index (BMI), laboratory values, operative findings, and outcomes were examined.
Results:
Two hundred thirteen of the 776 patients identified (28%) were morbidly obese (BMI>or=35 kg/m2). When compared with nonmorbidly obese patients, the morbidly obese patients were younger, had higher preoperative intact parathyroid hormone (iPTH) levels, heavier parathyroids, and required overnight stay more often (P<.05 for all). However, the rates of complications, eucalcemia, and recurrence were similar for all patients.
Conclusion:
In this study, more than a quarter of the patients who underwent parathyroidectomy for pHPT were morbidly obese and had significantly higher preoperative iPTH levels, heavier parathyroids, and longer hospital stay but similar rates of complications and operative success.
Related Concept Videos
 01:27
Hyperthyroidism II: Pathophysiology
 01:25
Hyperthyroidism I: Introduction
 01:25
Pharmacokinetics in Obese Patients: Drug Absorption and Distribution
 01:28
Cardiomyopathy VII: Pre and Post Operative Nursing Management
 00:59
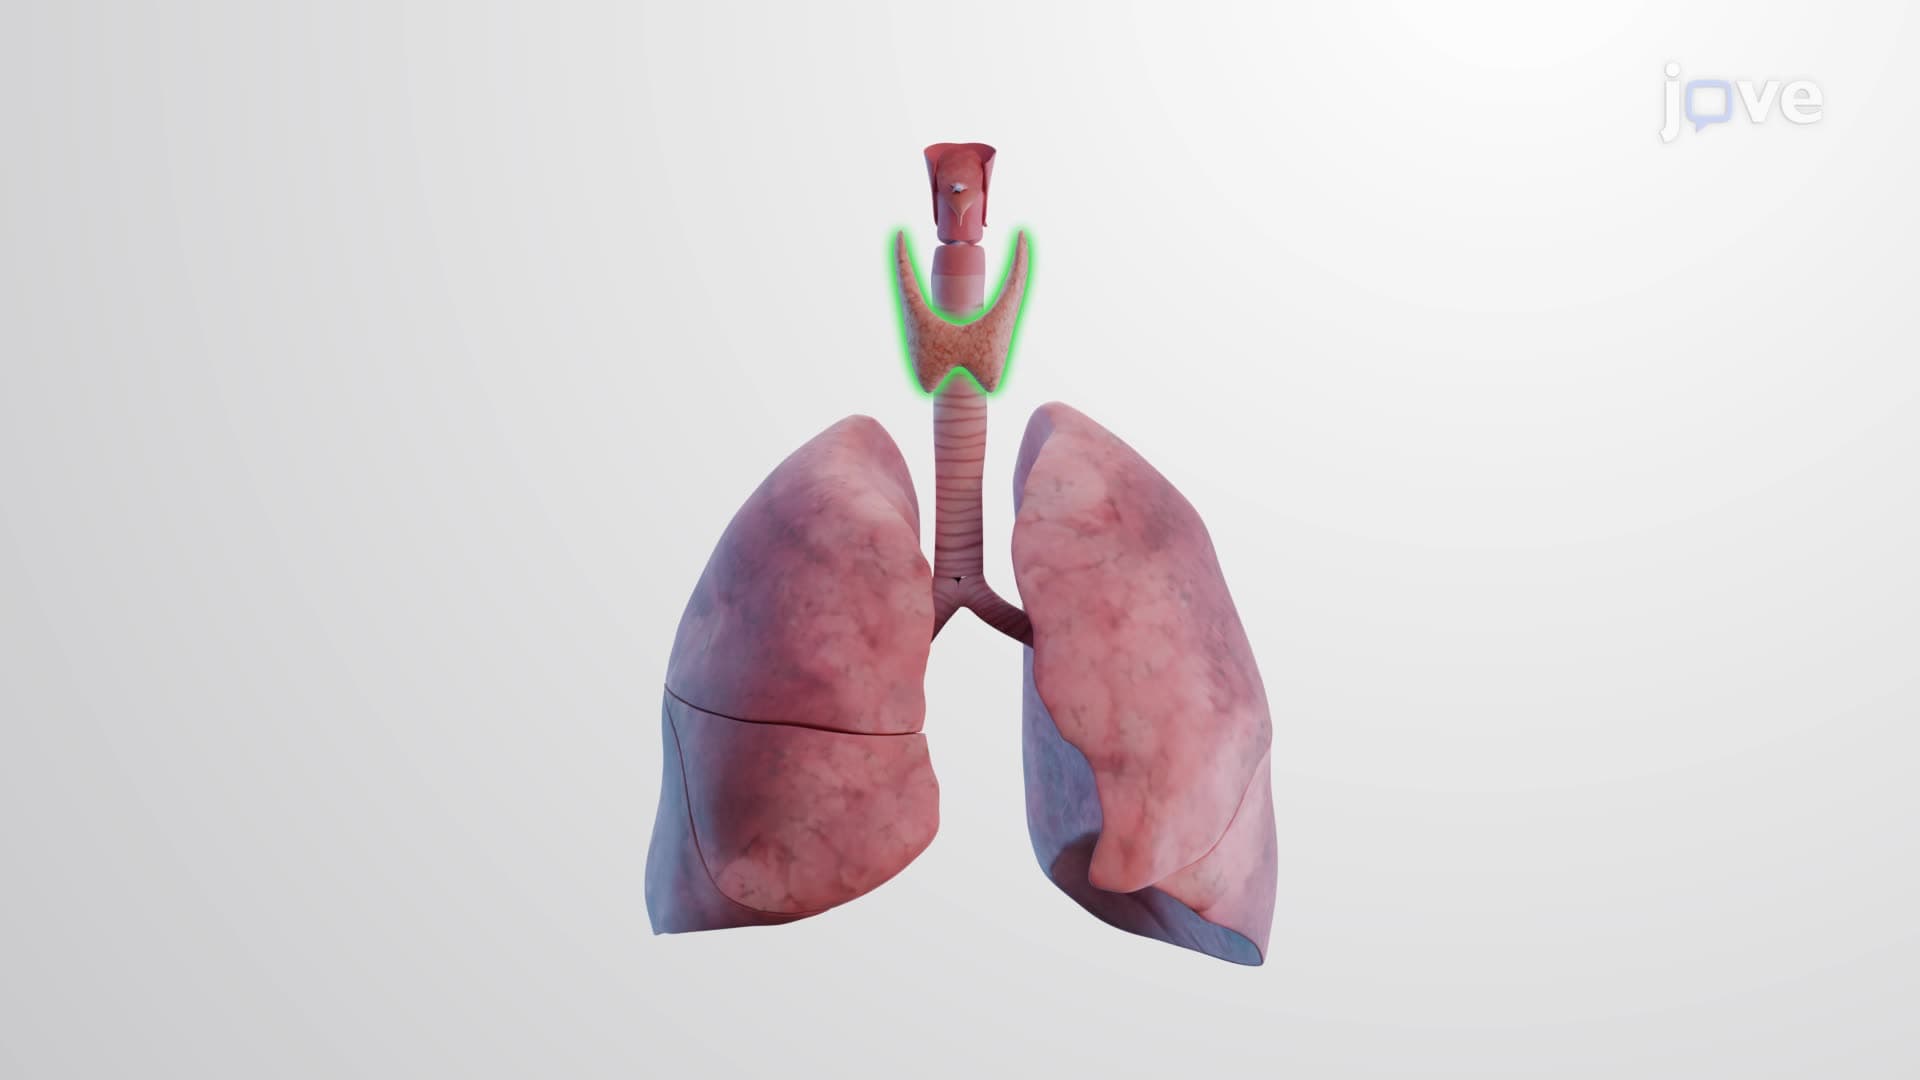
The Parathyroid Glands
Oxyphil cells, whose functions remain elusive, emerge during late puberty, adding a layer of complexity to the parathyroid gland's intricacies. In contrast, principal parathyroid cells undertake a vital role by producing...
 01:24
Graves Disease II: Pathophysiology