Related Experiment Video
Updated: Jun 14, 2026

Continuous Manual Exchange Transfusion for Patients with Sickle Cell Disease: An Efficient Method to Avoid Iron Overload
Published on: March 14, 2017
Patterns of liver iron accumulation in patients with sickle cell disease and thalassemia with iron overload
Jane S Hankins1, Matthew P Smeltzer, M Beth McCarville
1Department of Hematology, St. Jude Children's Research Hospital, Memphis, TN 38105-3678, USA. jane.hankins@stjude.org

The rate and pattern of iron deposition and accumulation are important determinants of liver damage in chronically transfused patients. To investigate iron distribution patterns at various tissue iron concentrations, effects of chelation on hepatic iron compartmentalization, and differences between patients with sickle cell disease (SCD) and thalassemia major (TM), we prospectively investigated hepatic histologic and biochemical findings in 44 patients with iron overload (35 SCD and 9 TM). The median hepatic iron content (HIC) in patients with TM and SCD was similar at 12.9 and 10.3 mg Fe/g dry weight, respectively (P = 0.73), but patients with SCD had significantly less hepatic fibrosis and inflammation (P < 0.05), less hepatic injury, and significantly less blood exposure. Patients with SCD had predominantly sinusoidal iron deposition, but hepatocyte iron deposition was observed even at low HIC. Chelated patients had more hepatocyte and portal tract iron than non-chelated ones, but similar sinusoidal iron deposition. These data suggest that iron deposition in patients with SCD generally follows the traditional pattern of transfusional iron overload; however, parenchymal hepatocyte deposition also occurs early and chelation removes iron preferentially from the reticuloendothelium. Pathophysiological and genetic differences affecting iron deposition and accumulation in SCD and TM warrants further investigation.
The rate and pattern of iron deposition and accumulation are important determinants of liver damage in chronically transfused patients. To investigate iron distribution patterns at various tissue iron concentrations, effects of chelation on hepatic iron compartmentalization, and differences between patients with sickle cell disease (SCD) and thalassemia major (TM), we prospectively investigated hepatic histologic and biochemical findings in 44 patients with iron overload (35 SCD and 9 TM). The median hepatic iron content (HIC) in patients with TM and SCD was similar at 12.9 and 10.3 mg Fe/g dry weight, respectively (P = 0.73), but patients with SCD had significantly less hepatic fibrosis and inflammation (P < 0.05), less hepatic injury, and significantly less blood exposure. Patients with SCD had predominantly sinusoidal iron deposition, but hepatocyte iron deposition was observed even at low HIC. Chelated patients had more hepatocyte and portal tract iron than non-chelated ones, but similar sinusoidal iron deposition. These data suggest that iron deposition in patients with SCD generally follows the traditional pattern of transfusional iron overload; however, parenchymal hepatocyte deposition also occurs early and chelation removes iron preferentially from the reticuloendothelium. Pathophysiological and genetic differences affecting iron deposition and accumulation in SCD and TM warrants further investigation.

Related Concept Videos
 01:27
Disorders of Erythrocytes
Erythrocyte disorders can be broadly categorized into two main types: anemic and polycythemic conditions.
A low oxygen-carrying capacity of the blood due to the loss, lower production, or destruction of erythrocytes is termed anemia. Hemorrhagic anemia, for example, occurs when bleeding from an external wound or internal ulcer reduces erythrocyte counts.
On the other...
 01:22
Portal Hypertension
 01:23
Cirrhosis I: Introduction
 01:24
Cirrhosis II: Pathophysiology
 01:27
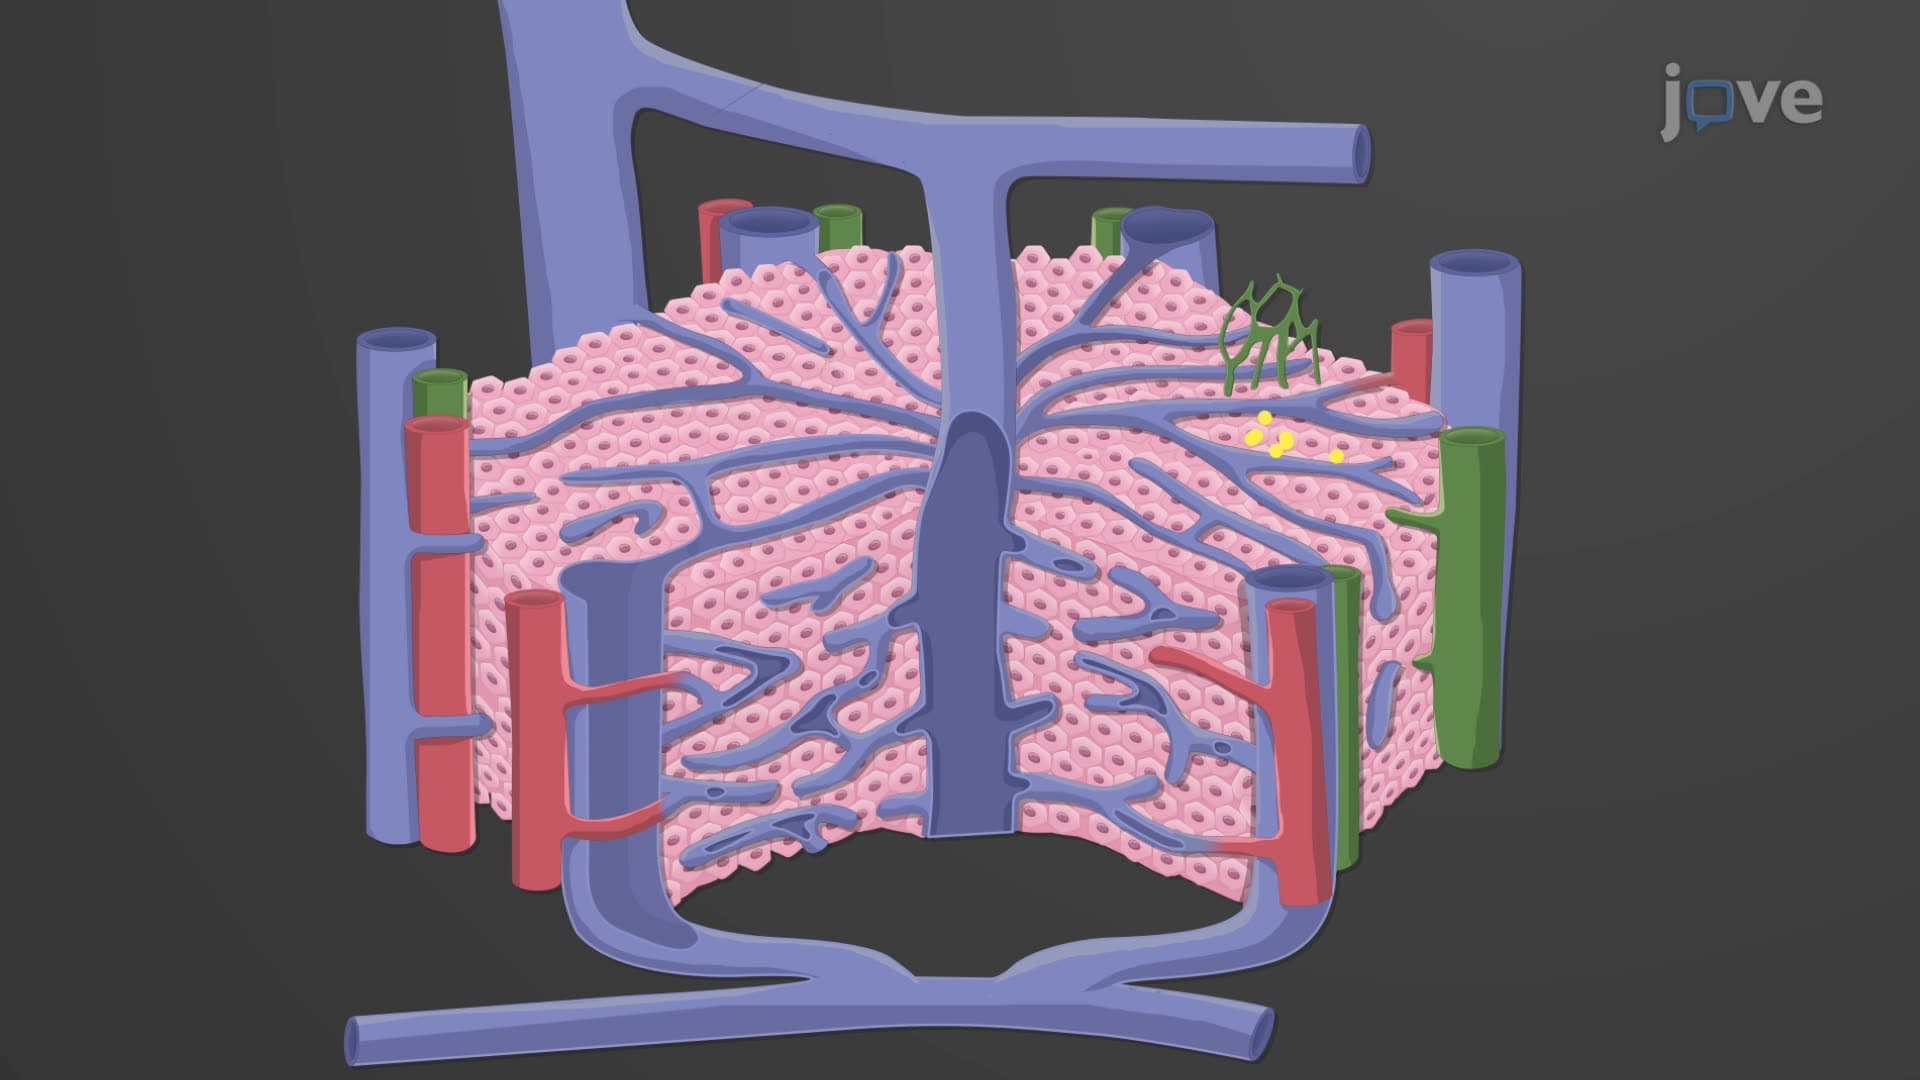
Liver Histology
Hepatocytes perform a variety of essential functions. They secrete...
 01:22
Lifecycle of Erythrocytes
The resident phagocytic macrophages deal with these damaged cells by engulfing them and separating their globin and heme groups.