Related Experiment Video
Updated: Jun 14, 2026

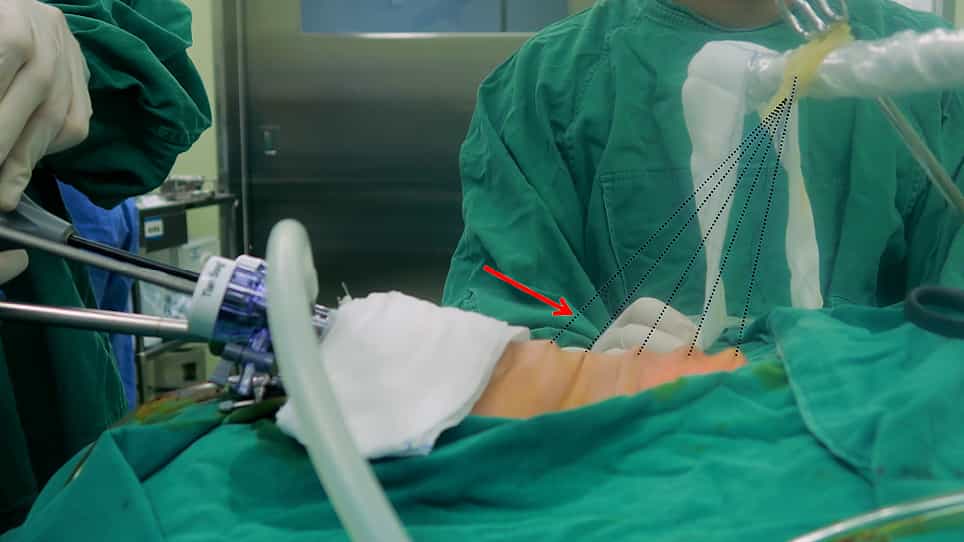
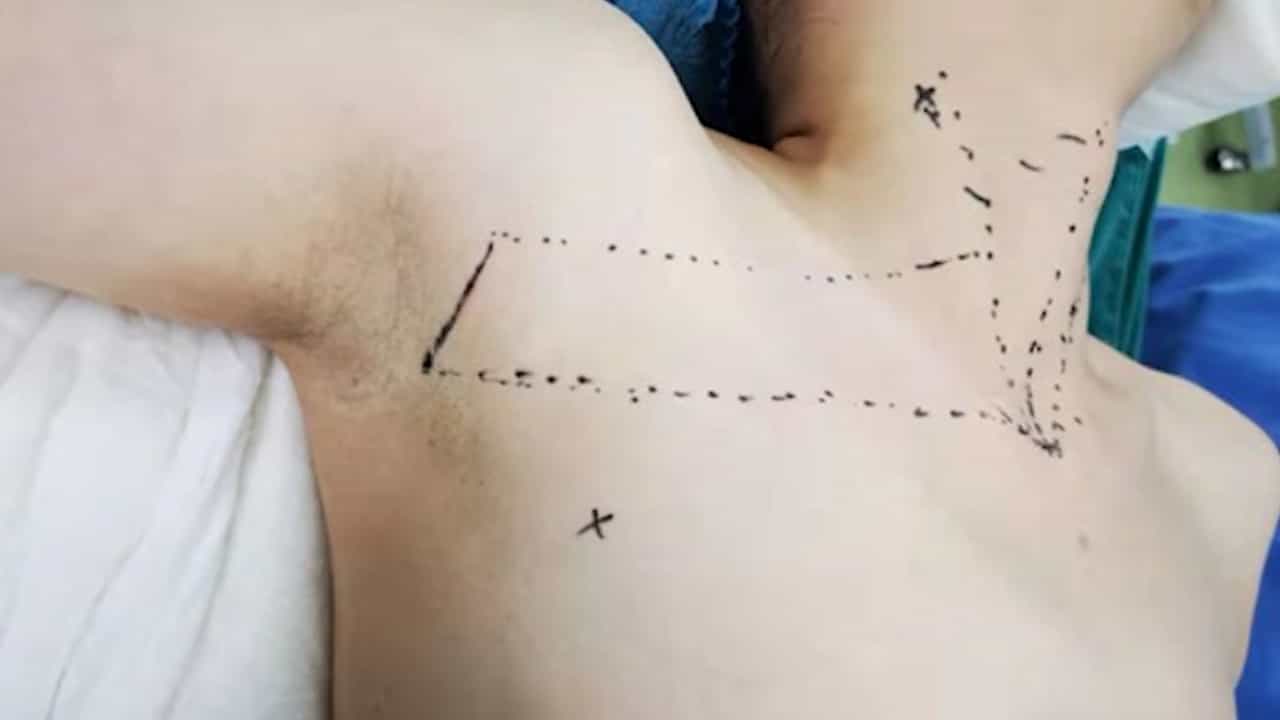
"Sun's Seven-Step Technique" for Endoscopic En-Bloc Resection of Thyroid Cancer via the Chest-Breast Approach
Published on: November 28, 2025
[Lymphectomy in differentiated thyroid carcinoma]
Giovanni Conzo1, Francesco Stanzione, Antonietta Palazzo
1IV Divisione di Chirurgia Generale e di Endocrinochirurgia, Seconda Università degli Studi di Napoli, Napoli.

Abstract:
Papillary and follicular thyroid carcinoma are still characterised by unclear biological and clinical behaviour with an autoptic incidence higher than the clinical incidence. Lymph-node involvement represents a prognostic factor that may increase the rate of local relapse, reducing long-term survival only in high risk patients--age > 45 years, M+, T > 3 cm, extra thyroidal extension, follicular histotype. The authors analyse the role of lymph-node cervical dissection. Routine or selective, extended or conservative lymphectomy are described in the literature. Prognostic factors are useful to determine the most appropriate surgical procedure. An elective cervical central dissection may be indicated in patients at high risk, while in cases of monolateral lymph-node metastases, in patients at low risk, a selective lymph node dissection of levels VI-III-IV is associated with lower morbidity. Modified radical neck dissection is reserved for patients at high risk or in cases of multiple lymph-node metastases (> 5) to reduce the incidence of local relapse. In the treatment of differentiated thyroid carcinoma an elective total thyroidectomy must be performed in combination with adjuvant radioiodine ablation.