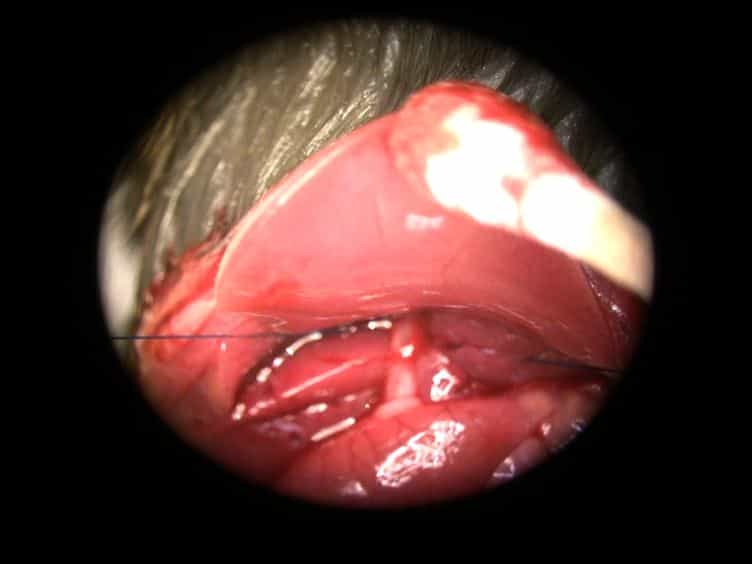
Related Experiment Video
Updated: Jun 13, 2026

Method of Direct Segmental Intra-hepatic Delivery Using a Rat Liver Hilar Clamp Model
Published on: April 2, 2017
Ischemic preconditioning-induced hyperperfusion correlates with hepatoprotection after liver resection
Oleg Heizmann1, Georgios Meimarakis, Andreas Volk
1Department of Surgery, University Hospital Basel, CH-4031 Basel, Switzerland. oheizmann@uhbs.ch

Aim:
To characterize the impact of the Pringle maneuver (PM) and ischemic preconditioning (IP) on total blood supply to the liver following hepatectomies.
Methods:
Sixty one consecutive patients who underwent hepatic resection under inflow occlusion were randomized either to receive PM alone (n = 31) or IP (10 min of ischemia followed by 10 min of reperfusion) prior to PM (n = 30). Quantification of liver perfusion was measured by Doppler probes at the hepatic artery and portal vein at various time points after reperfusion of remnant livers.
Results:
Occlusion times of 33 +/- 12 min (mean +/- SD) and 34 +/- 14 min and the extent of resected liver tissue (2.7 segments) were similar in both groups. In controls (PM), on reperfusion of liver remnants for 15 min, portal perfusion markedly decreased by 29% while there was a slight increase of 8% in the arterial blood flow. In contrast, following IP + PM the portal vein flow remained unchanged during reperfusion and a significantly increased arterial blood flow (+56% vs baseline) was observed. In accordance with a better postischemic blood supply of the liver, hepatocellular injury, as measured by alanine aminotransferase (ALT) levels on day 1 was considerably lower in group B compared to group A (247 +/- 210 U/I vs 550 +/- 650 U/I, P < 0.05). Additionally, ALT levels were significantly correlated to the hepatic artery inflow.
Conclusion:
IP prevents postischemic flow reduction of the portal vein and simultaneously increases arterial perfusion, suggesting that improved hepatic macrocirculation is a protective mechanism following hepatectomy.