Related Experiment Video
Updated: Jun 13, 2026
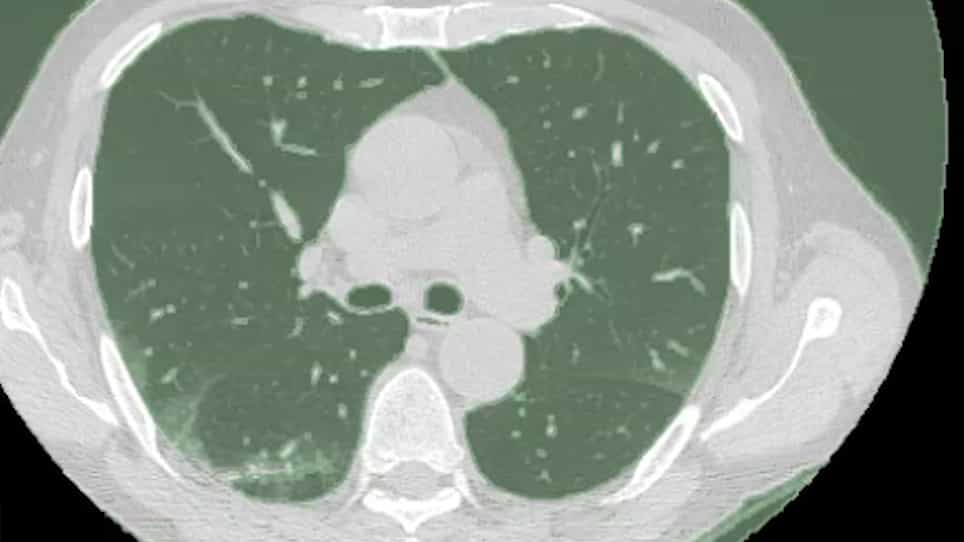

Lung CT Segmentation to Identify Consolidations and Ground Glass Areas for Quantitative Assesment of SARS-CoV Pneumonia
Published on: December 19, 2020
Non-severe pulmonary embolism: prognostic CT findings
Anne-Line Moroni1, Jean-Luc Bosson, Noélie Hohn
1University J Fourrier, Grenoble, France.

Insights
In patients with non-severe pulmonary embolism (PE), a right/left ventricle diameter ratio greater than 1 predicts mortality, especially with low embolic burden. Other CT parameters were not associated with death.
Area of Science:
- Cardiology
- Radiology
- Pulmonology
Background:
- Pulmonary embolism (PE) poses a significant mortality risk, even in clinically non-severe cases.
- Predictive markers for mortality in non-severe PE are crucial for risk stratification.
- Computed tomography (CT) offers detailed cardiovascular and embolic burden assessment.
Purpose of the Study:
- To retrospectively evaluate CT-derived cardiovascular parameters and pulmonary artery clot load score.
- To determine their predictive value for 3-month mortality in patients with non-severe PE.
- To identify key predictors of mortality in this patient cohort.
Main Methods:
- Retrospective analysis of 226 CT scans in hemodynamically stable patients with PE.
- Independent review of CT scans by two observers assessing interventricular septum shape and right/left ventricle (RV/LV) diameter ratio.
- Cox regression analysis to compare CT parameters with 3-month mortality.
- Multivariate analysis incorporating lower limb deep vein thrombosis (DVT) and comorbidities.
Main Results:
- A RV/LV diameter ratio >1 was predictive of death (OR, 3.83; p < 0.01) specifically when embolic burden was < 40%.
- Interobserver agreement was moderate for interventricular septum shape (κ = 0.41) and substantial for RV/LV ratio (κ = 0.76).
- CT cardiovascular parameters, as a group, were not associated with death in the multivariate model. Lower limb DVT and comorbidities were significant predictors.
Conclusions:
- In non-severe PE, an elevated RV/LV diameter ratio is a significant predictor of mortality, particularly in cases with low embolic burden.
- CT-derived cardiovascular parameters alone are insufficient for predicting mortality in non-severe PE.
- Concomitant lower limb DVT and comorbid conditions are critical factors influencing mortality in patients with non-severe PE.
Abstract:
The goal of this study was to retrospectively evaluate CT cardiovascular parameters and pulmonary artery clot load score as predictors of 3-month mortality in patients with clinically non-severe pulmonary embolism (PE). We included 226 CT positive for PE in hemodynamically stable patients (112 women; mean age 67.1 years ± 16.9). CT were independently reviewed by two observers. Results were compared with occurrence of death within 3 months using Cox regression. Twenty-four (10.6%) patients died, for whom 9 were considered to be due to PE. Interobserver agreement was moderate for the shape of interventricular septum (κ = 0.41), and for the ratio between the diameters of right and left ventricle (RV/LV) (κ = 0.76). Observers found no association between interventricular septum shape and death. A RV/LV diameter ratio >1 was predictive of death (OR, 3.83; p < 0.01) only when we also took into account the value of the embolic burden (< 40%). In a multivariate model, CT cardiovascular parameters were not associated with death. Concomitant lower limb DVT and comorbid conditions were important predictors of death. In clinically non-severe PE, a RV/LV diameter ratio >1 is predictive of death when the embolic burden is low (< 40%).

Related Concept Videos
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:29
Pulmonary Embolism I: Introduction
 01:19
Pulmonary Embolism I: Introduction
 01:27
Pulmonary Embolism III: Nursing Management
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies
 01:13
Radiological Investigation III: Pulmonary Angiogram and PET Scan
Pulmonary Angiogram
A Pulmonary Angiogram is an invasive procedure involving injecting a contrast medium through a catheter threaded into the pulmonary artery or the right side of the heart to visualize the pulmonary vasculature. Computed Tomography (CT) scans have mainly replaced this...