Superficial venous thrombophlebitis caused by rocuronium

Can Eyigor1, Arda Ceylan, Fusun Demir

  • 1Anesthesiology Department, Faculty of Medicine, Pain Clinic, Ege University, 35100, Bornova, Izmir, Turkey. can.eyigor@yahoo.com.tr

Journal of Anesthesia
|April 23, 2010
PubMed

Related Concept Videos

Venous Thrombosis I: Introduction01:30

Venous Thrombosis I: Introduction

Venous thrombosis, the most common disorder of the veins, involves the formation of a thrombus or blood clot associated with vein inflammation. It can be classified as either superficial vein thrombosis or deep vein thrombosis.Superficial Vein Thrombosis: This involves the formation of a thrombus in a superficial vein, usually the greater or lesser saphenous vein. Though less severe than deep vein thrombosis (DVT), SVT can lead to complications if untreated.Deep Vein Thrombosis (DVT): This...
Venous Thrombosis III: Interprofessional Care01:29

Venous Thrombosis III: Interprofessional Care

Venous thrombosis requires effective prevention and treatment strategies to improve patient outcomes and reduce potential complications.Prevention StrategiesHealthcare providers must prioritize preventing venous thromboembolism (VTE) for all adult patients upon admission. Interventions depend on bleeding and thrombosis risk, medical history, current medications, diagnoses, planned procedures, and patient preferences. Patients on bed rest should change positions every two hours and, if not...
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies01:20

Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies

The key difference between Superficial Vein Thrombosis (SVT) and Deep Vein Thrombosis (DVT) lies in their location and severity.Clinical ManifestationsSVT typically presents with localized pain, tenderness, and redness along the course of a superficial vein, often accompanied by a palpable, cord-like structure under the skin. This condition is usually less dangerous than DVT but can be uncomfortable and may lead to complications such as cellulitis or, rarely, a clot extension into the deep...
Skeletal Muscle Relaxants: Therapeutic Uses01:31

Skeletal Muscle Relaxants: Therapeutic Uses
Skeletal muscle relaxants are used to relax muscle tone and alleviate painful muscle contractions. However, the choice of skeletal muscle relaxants depends on the duration of the surgical procedure in order to minimize potential side effects. Skeletal muscle relaxants like neuromuscular blocking agents [NMBAs] are commonly employed as adjuvants alongside general anesthetics in clinical settings. NMBAs are also used to maintain controlled ventilation during surgery of the larynx or pharynx as...
Nondepolarizing (Competitive) Neuromuscular Blockers: Mechanism of Action01:17

Nondepolarizing (Competitive) Neuromuscular Blockers: Mechanism of Action

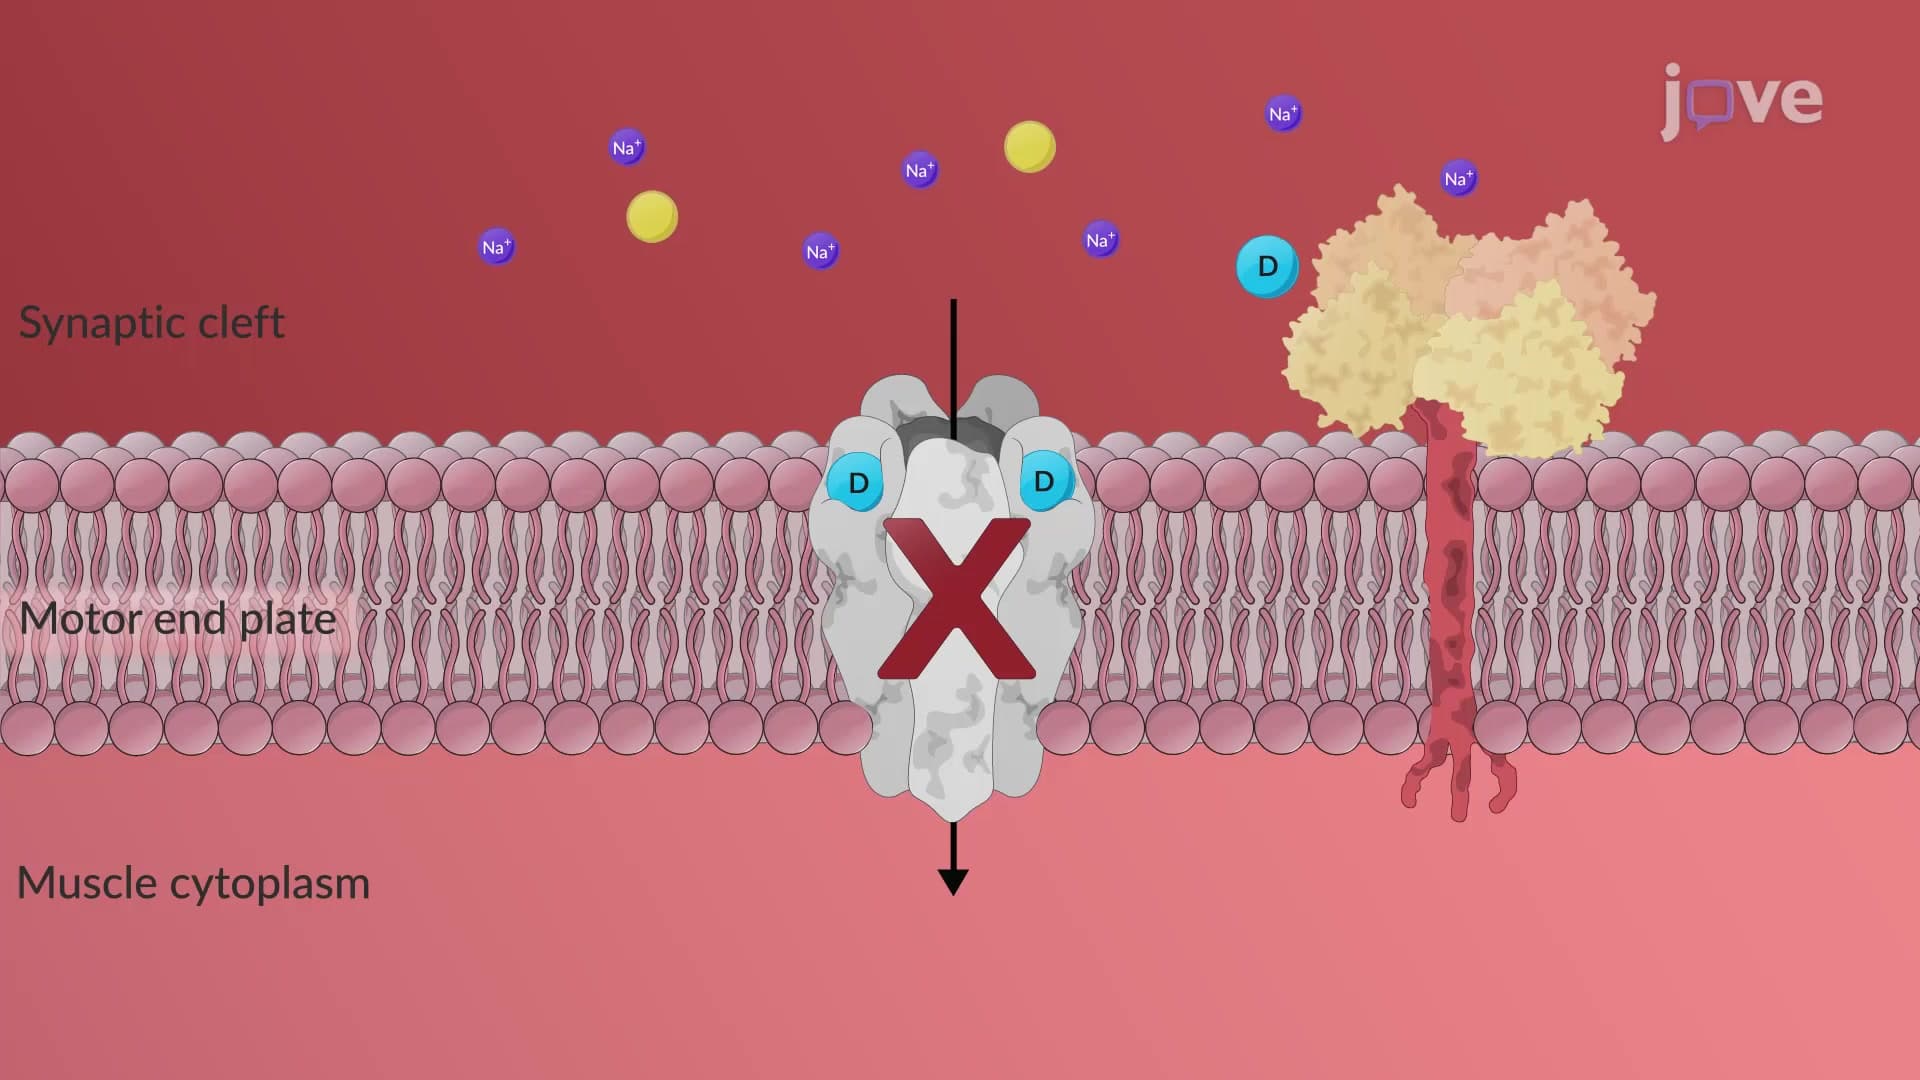
Nondepolarizing neuromuscular blockers induce paralysis by competitively blocking nicotinic acetylcholine receptors at the muscle end plate. Examples include pancuronium, mivacurium, vecuronium, and rocuronium. These quaternary ammonium derivatives are administered intravenously, are poorly absorbed, and are excreted via the kidneys.
Competitive antagonists prevent acetylcholine from binding to its receptor, inhibiting membrane depolarization. Without conformational changes or intrinsic...
Local Anesthetics: Clinical Application as Intravenous Regional Anesthesia01:16

Local Anesthetics: Clinical Application as Intravenous Regional Anesthesia

Intravenous regional anesthesia or the Bier block technique is used to anesthetize a specific limb or extremity. It uses exsanguinated or blood-drained vessels to transport local anesthetics or LAs to the peripheral nerve trunks. Lidocaine without vasoconstrictors like epinephrine is most commonly used for this technique. Other drugs used are prilocaine, ropivacaine, and chloroprocaine. Bupivacaine is not recommended for this technique due to its high cardiac toxicity.
One of the advantages of...