Related Experiment Video
Updated: Jun 12, 2026


Improved Renal Denervation Mitigated Hypertension Induced by Angiotensin II Infusion
Published on: May 26, 2022
Is the reno-protective effect of valsartan dose dependent? A comparative study of 80 and 160 mg day(-1)
Tetsunori Saikawa1, Jun Sasaki, Sadayoshi Biro
1Department of Clinical Examination and Diagnostics, Oita University, Oita, Japan. saikawa@med.oita-u.ac.jp

Abstract:
Whether the reno-protective effect of angiotensin receptor blockers is dose dependent is unknown for the Japanese population. We sought to elucidate the dose-dependent reno-protective effects of valsartan in Japanese hypertensive patients with albuminuria. This was a multi-center, open-label, parallel-group trial. A total of 181 patients were randomized to receive either 80 (n=89) or 160 mg day(-1) (n=92) of valsartan for 24 weeks. Then, the effects on blood pressure, urinary albumin excretion (UAE), type IV collagen and beta(2)-microglobulin (beta2MG) were determined. Systolic and diastolic blood pressures decreased substantially by almost the same extent in the low-dose and high-dose groups, showing no inter-group difference during the treatment. The UAE value decreased significantly by 35% in both groups. Urinary excretion of beta2MG was significantly decreased in the high-dose group (17%), but not in the low-dose group (13%), although the decrease was not significantly different between the two groups (P=0.74). Urinary excretion of type IV collagen decreased non-significantly by 10% in the low-dose group and by 8% in the high-dose group, showing no significant inter-group difference (P=0.78). Low (80 mg day(-1)) and high (160 mg day(-1)) doses of valsartan showed a similar effect of lowering blood pressure. The high dose of valsartan resulted in a slightly greater decrease in urinary beta2MG, but it was inconclusive whether the high dose was more reno-protective as compared with the low dose.
Related Concept Videos
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 01:25
Antihypertensive Drugs: Direct Renin Inhibitors
 01:30
Antihypertensive Drugs: Angiotensin II Receptor Blockers
 01:26
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System
 01:25
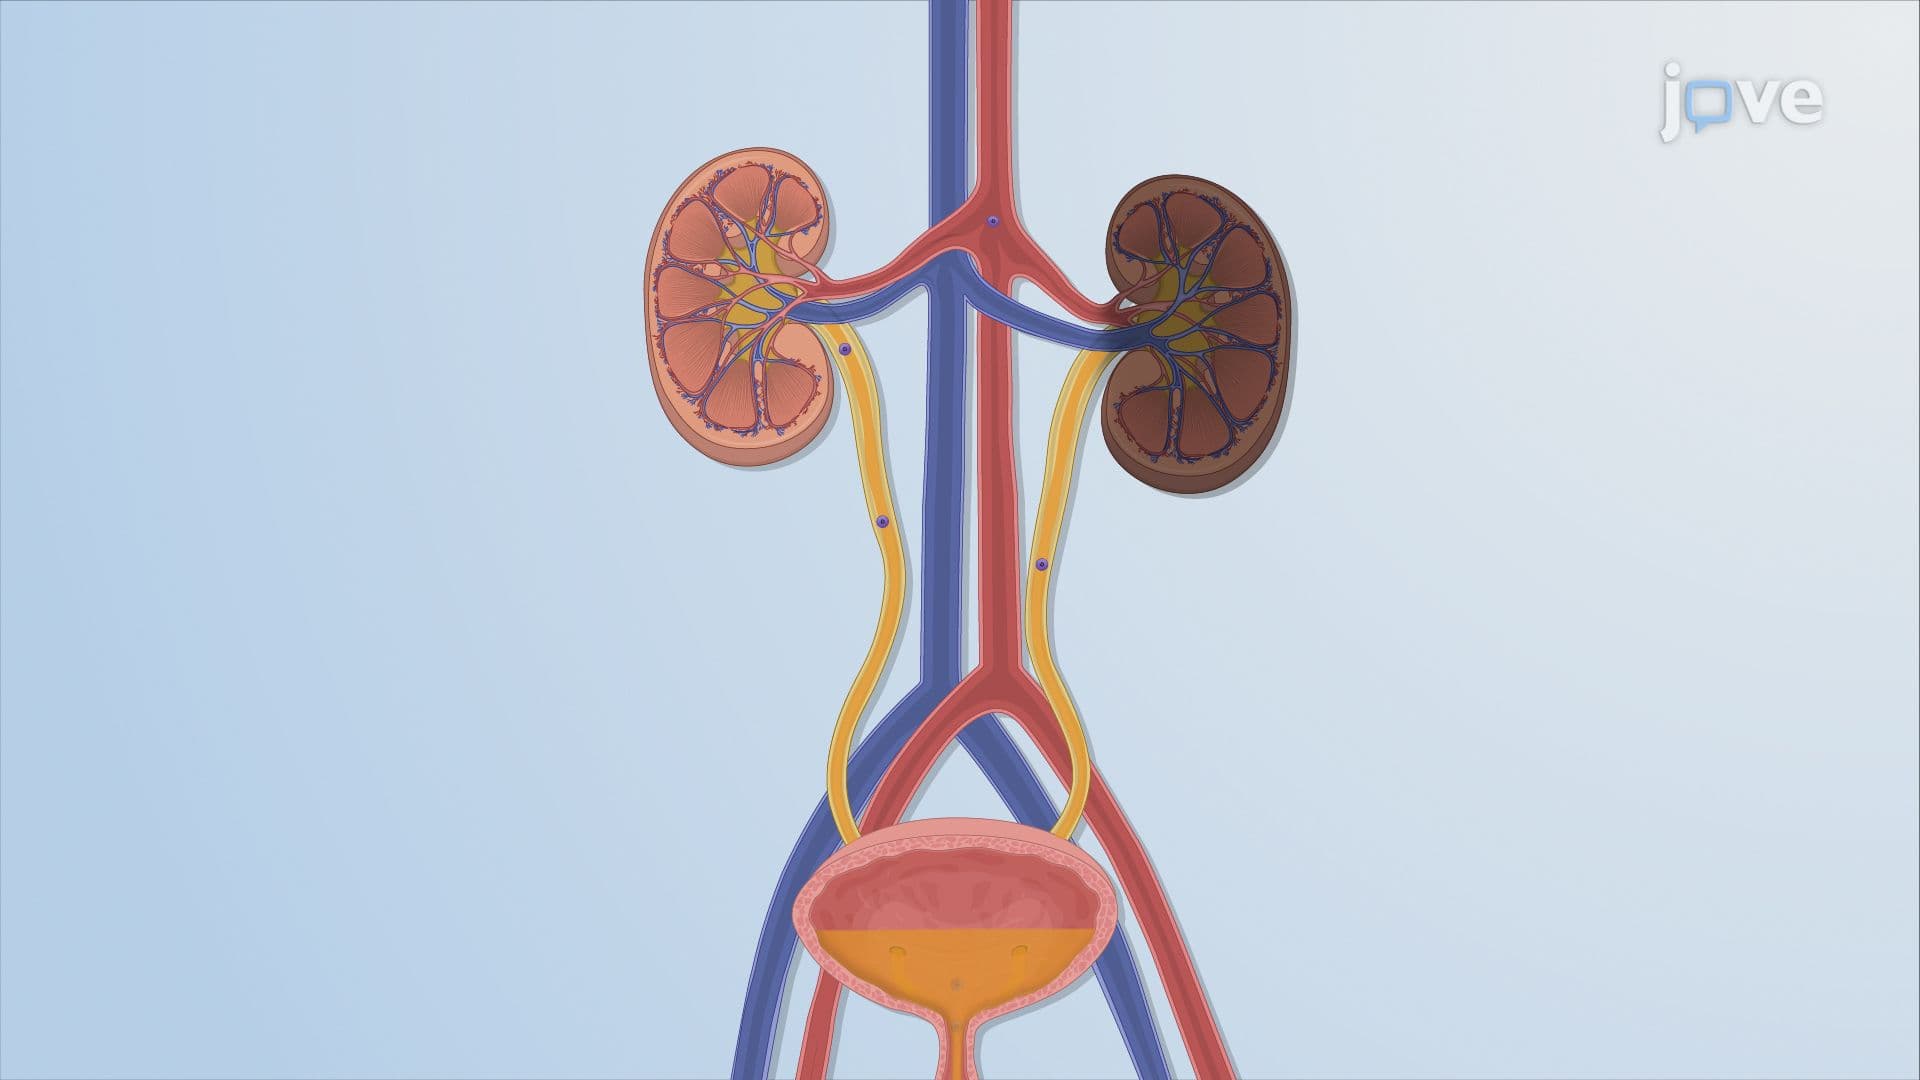
Drug Dosing in Renal Diseases: Measurement of Glomerular Filtration Rate