Related Experiment Video
Updated: Jun 10, 2026
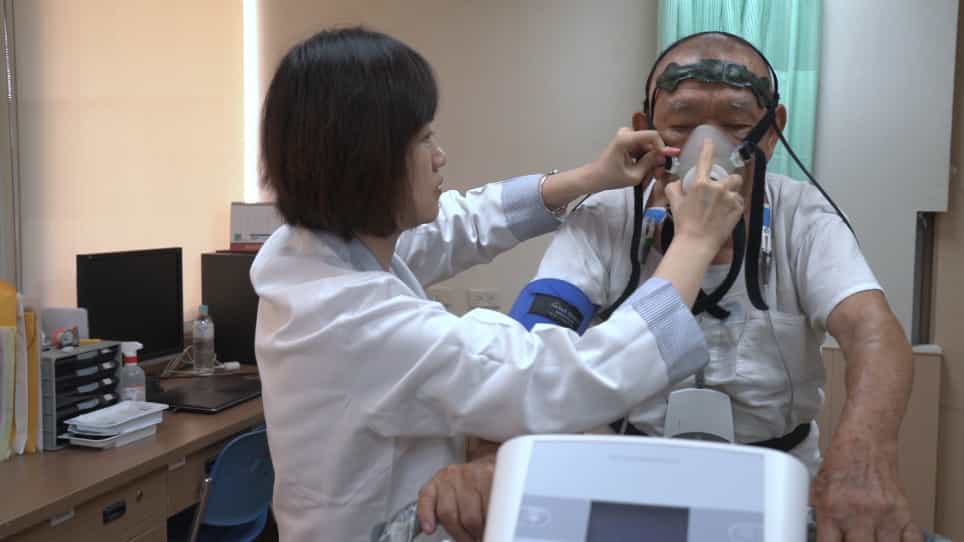

Integration of Brain Tissue Saturation Monitoring in Cardiopulmonary Exercise Testing in Patients with Heart Failure
Published on: October 1, 2019
Cardiopulmonary Exercise Testing in Patients with Chronic Heart Failure: Prognostic Comparison from Peak VO2 and
Filippo Maria Sarullo1, Giovanni Fazio, Ignazio Brusca
1Division of Cardiology, Buccheri La Ferla Fatebenefratelli Hospital Palermo, Italy.

Background:
Cardiopulmonary exercise testing with ventilatory expired gas analysis (CPET) has proven to be a valuable tool for assessing patients with chronic heart failure (CHF). The maximal oxygen uptake (peak V02) is used in risk stratification of patients with CHF. The minute ventilation-carbon dioxide production relationship (VE/VCO2 slope) has recently demonstrated prognostic significance in patients with CHF.
Methods:
Between January 2006 and December 2007 we performed CPET in 184 pts (146 M, 38 F, mean age 59.8 +/- 12.9 years), with stable CHF (96 coronary artery disease, 88 dilated cardiomyopathy), in NYHA functional class II (n.107) - III (n.77), with left ventricular ejection fraction (LVEF)
Results:
Peak VO2 and VE/VCO2 slope were demonstrated with univariate Cox regression analysis both to be significant predictor of cardiac-related mortality and hospitalization (p < 0.0001, respectively). Non survivors had a lower peak VO2 (10.49 +/- 1.70 ml/kg/min vs. 14.41 +/- 3.02 ml/kg/min, p < 0.0001), and steeper Ve/VCO2 slope (41.80 +/- 8.07 vs. 29.84 +/- 6.47, p < 0.0001) than survivors. Multivariate survival analysis revealed that VE/VCO2 slope added additional value to VO2 peak as an independent prognostic factor (chi2: 56.48, relative risk: 1.08, 95% CI: 1.03 - 1.13, p = 0.001). The results from Kaplan-Meier analysis revealed a 1-year cardiac-related mortality of 75% in patients with VE/VCO2 slope >/= 35.6 and 25% in those with VE/VCO2 slope < 35.6 (log rank chi2: 67.03, p < 0.0001) and 66% in patients with peak VO2 12.2 ml/kg/min (log rank chi2: 50.98, p < 0.0001). One-year cardiac-related hospitalization was 77% in patients with VE/VCO2 slope >/= 32.5 and 23% in those with VE/VCO2 slope < 32.5 (log rank chi2: 133.80, p < 0.0001) and 63% in patients with peak VO2 12.3 ml/kg/min (log rank chi2: 72.86, p < 0.0001). The VE/VCO2 slope was demonstrated with receiver operating characteristic curve analysis to be equivalent to peak VO2 in predicting cardiac-related mortality (0.89 vs. 0.89). Although area under the receiver operating characteristic curve for the VE/VCO2 slope was greater than peak VO2 in predicting cardiac-related hospitalization (0.88 vs 0.82), the difference was no statistically significant (p = 0.13).
Conclusion:
These results add to the present body of knowledge supporting the use of CPET in CHF patients. The VE/VCO2 slope, as an index of ventilatory response to exercise, is an excellent prognostic parameter and improves the risk stratification of CHF patients. It is easier to obtain than parameters of maximal exercise capacity and is of equivalent prognostic importance than peak VO2.
More Related Videos
Related Concept Videos
 01:17
Exercise and Cardiac Output
Sustained exercise increases the muscles' oxygen demand, which can be met...
 01:25
Pulmonary Function Tests
Pulmonary Function Tests are crucial diagnostic tools for assessing respiratory function, particularly in patients with chronic respiratory disorders. They comprehensively evaluate lung volumes, ventilatory function, breathing mechanics, diffusion, and gas exchange. These tests help diagnose pulmonary diseases and play a significant role in monitoring disease progression, evaluating disability, and assessing response to therapy.
PFTs involve using a spirometer, a...
 01:17
Assessment of Diffusion and Perfusion
The Role of Diffusion in Respiration
Diffusion is the process by which molecules move from an area of higher concentration to an area of lower concentration. In the respiratory system, this principle...
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:19
Cardiac Output I:Effect of Heart Rate on Cardiac Output
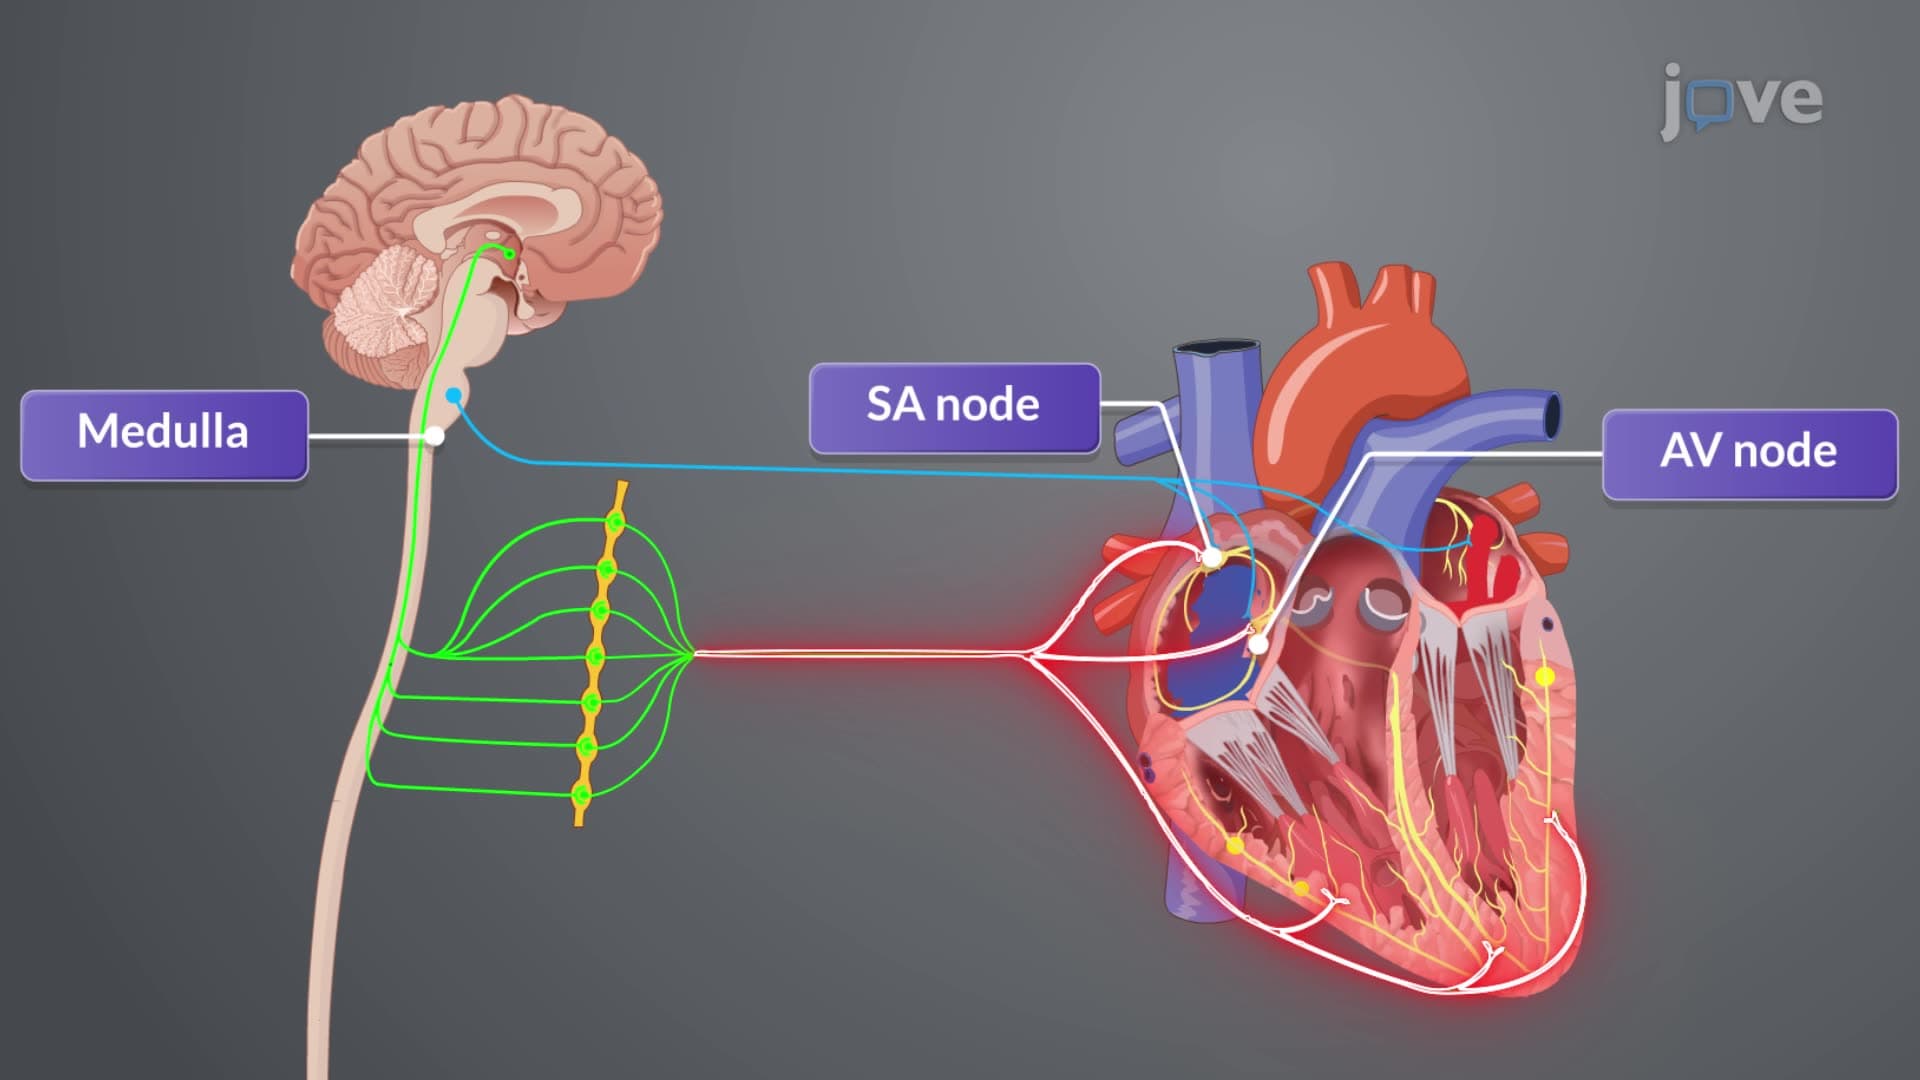
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart rate...
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...