Related Experiment Video
Updated: Jun 10, 2026
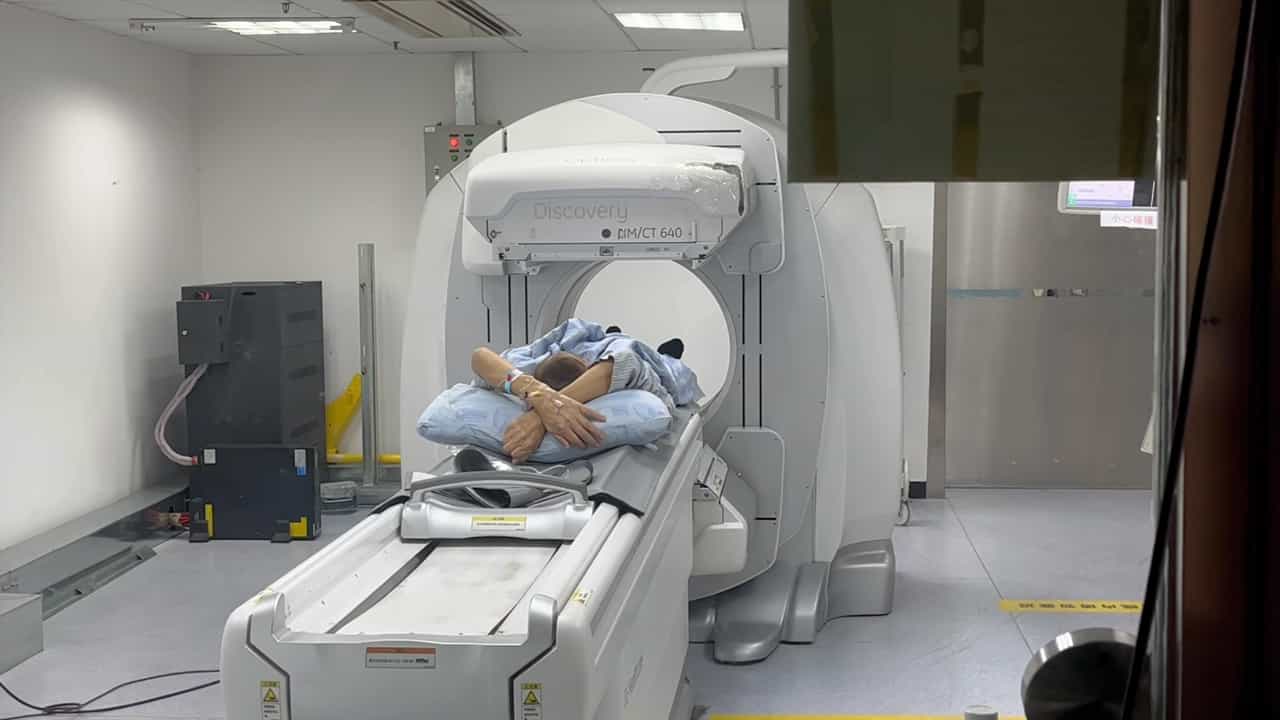

Y-90 Radioembolization and PD-1 Inhibitor as Neoadjuvant Treatment in Hepatocellular Carcinoma
Published on: May 24, 2024
Development of new hepaticoenteric collateral pathways after hepatic arterial skeletonization in preparation for
Mohamed H K Abdelmaksoud1, Gloria L Hwang, John D Louie
1Division of Interventional Radiology, H-3646 Stanford University Medical Center, 300 Pasteur Drive, Stanford, CA 94305-5642, USA.

Purpose:
Development of new hepaticoenteric anastomotic vessels may occur after endovascular skeletonization of the hepatic artery. Left untreated, they can serve as pathways for nontarget radioembolization. The authors reviewed the incidence, anatomy, management, and significance of collateral vessel formation in patients undergoing radioembolization.
Materials And Methods:
One hundred thirty-eight treatments performed on 122 patients were reviewed. Each patient underwent a preparatory digital subtraction angiogram (DSA) and embolization of all hepaticoenteric vessels in preparation for yttrium-90 ((90)Y) administration. Successful skeletonization was verified by C-arm computed tomography (CACT) and technetium-99m macroaggregated albumin ((99m)TcMAA) scintigraphy. During the subsequent treatment session, DSA and CACT were repeated before administration of (90)Y, and the detection of extrahepatic perfusion prompted additional embolization.
Results:
Forty-two patients (34.4%) undergoing 43 treatments (31.2%) required adjunctive embolization of hepaticoenteric vessels immediately before (90)Y administration. Previous scintigraphy findings showed extrahepatic perfusion in only three cases (7.1%). Vessels were identified by DSA in 54.1%, by CACT in 4.9%, or required both in 41.0%. The time interval between angiograms did not correlate with risk of requiring reembolization (P = .297). A total of 19.7% of vessels were new collateral vessels not visible during the initial angiography. Despite reembolization, three patients (7.1%) had gastric or duodenal ulceration, compared with 1.3% who never had visible collateral vessels, all of whom underwent whole-liver treatment with resin microspheres (P = .038).
Conclusions:
Development of collateral hepaticoenteric anastomoses occurs after endovascular skeletonization of the hepatic artery. Identified vessels may be managed by adjunctive embolization, but patients appear to remain at increased risk for gastrointestinal complications.
More Related Videos
 09:49
Dual-phase Cone-beam Computed Tomography to See, Reach, and Treat Hepatocellular Carcinoma during Drug-eluting Beads Transarterial Chemo-embolization
Published on: December 2, 2013
 14:52
Re-Arterialized Rat Partial Liver Transplantation with an in vivo Vessel-Oriented 70% Hepatectomy
Published on: April 8, 2018