Related Experiment Video
Updated: Jun 10, 2026
A Murine Model of Hemodialysis Access-Related Hand Dysfunction
Published on: May 31, 2022
Brachial artery aneurysms associated with arteriovenous access for hemodialysis
Eric Chemla1, Mei Nortley, Mohamed Morsy
1Renal Transplant Unit, St. George's Hospital, London, United Kingdom. eric.chemla@stgeorges.nhs.uk

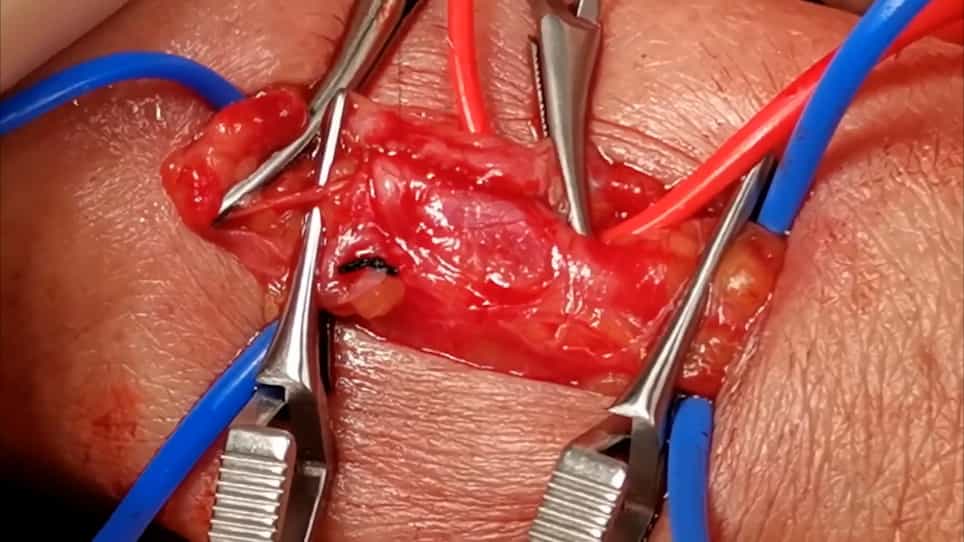
Brachial artery aneurysm (BAA) is a rare condition. We describe a series of cases of BAA with arteriovenous access. Thirteen patients were retrospectively identified between January 2006 and July 2009 using a patient database. All were associated with brachio-cephalic fistulas. Mean age was 51.2 +/- 13.8 years. Twelve males (93.3%) were identified. Characteristics were: diabetes 1, hypertension 8, hypercholesterolemia 2, ischemic heart disease 2, family history of aneurysmal disease 2. Five BAA developed after access ligation, eight while it was working, one after trauma. One was associated with a venous aneurysm. While the average life of the access was 161 +/- 115 months, the average time for BAA formation was 40 +/- 35.8 months. BAA was asymptomatic in three patients, whereas 10 presented with ischemic and neurologic symptoms. None presented with a rupture. All patients underwent surgical repair, seven an aneurysm excision and end-to-end reconstruction of the brachial artery. Venous conduits were utilized: four long saphenous veins, one cephalic, and one basilic vein. All patients had patent brachial arteries with a complete relief of symptoms at 14 months. BAA is a rare but significant complication of vascular access. The surgical approaches presented offer a reasonable outcome.
Brachial artery aneurysm (BAA) is a rare condition. We describe a series of cases of BAA with arteriovenous access. Thirteen patients were retrospectively identified between January 2006 and July 2009 using a patient database. All were associated with brachio-cephalic fistulas. Mean age was 51.2 +/- 13.8 years. Twelve males (93.3%) were identified. Characteristics were: diabetes 1, hypertension 8, hypercholesterolemia 2, ischemic heart disease 2, family history of aneurysmal disease 2. Five BAA developed after access ligation, eight while it was working, one after trauma. One was associated with a venous aneurysm. While the average life of the access was 161 +/- 115 months, the average time for BAA formation was 40 +/- 35.8 months. BAA was asymptomatic in three patients, whereas 10 presented with ischemic and neurologic symptoms. None presented with a rupture. All patients underwent surgical repair, seven an aneurysm excision and end-to-end reconstruction of the brachial artery. Venous conduits were utilized: four long saphenous veins, one cephalic, and one basilic vein. All patients had patent brachial arteries with a complete relief of symptoms at 14 months. BAA is a rare but significant complication of vascular access. The surgical approaches presented offer a reasonable outcome.

Related Concept Videos
 01:25
Hemodialysis I: Introduction
 01:24
Hemodialysis II: Procedure and Complications
 01:12
Arteries of the Upper Limbs
 01:25
Hemodialysis III: Nursing Management
 01:26
Aneurysm III: Interprofessional Care
 01:21
Sites for measuring blood pressure
The Brachial Artery: Primary Site for Blood Pressure Measurement