Related Experiment Video
Updated: Jun 10, 2026

Drug-Induced Sleep Endoscopy (DISE) with Target Controlled Infusion (TCI) and Bispectral Analysis in Obstructive Sleep Apnea
Published on: December 6, 2016
Changes in lung volume and diaphragm muscle activity at sleep onset in obese obstructive sleep apnea patients vs.
Daniel L Stadler1, R Doug McEvoy, Jana Bradley
1Adelaide Institute for Sleep Health, Repatriation General Hospital, Daw Park, South Australia 5041, Australia. daniel.stadler@health.sa.gov.au

Abstract:
Obese obstructive sleep apnea (OSA) patients potentially defend end-expiratory lung volume (EELV) during wakefulness via increased expiratory diaphragmatic activity (eEMG(dia)). A reduction in eEMG(dia) and EELV at sleep onset could, therefore, increase upper airway collapsibility via reduced tracheal traction. The aim of this study was to establish if eEMG(dia) is greater in obese OSA patients vs. healthy-weight controls during wakefulness, and to compare eEMG(dia) and EELV changes at sleep onset between groups as a function of stable breathing, hypopnea vs. apnea events developing within the first few breaths after sleep onset. Eight obese men with OSA and eight healthy-weight men without OSA were studied in the supine position while instrumented with an intraesophageal catheter to measure eEMG(dia) and magnetometer coils to assess changes in EELV. While eEMG(dia) expressed as %maximal activity was not significantly different between groups during wakefulness, OSA patients experienced a greater fall in eEMG(dia) following sleep onset (group × breath, P < 0.001) and a greater decrease when respiratory events accompanied sleep onsets (category × breath, P < 0.001). The decrease in EELV by the third postsleep onset breath was small (OSA, 61.4 ± 8.0 ml, P < 0.001; controls, 34.0 ± 4.2 ml, P < 0.001), with the decrease significantly greater in OSA patients over time (group × breath, P = 0.007). There was a greater decrease with more severe events (category × breath, P < 0.001), with EELV decreasing by 89.6 ± 14.2 ml (P < 0.001) at the onset of apneas in the OSA group. These data support that diaphragm tone and EELV frequently decrease following sleep onset, with greater falls at transitions accompanied by respiratory events. In addition to decrements in upper airway dilator muscle activity, decreasing lung volume potentially contributes to an increased propensity for upper airway collapse in OSA patients at sleep onset.
More Related Videos
 04:53
Acupoint Application Combined with Ear Plaster Therapy for Treating Sleep Disorders with Acute Exacerbation of Chronic Obstructive Pulmonary Disease
Published on: October 18, 2024
 08:30
Intraperitoneal Glucose Tolerance Test, Measurement of Lung Function, and Fixation of the Lung to Study the Impact of Obesity and Impaired Metabolism on Pulmonary Outcomes
Published on: March 15, 2018
Related Concept Videos
 01:21
Sleep Apnea
The condition is more prevalent among...
 01:15
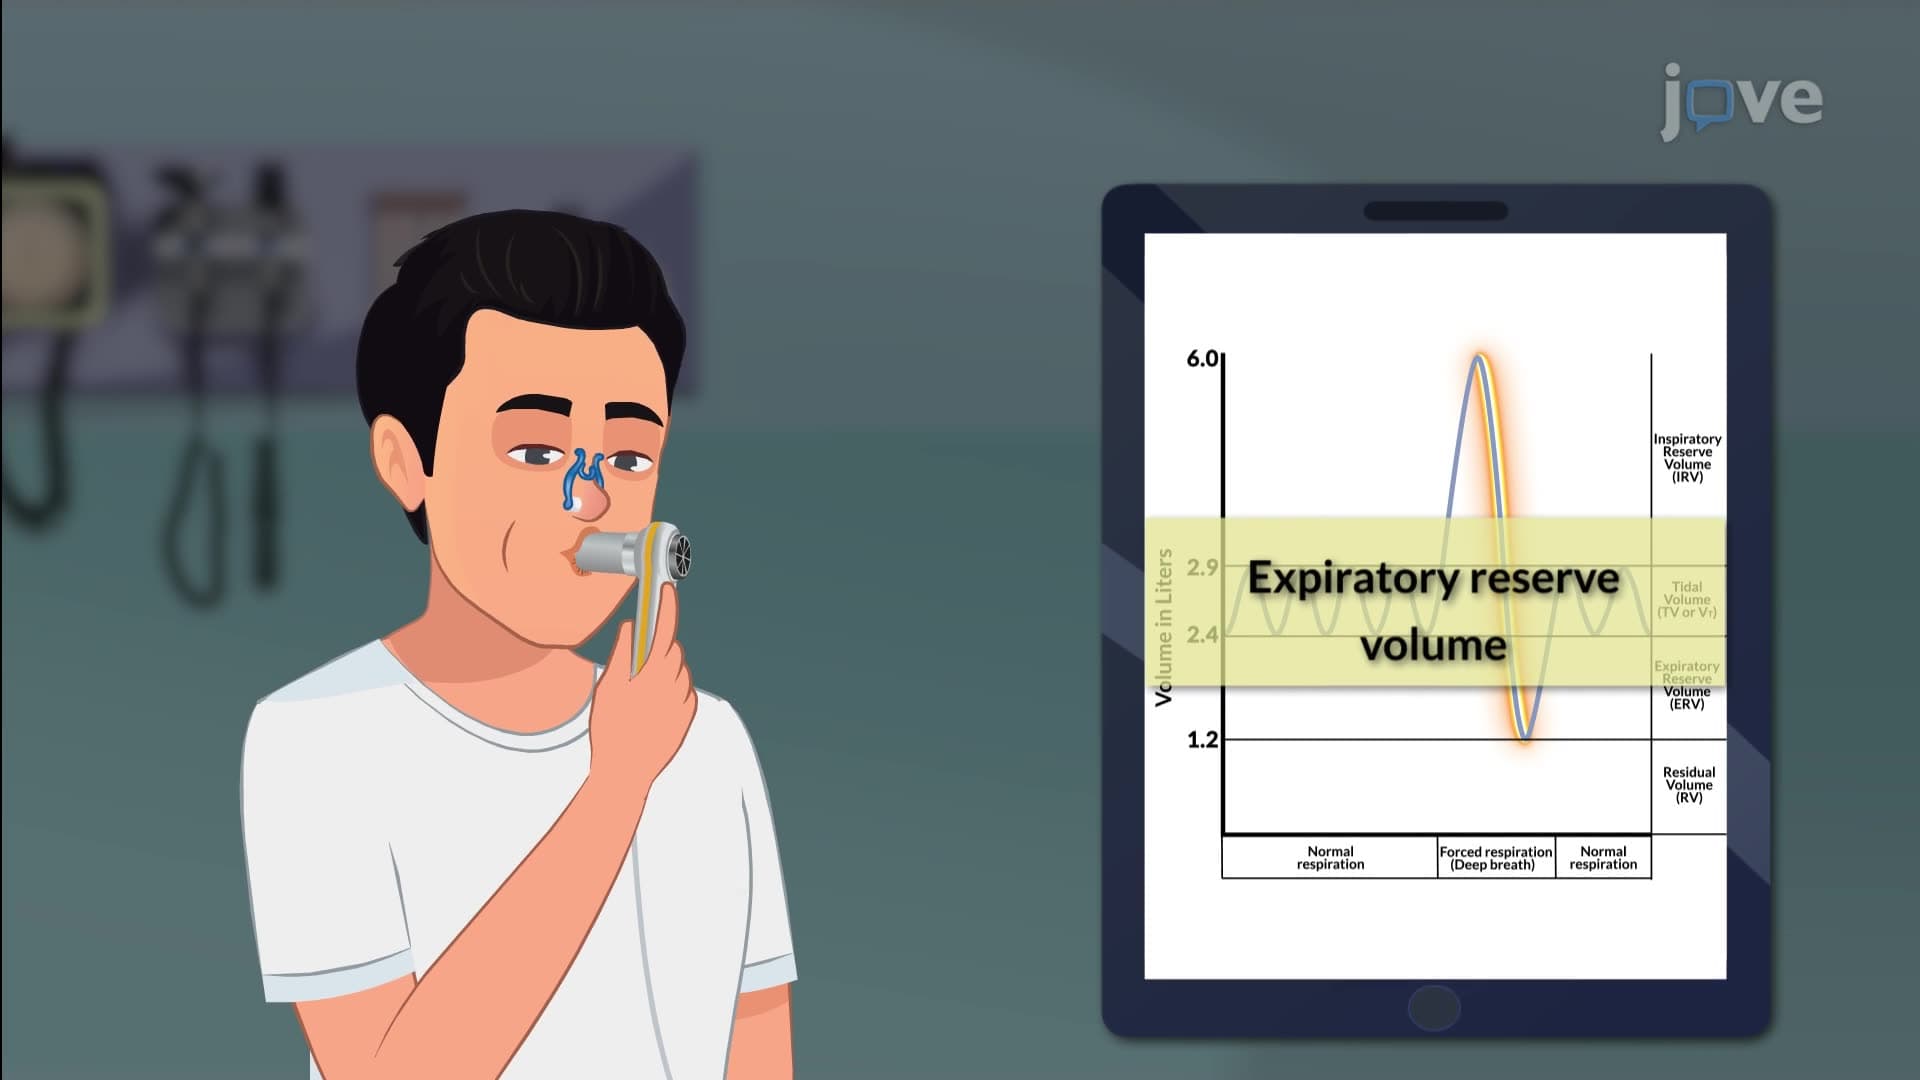
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:26
Respiratory Volumes and Capacities I
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:25
Hyperpnea and Hyperventilation
 01:30
Alterations in Respiration II
In Biot's breathing, the respiratory rate and depth are irregular, alternating between periods of deep gasping and apnea. Common causes include...