Related Experiment Video
Updated: Aug 19, 2026


Instrumentation of Near-term Fetal Sheep for Multivariate Chronic Non-anesthetized Recordings
Published on: October 25, 2015
Fetal and newborn lambs differ in their cardiopulmonary responsiveness to adenosine agonists
P L Toubas1, K C Sekar, R E Sheldon
1Department of Pediatrics, University of Oklahoma Health Sciences Center, Oklahoma City.

Abstract:
We investigated cardiorespiratory responses to adenosine analogs in the pre- and postnatal periods in an unanesthetized chronic animal preparation. Heart rate, blood pressure, breathing movements and blood gases were measured in 8 fetal lambs (117-130 days gestation) and 9 newborn lambs (4-30 days). Various doses of analogs were given by intravenous infusion. L-N6-5'-Phenylisopropyladenosine (L-PIA), 5-N-ethyl carboxamidoadenosine (NECA) and cyclohexyladenosine (CHA) were studied. All analogs produced dose-dependent bradycardia and hypotension in the fetus. However, in the newborn, NECA produced a dose-dependent tachycardia, whereas PIA and CHA produced a dose-dependent bradycardia. Fetal breathing movements were interrupted by all the analogs, but they did not produce apnea in the newborn. No changes in blood gases were observed. The actions of the adenosine agonists were blocked by caffeine.

Related Concept Videos
 01:21
Factors Affecting Drug Response: Overview
 01:26
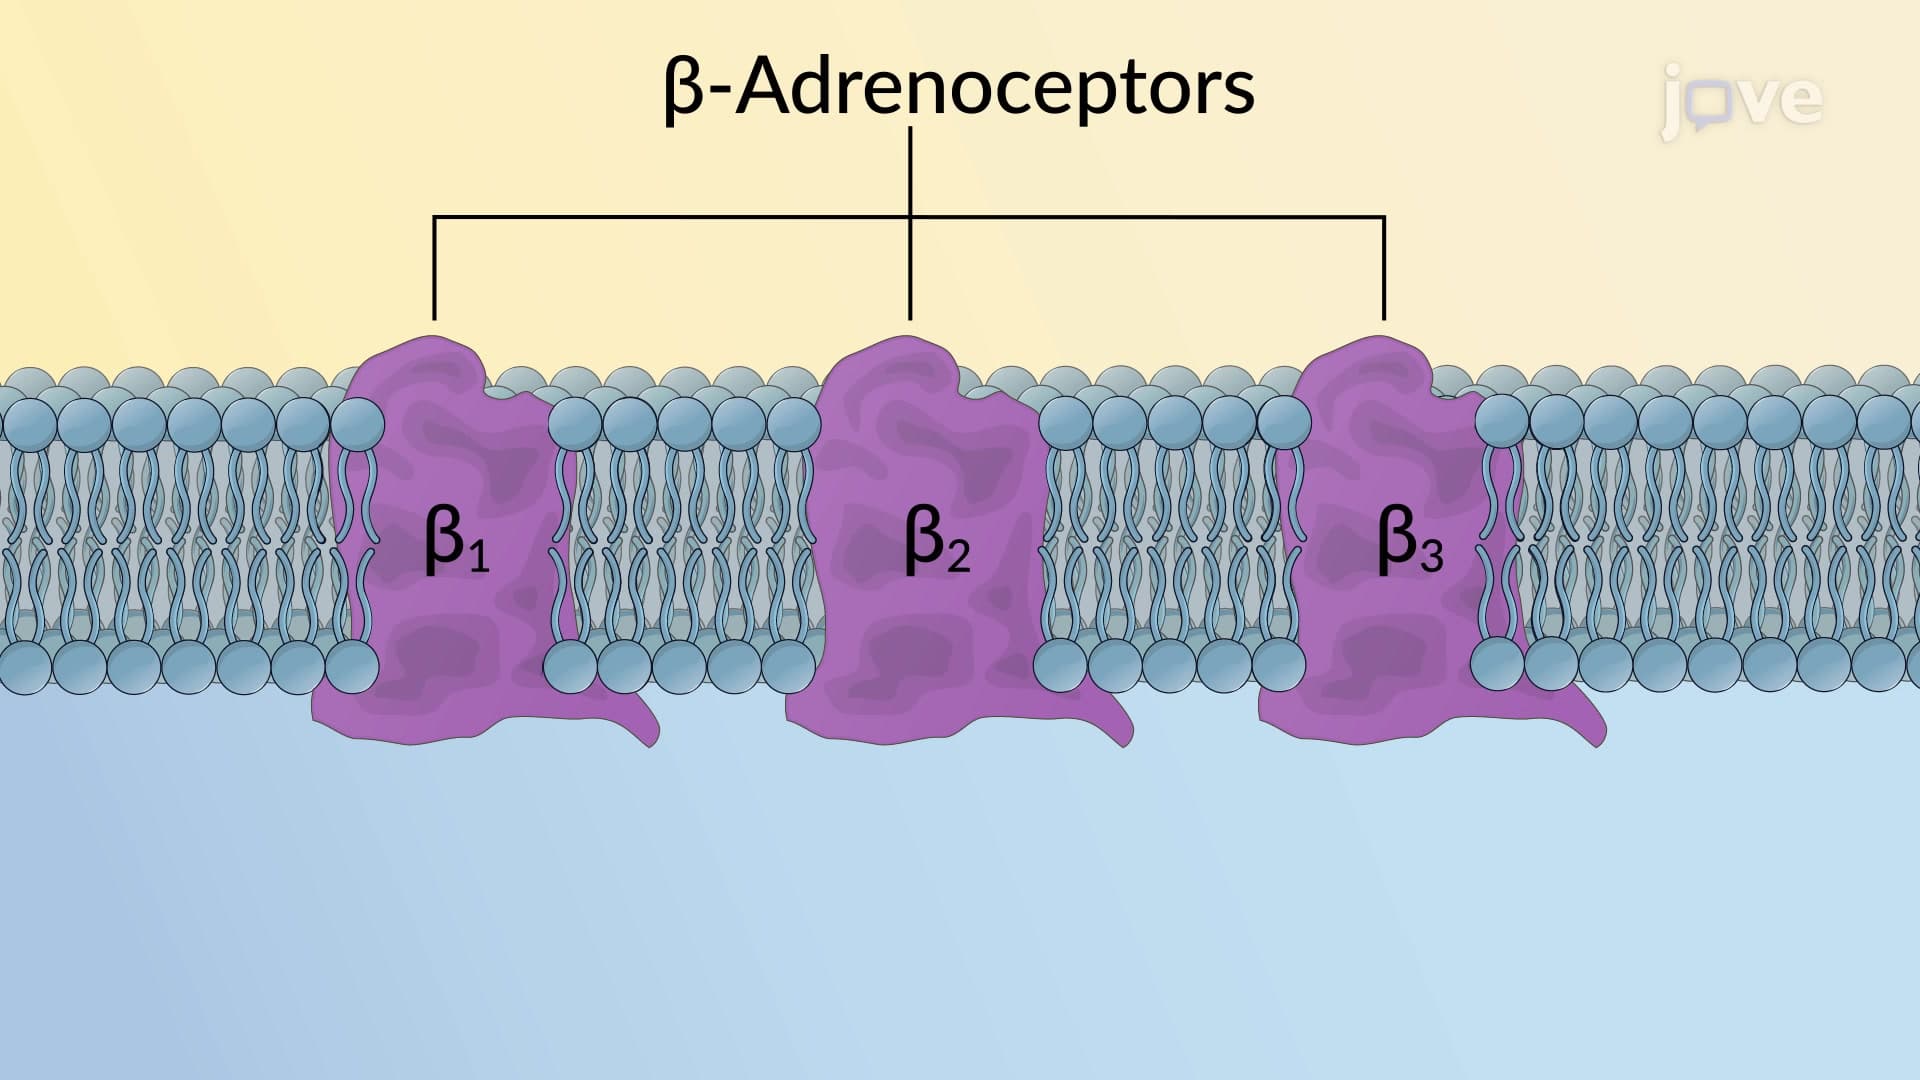
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors have equal affinities for...
 01:30
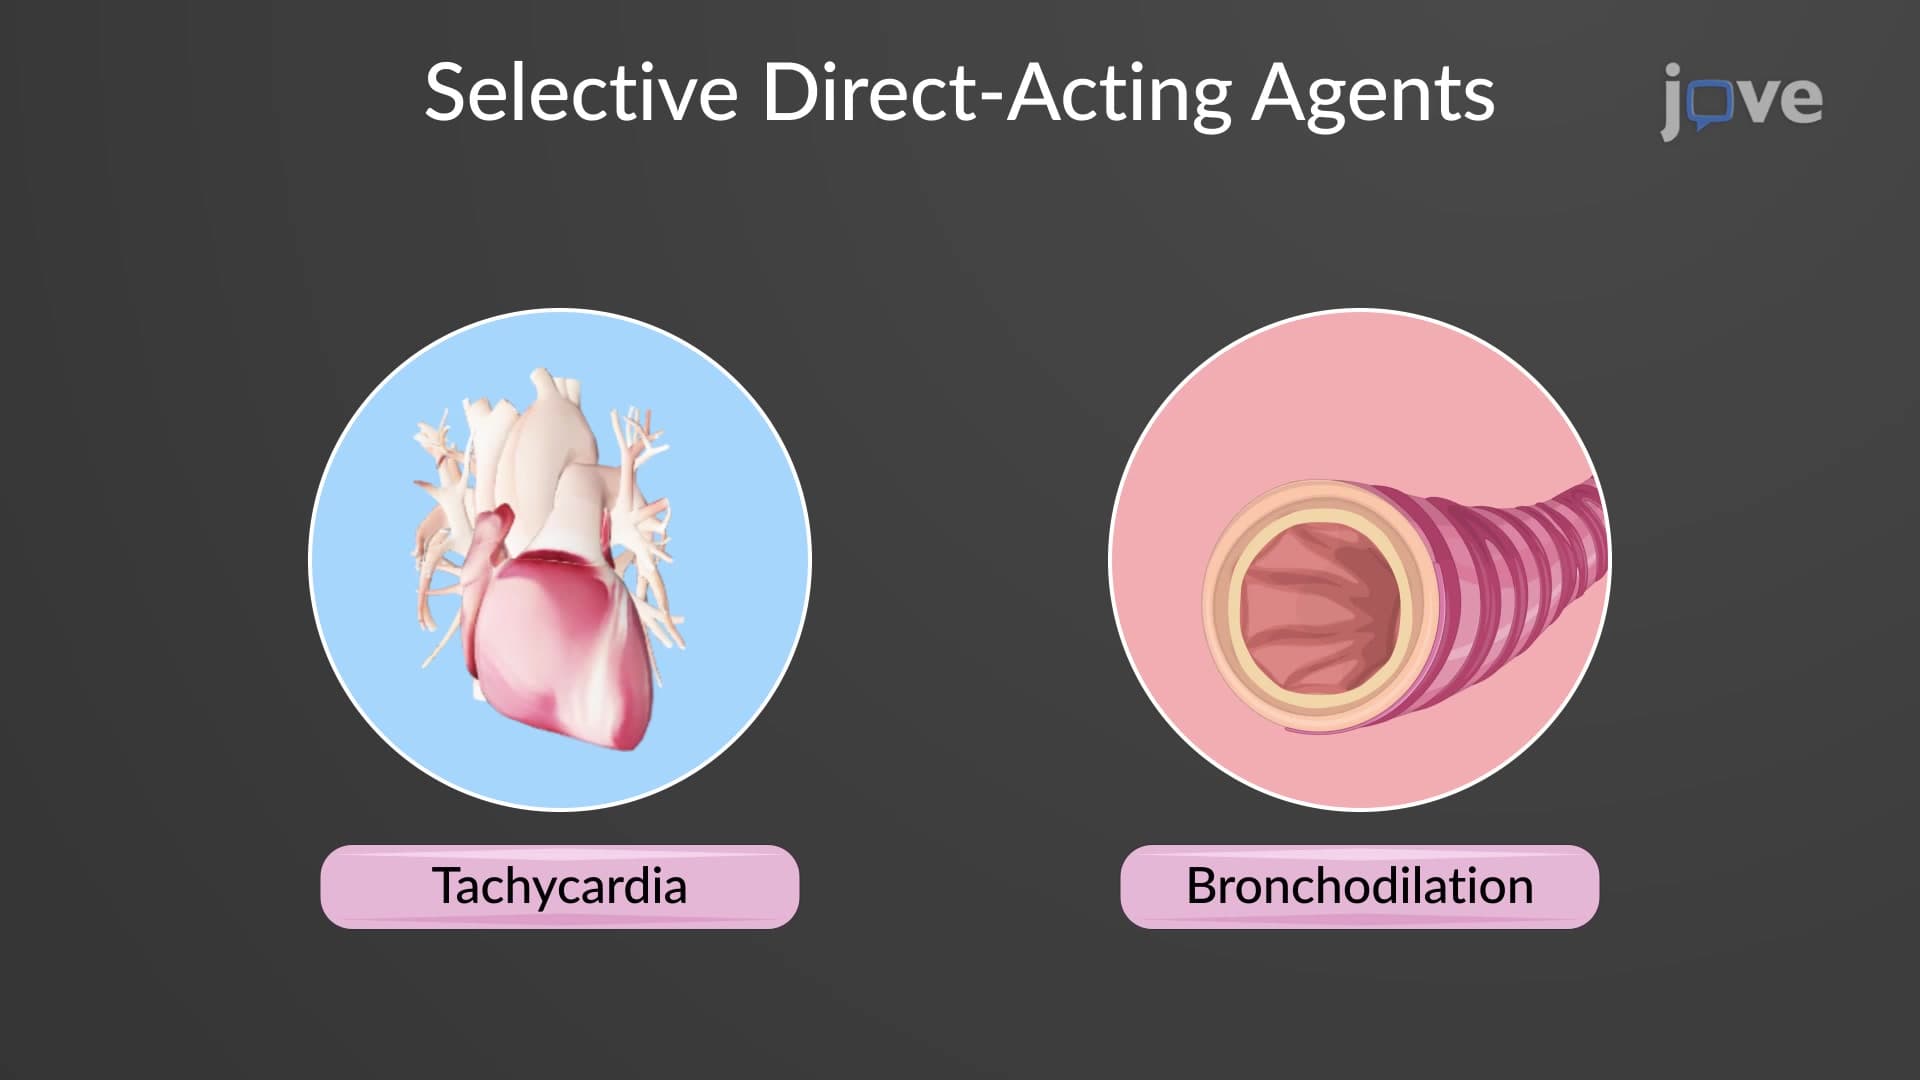
Adrenergic Agonists: Direct-Acting Agents
These agents can be classified...
 01:31
Adrenergic Antagonists: ɑ and β-Receptor Blockers
 01:24
Antiarrhythmic Drugs: Class II Agents as β-Adrenergic Blockers
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management