Related Experiment Video
Updated: Jun 8, 2026
Transtubular Endoscopic Posterolateral Decompression for L5-S1 Lumbar Lateral Disc Herniation
Published on: October 14, 2022
Is spinal anaesthesia at L2-L3 interspace safe in disorders of the vertebral column? A magnetic resonance imaging
N Lin1, J F Bebawy, L Hua
1Department of Anaesthesiology, Beijing Tiantan Hospital, Capital Medical University, Beijing 100050, PR China.

Background:
The varying point at which the spinal cord terminates in the lumbar spinal canal may affect the incidence of spinal cord injuries associated with needle insertion for spinal anaesthesia, especially in patients with vertebral body or intervertebral disc disease. This is a complication which has been frequently reported when spinal needle insertion was performed at higher lumbar spinal levels.
Methods:
We retrospectively reviewed magnetic resonance images of the spine in 1047 Chinese patients to determine the conus medullaris terminus (CMT) in patients with and without vertebral disorders. Patients with tumours in and around the spine and those with congenital spinal anomalies were excluded from the study. Patients with mixed vertebral disorders were also excluded.
Results:
Our data demonstrate that patients with thoracic vertebral compression fractures had lower ending points of the CMT than those without (P<0.05), while patients with lumbar compression fractures did not demonstrate such a correlation. With regard to this difference, females were significantly at higher risk for a lower CMT than males. Conversely, lumbar disc disorders such as intervertebral disc extrusion, herniation, or bulging did not have any significant influence on the level of CMT. Moreover, patients with spondylolisthesis or scoliosis did not demonstrate an abnormal CMT location.
Conclusions:
When performing spinal anaesthesia, anaesthesiologists should be aware of potential differences of the CMT location, particularly in female patients with thoracic vertebral compression fractures, who may have a lower CMT than normal, extending to the level of L2. Performing spinal anaesthesia at the L2-L3 interspace would seem to be ill-advised in this patient population.
Related Concept Videos
 01:11
Local Anesthetics: Clinical Application as Spinal Anesthesia
 01:29
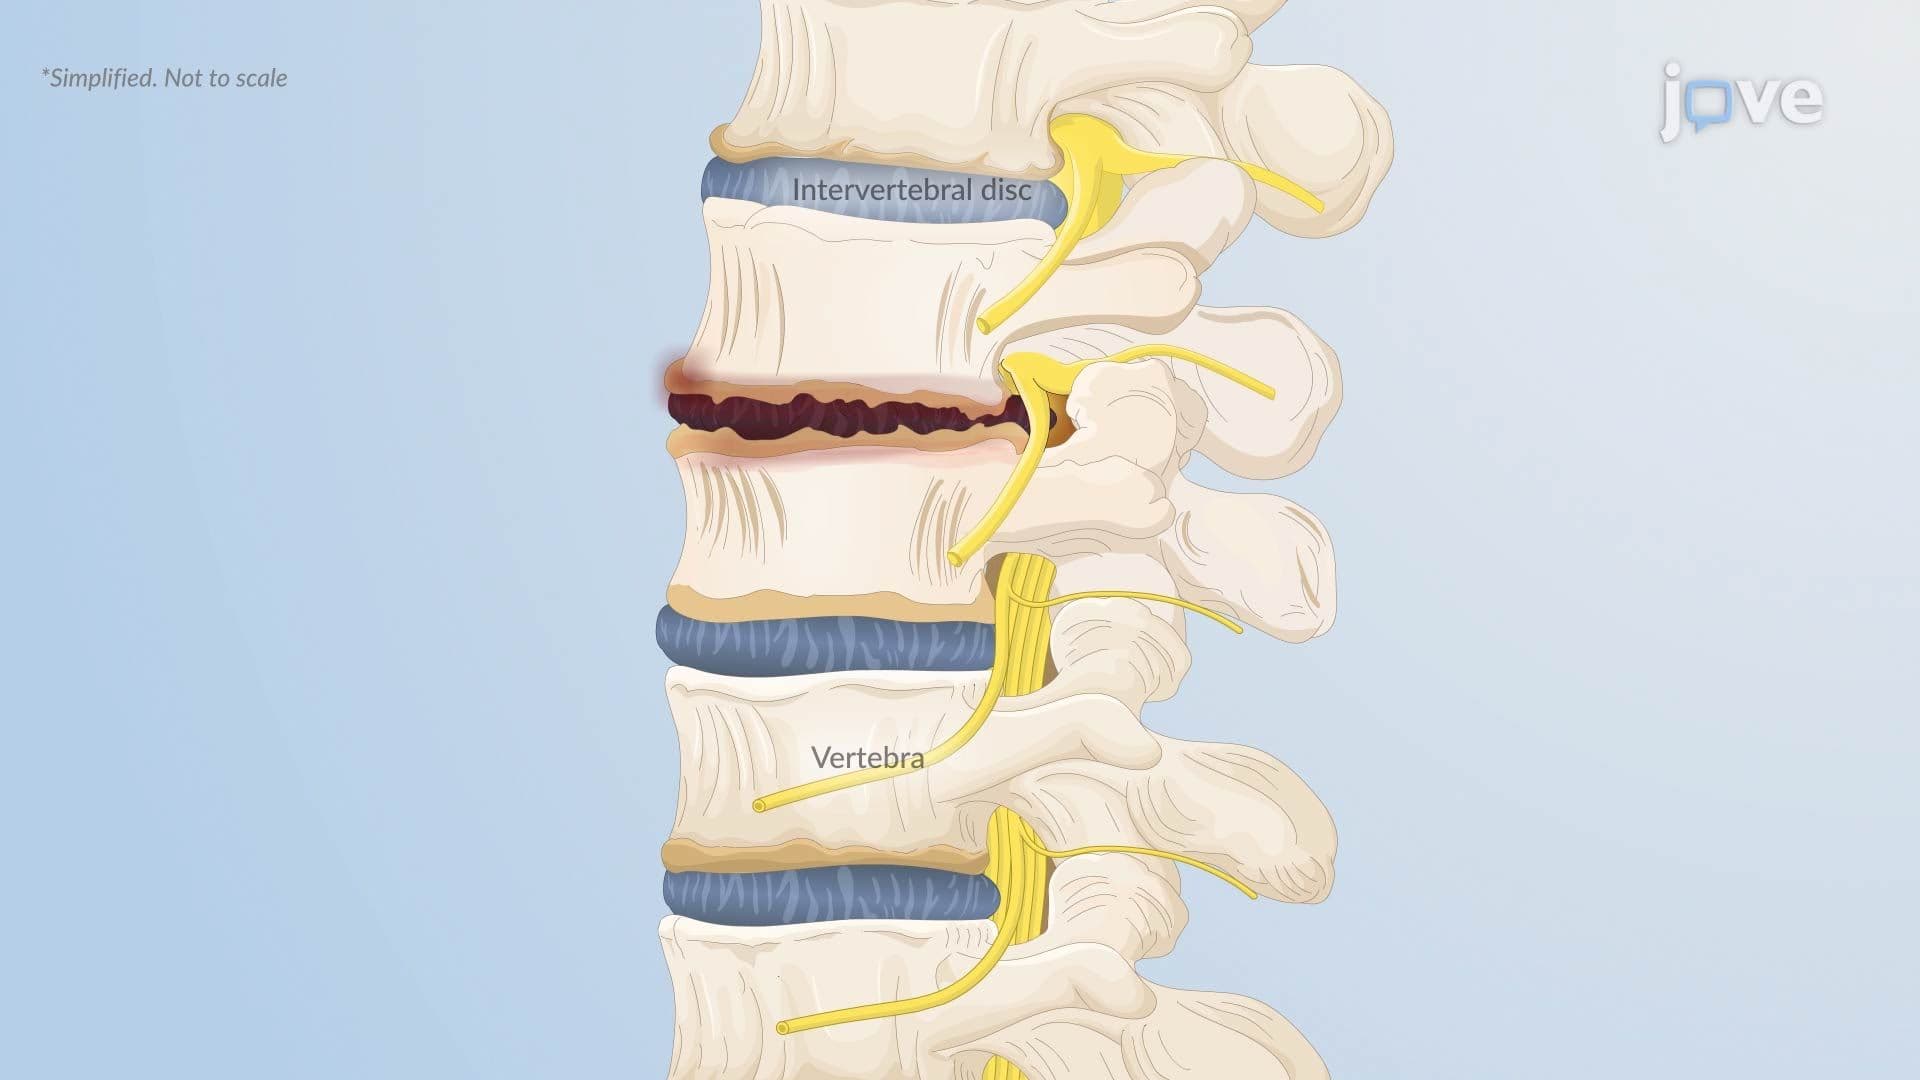
Herniated Intervertebral Disc l: Introduction