Early descriptions of acromegaly and gigantism and their historical evolution as clinical entities

Antonios Mammis1, Jean Anderson Eloy, James K Liu

  • 1Department of Neurological Surgery, Division of Otolaryngology, University of Medicine and Dentistry of New Jersey, New Jersey Medical School, Neurological Institute of New Jersey, Newark, New Jersey 07103, USA.

Neurosurgical Focus
|October 5, 2010
PubMed

Related Concept Videos

Goiter01:27

Goiter

Goiter refers to an abnormal enlargement of the thyroid gland that may appear as a diffuse goiter (uniform enlargement) or nodular (single or multiple nodules). Functionally, it is classified as nontoxic (normal/low hormone levels) or toxic (excess hormone production).PathophysiologyDiffuse thyroid enlargement typically results from prolonged stimulation by thyroid-stimulating hormone (TSH) or TSH-like agents, commonly seen in hypothyroidism or iodine deficiency. In contrast, in hyperthyroid...
Cellular Adaptation II: Hypertrophy01:26

Cellular Adaptation II: Hypertrophy
Hypertrophy is the increase in the size of individual cells, resulting in the enlargement of a tissue or organ. Unlike hyperplasia, which involves an increase in cell number, hypertrophy is characterized by an increase in cell volume. This process often occurs in response to higher functional demand or hormonal stimulation, leading to the production of more structural proteins and organelles, thereby enhancing the cells' work capacity.There are two primary types of hypertrophy: physiological...
Hyperthyroidism I: Introduction01:25

Hyperthyroidism I: Introduction

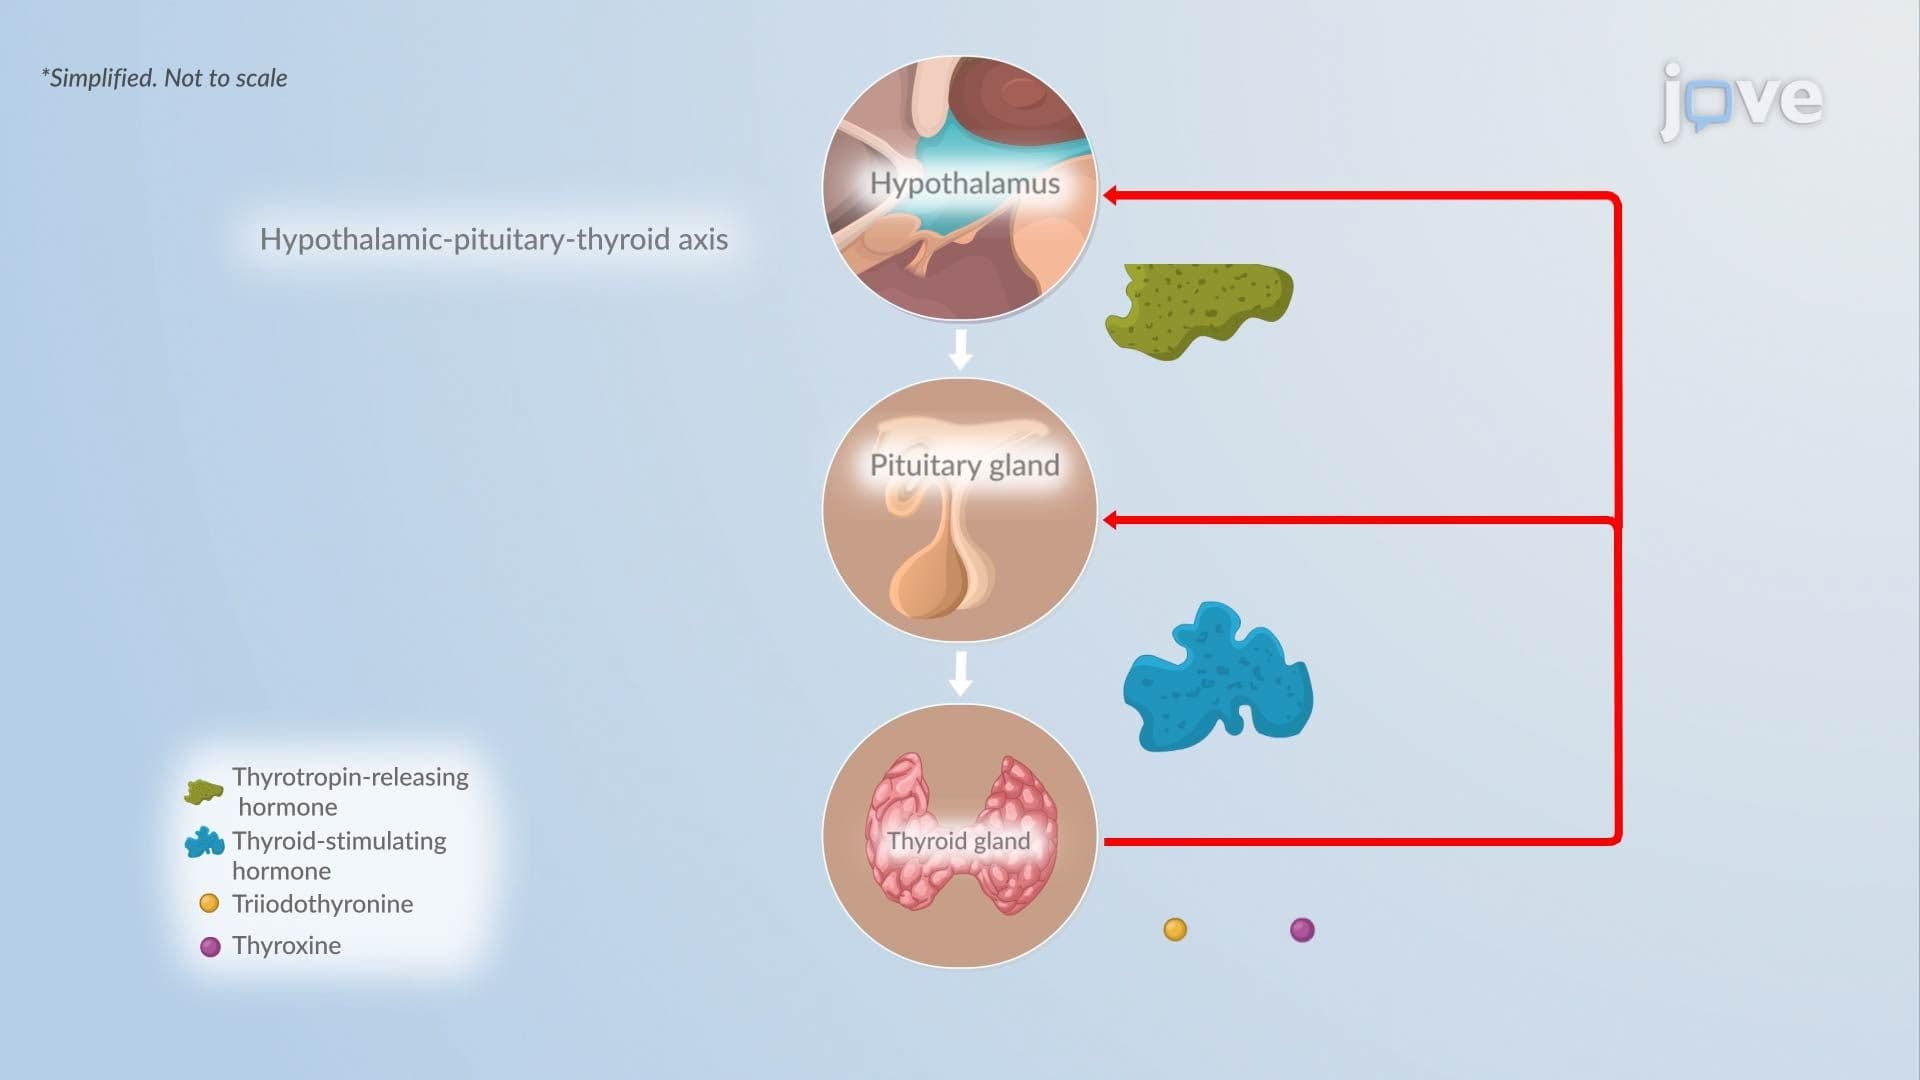
Hyperthyroidism is a type of thyrotoxicosis characterized by the thyroid gland's overproduction of the thyroid hormones triiodothyronine (T3) and thyroxine (T4). This hormone excess increases the basal metabolic rate and enhances sensitivity to catecholamines.DiagnosisDiagnosis is based on clinical features and biochemical testing. It typically shows suppressed thyroid-stimulating hormone (TSH) levels below 0.4 mIU/L, with elevated free T3 and/or T4. Additional tests, including thyroid...
Cushing Syndrome I: Introduction01:26

Cushing Syndrome I: Introduction

Cushing syndrome refers to the collection of clinical manifestations that arise when tissues are exposed to excessive amounts of cortisol or cortisol-like medications over an extended period. Cortisol, a glucocorticoid produced by the adrenal cortex, regulates metabolism, immune responses, and the body’s adaptation to stress. When its concentration remains chronically elevated, these physiological pathways become dysregulated, resulting in the characteristic features of the syndrome.Exogenous...
Cirrhosis I: Introduction01:23

Cirrhosis I: Introduction

Cirrhosis is a chronic, irreversible liver disease characterized by the widespread replacement of healthy liver tissue with fibrotic scar tissue and the formation of regenerative nodules.Etiology of cirrhosisCirrhosis results from sustained liver injury that triggers progressive fibrosis and structural remodeling. The underlying causes are diverse, encompassing common and less frequent clinical conditions. Regardless of the origin, all causes lead to chronic inflammation, hepatocyte loss, and...
Cushing Syndrome II: Pathophysiology01:19

Cushing Syndrome II: Pathophysiology

Cortisol production is normally governed by the hypothalamic–pituitary–adrenal (HPA) axis, which maintains hormonal balance through tightly regulated feedback mechanisms. Disruption of this regulatory system is central to the development of Cushing syndrome, whether the excess cortisol originates from external medications or internal pathology. Persistent cortisol elevation alters metabolism, immune function, and endocrine signaling, producing the characteristic clinical features of the...




