Related Experiment Video
Updated: Jun 7, 2026
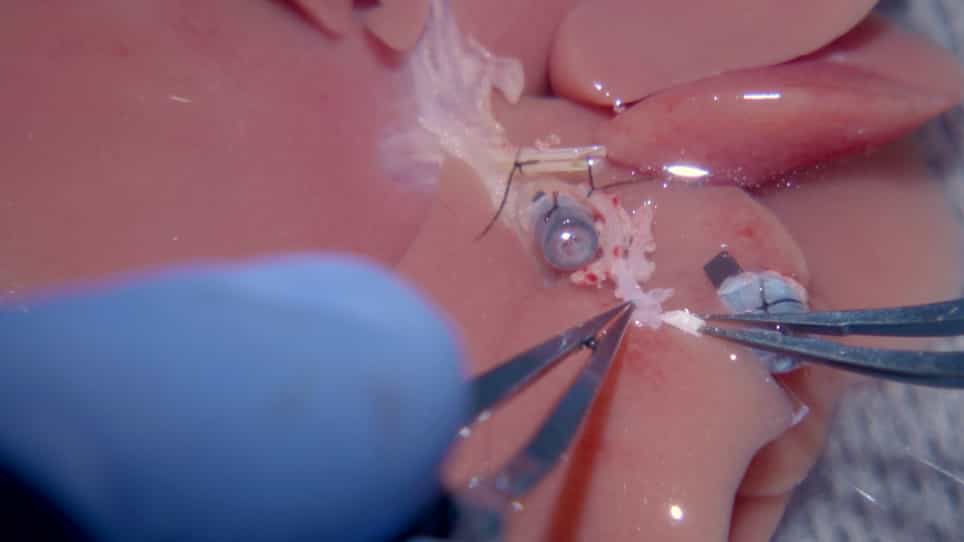

Reduced Complications after Arterial Reconnection in a Rat Model of Orthotopic Liver Transplantation
Published on: November 7, 2020
[Liver transplantation and pregnancy]
Aurélie Revaux1, Jacques Bernuau, Pierre-François Ceccaldi
1Université Paris VII, Assistance publique-Hôpitaux de Paris (AP-HP), hôpital Beaujon, service de gynécologie obstétrique, 92110 Clichy, France.

Abstract:
Patients with liver failure have menstrual cycle irregularities or amenorrhea. Liver transplantation restores menstrual pattern among women with cirrhosis in childbearing years. It is now accepted that a planned pregnancy is possible among liver transplant recipients at least 1 year after liver transplantation, with stable allograft function and under immunosuppressive regimens, to minimize the risks of preterm delivery and pregnancy-induced hypertension. After 1 year, the risk of graft loss decreases and is not related to pregnancy. It is a high-risk pregnancy which requires a specific and regular multidisciplinary joint follow-up (obstetrician, hepatologist, and anaesthesiologist), which leads in most cases to successful outcome for mother and child. But, early prevention and multidisciplinary management of the most common complications (pregnancy-induced hypertension, preeclampsia, and fetal growth restriction) is essential. The prematurity rate, maternal morbidity and mortality are higher than in the general population. Usual immunosuppressive treatments (corticoids, cyclosporine, tacrolimus, azathioprine or mycophenolate mofetil) may require dose adaptation during pregnancy. Immunosuppressive drugs are not teratogenic, but breast feeding is not allowed.


Related Concept Videos
 01:28
Kidney Transplant I: Introduction
 01:26
Kidney Transplant II: Surgical Procedure
 01:24
Tissue Transplantation
The Biology of Tissue Transplantation
The biology of tissue transplantation hinges on the Major Histocompatibility Complex (MHC) molecules. These molecules...
 01:16
Kidney Transplant III: Nursing Management