Related Experiment Video
Updated: Jun 6, 2026
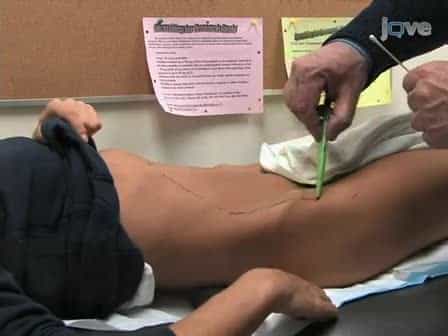

Demonstration of Cutaneous Allodynia in Association with Chronic Pelvic Pain
Published on: June 23, 2009
[Symptomatic approach to chronic neuropathic somatic pelvic and perineal pain]
J-J Labat1, R Robert, D Delavierre
1Centre fédératif de pelvipérinéologie, clinique urologique, CHU Hôtel-Dieu, 1, place Alexis-Ricordeau, 44093 Nantes, France. jjlabat@chu-nantes.fr

Objectives:
To determine the characteristics of neuropathic pain and the somatic nerve lesions most frequently encountered in the context of chronic pelvic and perineal pain.
Material And Methods:
Review of the literature devoted to pelvic and perineal neuralgia.
Results:
The diagnosis of pelvic and perineal pain related to a somatic nerve lesion is essentially clinical. The topography of the pain and its characteristics (burning, paraesthesia, etc.) can help to link the pain to the neurological territory involved. Complementary investigations are poorly contributive. Two main systems are involved in this region: sacral nerve roots that give rise to the pudendal nerve and the posterior cutaneous nerve of the thigh, thoracolumbar nerve roots that give rise to the ilioinguinal, iliohypogastric, genitofemoral and obturator nerves. The first system is essentially perineal and the second is essentially anterior inguinoperineal.
Discussion:
Pudendal neuralgia is the most common and most disabling form of pelvic pain. It presents as unilateral or bilateral burning pain of the anterior or posterior perineum that is worse on sitting and relieved by standing, not usually associated with night pain. It is related to a ligamentous nerve compression mechanism. Inferior cluneal neuralgia tends to be experienced as ischial and lateroperineal pain, and is sometimes accompanied by pain in a truncated sciatic territory, corresponding to projections of the posterior cutaneous nerve of the thigh. This neuralgia can be related to a piriformis syndrome or an ischial lesion. Sacral nerve root lesions do not cause acute pain, but are accompanied by sacral sensory loss and urinary, anorectal or sexual disorders. Pain related to ilioinguinal, iliohypogastric and genitofemoral nerves is generally secondary to surgical trauma and scars. Although these various lesions are sometimes difficult to distinguish from each other, an essential part of management consists of performing a local anesthetic block at the trigger point detected in the scar. Referred pain derived from the spinal cord due to thoracolumbar painful minor intervertebral dysfunction is experienced in the inguinal region, pubis, labium majorum and sometimes the trochanter, and only a complete clinical examination of the thoracolumbar region can demonstrate local signs (posterior facet joint pain at several levels, fibromyalgia).
More Related Videos
 07:20
Intraoperative Detection of Subtle Endometriosis: A Novel Paradigm for Detection and Treatment of Pelvic Pain Associated with the Loss of Peritoneal Integrity
Published on: December 21, 2012
 02:41
Acupoint Catgut Embedding for Treatment of Chronic Pelvic Pain Due to the Sequelae of Pelvic Inflammatory Disease
Published on: May 3, 2024
Related Concept Videos
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
 01:25
Analgesia and Pain Management
 01:21
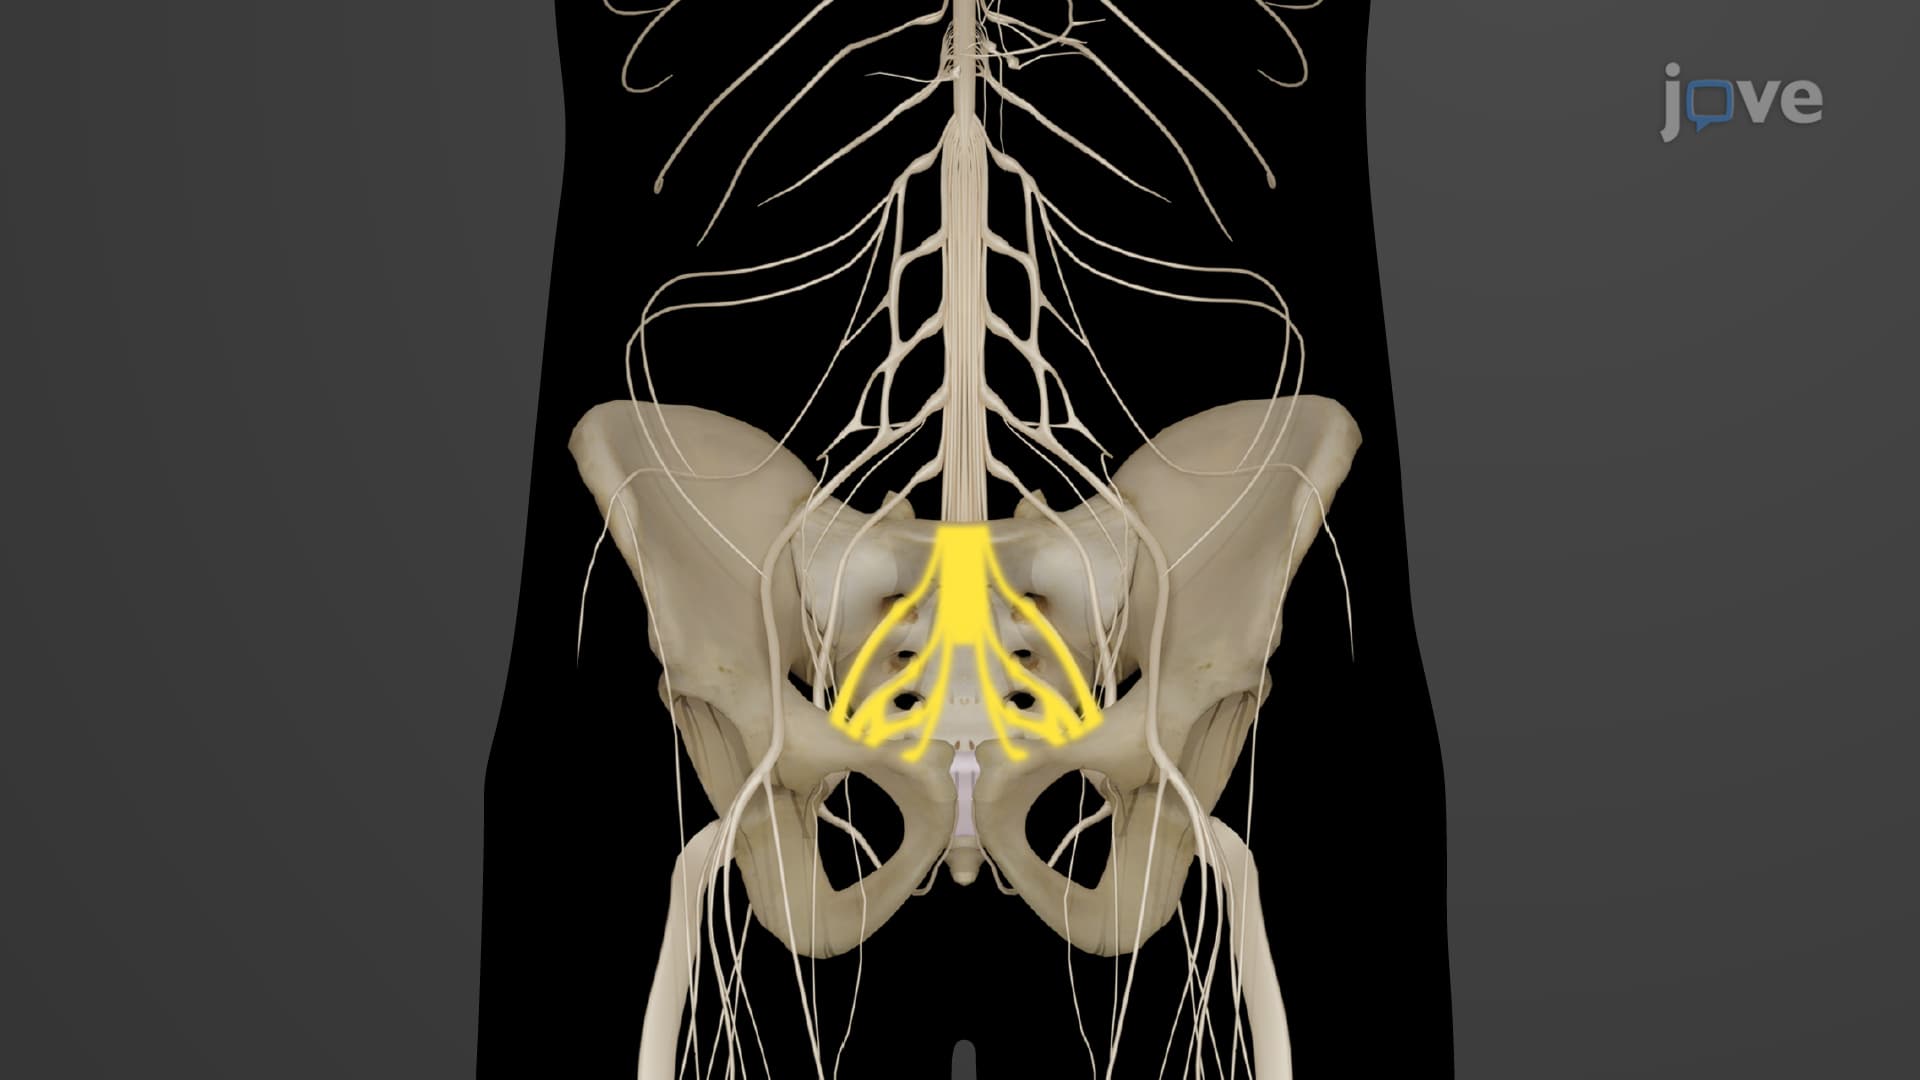
Spinal Nerves: Plexus II
The Lumbar Plexus
The lumbar plexus is situated within the lumbar region of the back and is primarily formed by the first four lumbar spinal nerves (L1 to L4). This plexus extends its branches into several nerves, including the...