Related Experiment Video
Updated: Jun 6, 2026


Multiplex Therapeutic Drug Monitoring by Isotope-dilution HPLC-MS/MS of Antibiotics in Critical Illnesses
Published on: August 30, 2018
Vancomycin pharmacokinetic-pharmacodynamic parameters to optimize dosage administration in critically ill children
Gustavo A Giachetto1, Héctor M Telechea, Noelia Speranza
1Universidad de la República, Montevideo, Uruguay.

Insights
Critically ill children often have altered vancomycin pharmacokinetics, requiring individualized dosing. Most pediatric patients do not achieve the target vancomycin area under the curve/minimal inhibitory concentration ratio for Staphylococcus aureus with standard regimens.
Area of Science:
- Pediatric Critical Care Medicine
- Pharmacokinetics and Pharmacodynamics
- Infectious Diseases
Background:
- Critically ill children exhibit altered drug pharmacokinetics.
- Current vancomycin dosing may not achieve therapeutic concentrations in this population.
Purpose of the Study:
- To determine vancomycin pharmacokinetic parameters in critically ill children.
- To estimate the vancomycin area under the curve at 24 hrs/minimal inhibitory concentration (MIC) ratio against Staphylococcus aureus.
Main Methods:
- Prospective study of 22 critically ill children receiving vancomycin.
- Vancomycin serum concentrations (Cmax and Cmin) measured on days 1 and 3.
- Pharmacokinetic parameters (half-life, volume of distribution, clearance, AUC24) calculated.
Main Results:
- Therapeutic vancomycin concentrations were not consistently achieved.
- Mean half-life increased from day 1 to day 3.
- Fewer than half of the children achieved an AUC24/MIC ratio >400 for S. aureus (MIC=1 μg/mL).
Conclusions:
- Critically ill children have altered vancomycin pharmacokinetics.
- Therapeutic drug monitoring and individualized dosing are essential.
- Current vancomycin dosages are often insufficient to reach target AUC24/MIC ratios.
Objective:
Critically ill children may present changes in pharmacokinetic parameters and may not reach effective concentrations of vancomycin with current dosages. The objective of this study is to calculate vancomycin pharmacokinetic parameters in critically ill children and to estimate area under the curve at 24 hrs/minimal inhibitory concentration reached for Staphylococcus aureus.
Design, Setting, And Patients:
Children treated with vancomycin, hospitalized in the Intensive Care Unit of the Pediatric Hospital-Centro Hospitalario Pereira Rossell, were included. Samples to determine vancomycin serum concentration were obtained on first and third days of treatment, 1 hr after the end of the third daily dose administration (maximum drug concentration) and 15 mins before the fourth (minimum drug concentration). Half-life elimination, volume of distribution, clearance, and area under the curve at 24 hrs were estimated. Vancomycin concentration values of 20-40 μg/mL (maximum drug concentration) and 5-10 μg/mL (minimum drug concentration) were considered therapeutic.
Measurements And Main Results:
Twenty-two children were included. On day 1, seven of 18 children for maximum drug concentration and 16 of 22 for minimum drug concentration reached concentrations in therapeutic range; on day 3, seven of 16 children for maximum drug concentration and 11 of 17 for minimum drug concentration did. Mean values of maximum drug concentration and minimum drug concentration were higher in children with negative water balance. Mean value of half-life elimination increased from day 1 to day 3. Considering a value of minimal inhibitory concentration for S. aureus of 1 μg/mL, nine of 18 children reached a relationship area under the curve at 24 hrs/minimal inhibitory concentration >400 on day 1 and seven of 15 on day 3. Considering a minimal inhibitory concentration of 2 μg/mL, one child reached it on day 1 and one on day 3.
Conclusions:
Critically ill children show changes in pharmacokinetic parameters. Serum concentration monitorization is necessary for dosage individualization. Most children do not reach an area under the curve at 24 hrs/minimal inhibitory concentration >400 with current dosage.

Related Concept Videos
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:29
Drug Dosing: Infants and Children
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism
 01:17
Pharmacokinetics in Pediatric Patients: Drug Distribution
 01:23
Pharmacokinetics in Pediatric Patients: Overview and Drug Absorption
 01:20
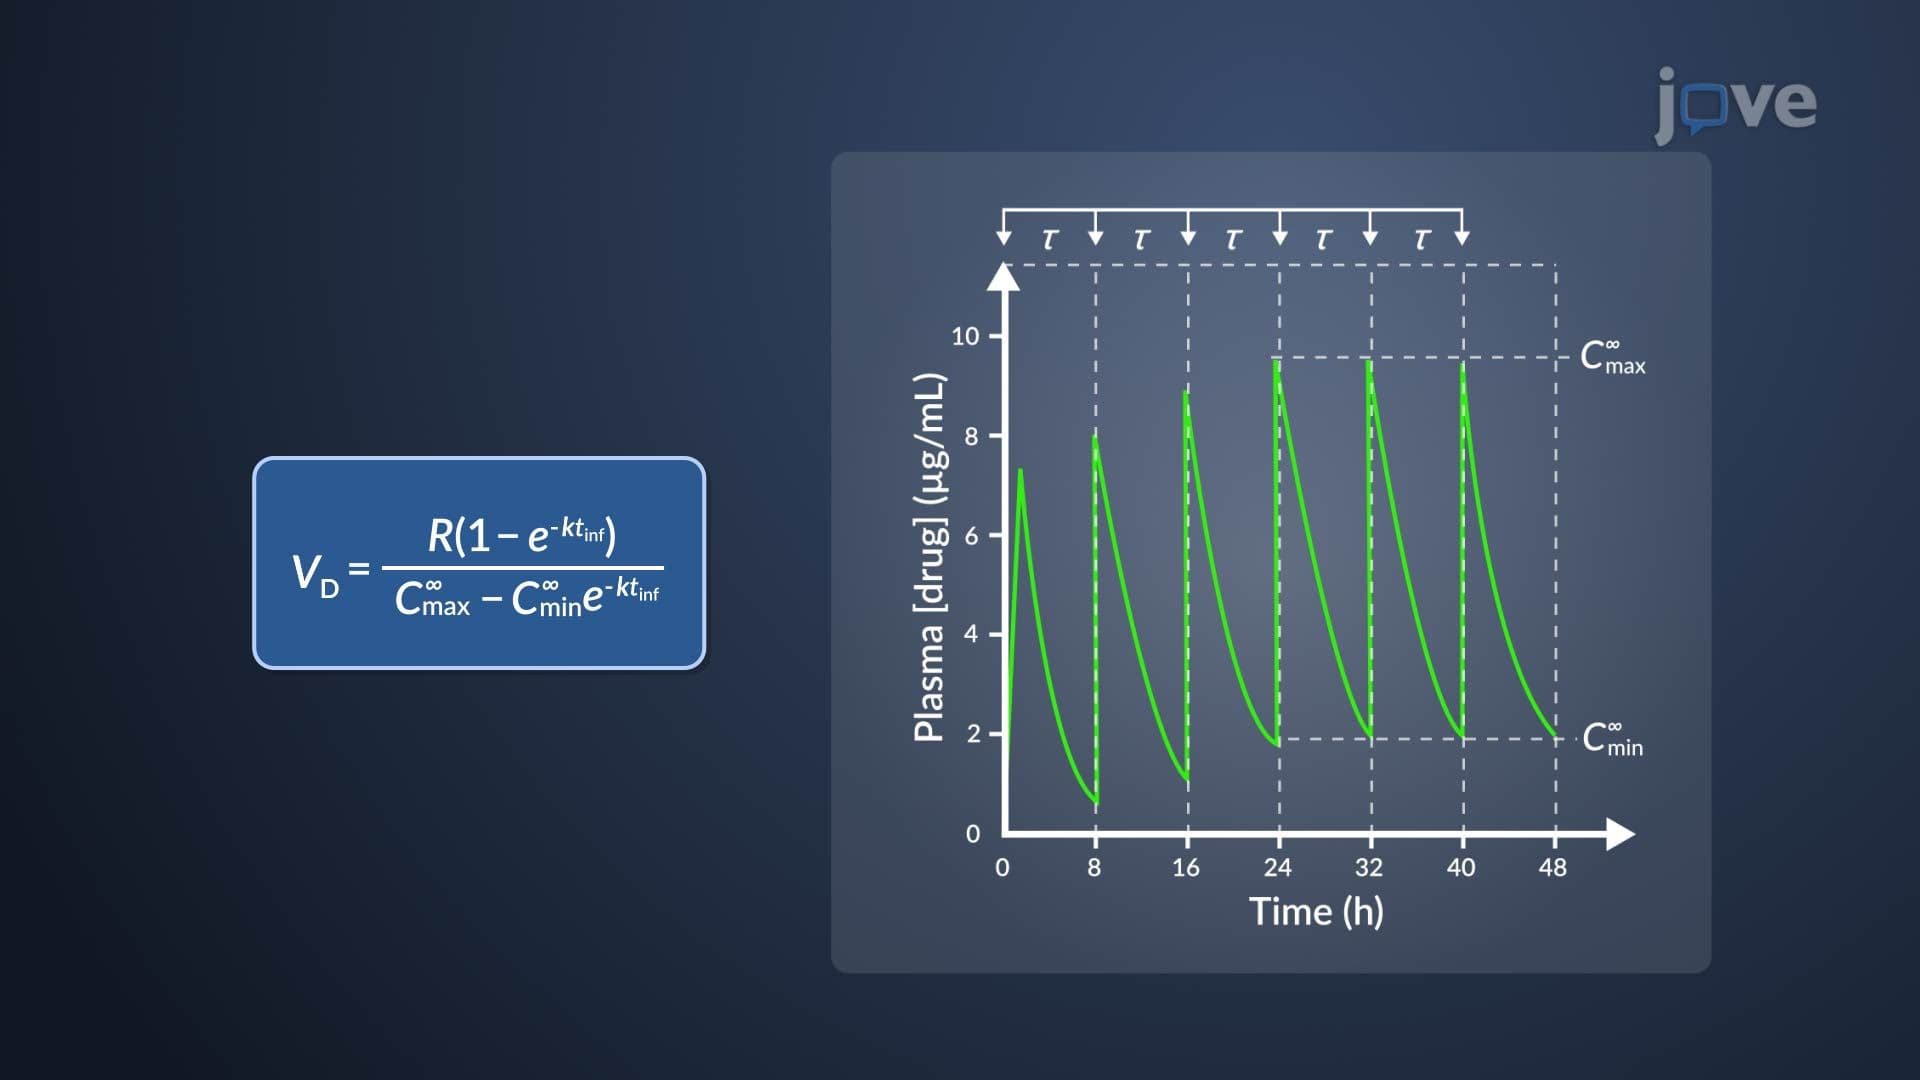
Estimation of k and VD of Aminoglycosides