

Coronary disease in emergency department chest pain patients with recent negative stress testing
Jonathan Walker1, Michael Galuska, David Vega
1York Hospital, Department of Emergency Medicine, York, PA.

Insights
Negative cardiac stress tests are unreliable for ruling out coronary artery disease (CAD). Patients with inconclusive tests have a similar likelihood of CAD, highlighting the need for further diagnostic evaluation in emergency department chest pain cases.
Area of Science:
- Cardiology
- Diagnostic Imaging
- Emergency Medicine
Background:
- Cardiac stress tests are crucial for diagnosing coronary artery disease (CAD).
- However, current stress test methods exhibit incomplete sensitivity and specificity.
- This limitation necessitates further investigation into their diagnostic accuracy.
Purpose of the Study:
- To determine the prevalence of significant CAD in emergency department (ED) patients with chest pain.
- To analyze patients who recently underwent a negative or inconclusive cardiac stress test.
- To assess the diagnostic utility of stress tests in this high-risk population.
Main Methods:
- A retrospective chart review was conducted on 164 patients presenting to the ED with chest pain.
- Inclusion criteria included a recent (within three years) negative or inconclusive cardiac stress test and hospital admission.
- Coronary artery disease (CAD) diagnosis was confirmed via troponin levels, percutaneous coronary intervention, or inpatient stress test results.
Main Results:
- Out of 164 patients, 74.4% had negative stress tests and 25.6% had inconclusive tests.
- Overall, 20.7% of patients were diagnosed with CAD.
- The CAD prevalence was similar between those with negative (20.5%) and inconclusive (21.4%) stress tests (p = .973).
Conclusions:
- Negative cardiac stress tests should not be relied upon to exclude CAD.
- Patients with negative stress tests are as likely to have CAD as those with inconclusive results.
- This underscores the inadequacy of stress test sensitivity in ruling out CAD.
Background:
Cardiac stress tests for diagnosis of coronary artery disease (CAD) are incompletely sensitive and specific.
Objective:
We examined the frequency of significant CAD in patients presenting to the emergency department (ED) with chest pain who have had a recent negative or inconclusive (<85% of predicted maximum heart rate) cardiac stress test.
Methods:
This was a retrospective chart review of patients identified from ED and cardiology registries at the study hospital. We included patients presenting to the ED with a chief complaint of chest pain, with a negative cardiac stress test in the past three years as the last cardiac test, and hospital admission. One-hundred sixty-four patients met the inclusion criteria. Their admission was reviewed for diagnosis of CAD by positive serum troponin, percutaneous coronary intervention, or positive stress test while an inpatient.
Results:
Of 164 patients, 122(74.4%, 95% CI 67.7, 81.1) had a negative stress test prior to the index admission, while 42 (25.6%, 95% CI 18.9, 32.3) had otherwise normal but inconclusive stress tests. Thirty-four (20.7%, 95% CI 14.4,27.0) of the included patients were determined to have CAD. Twenty-five of the 122 patients (20.5%, 95% CI 13.3, 27.7) had negative pre-admission stress tests and nine of 42 patients (21.4%, 95% CI 9.0, 33.8) had inclusive stress tests of CAD. A statistical comparison between these two proportions showed no significant difference (p = .973).
Conclusion:
Due to inadequate sensitivity, negative non-invasive cardiac stress tests should not be used to rule out CAD. Patients with negative stress tests are just as likely to have CAD as patients with inconclusive stress tests.


Related Concept Videos
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:26
Exercise Stress Test
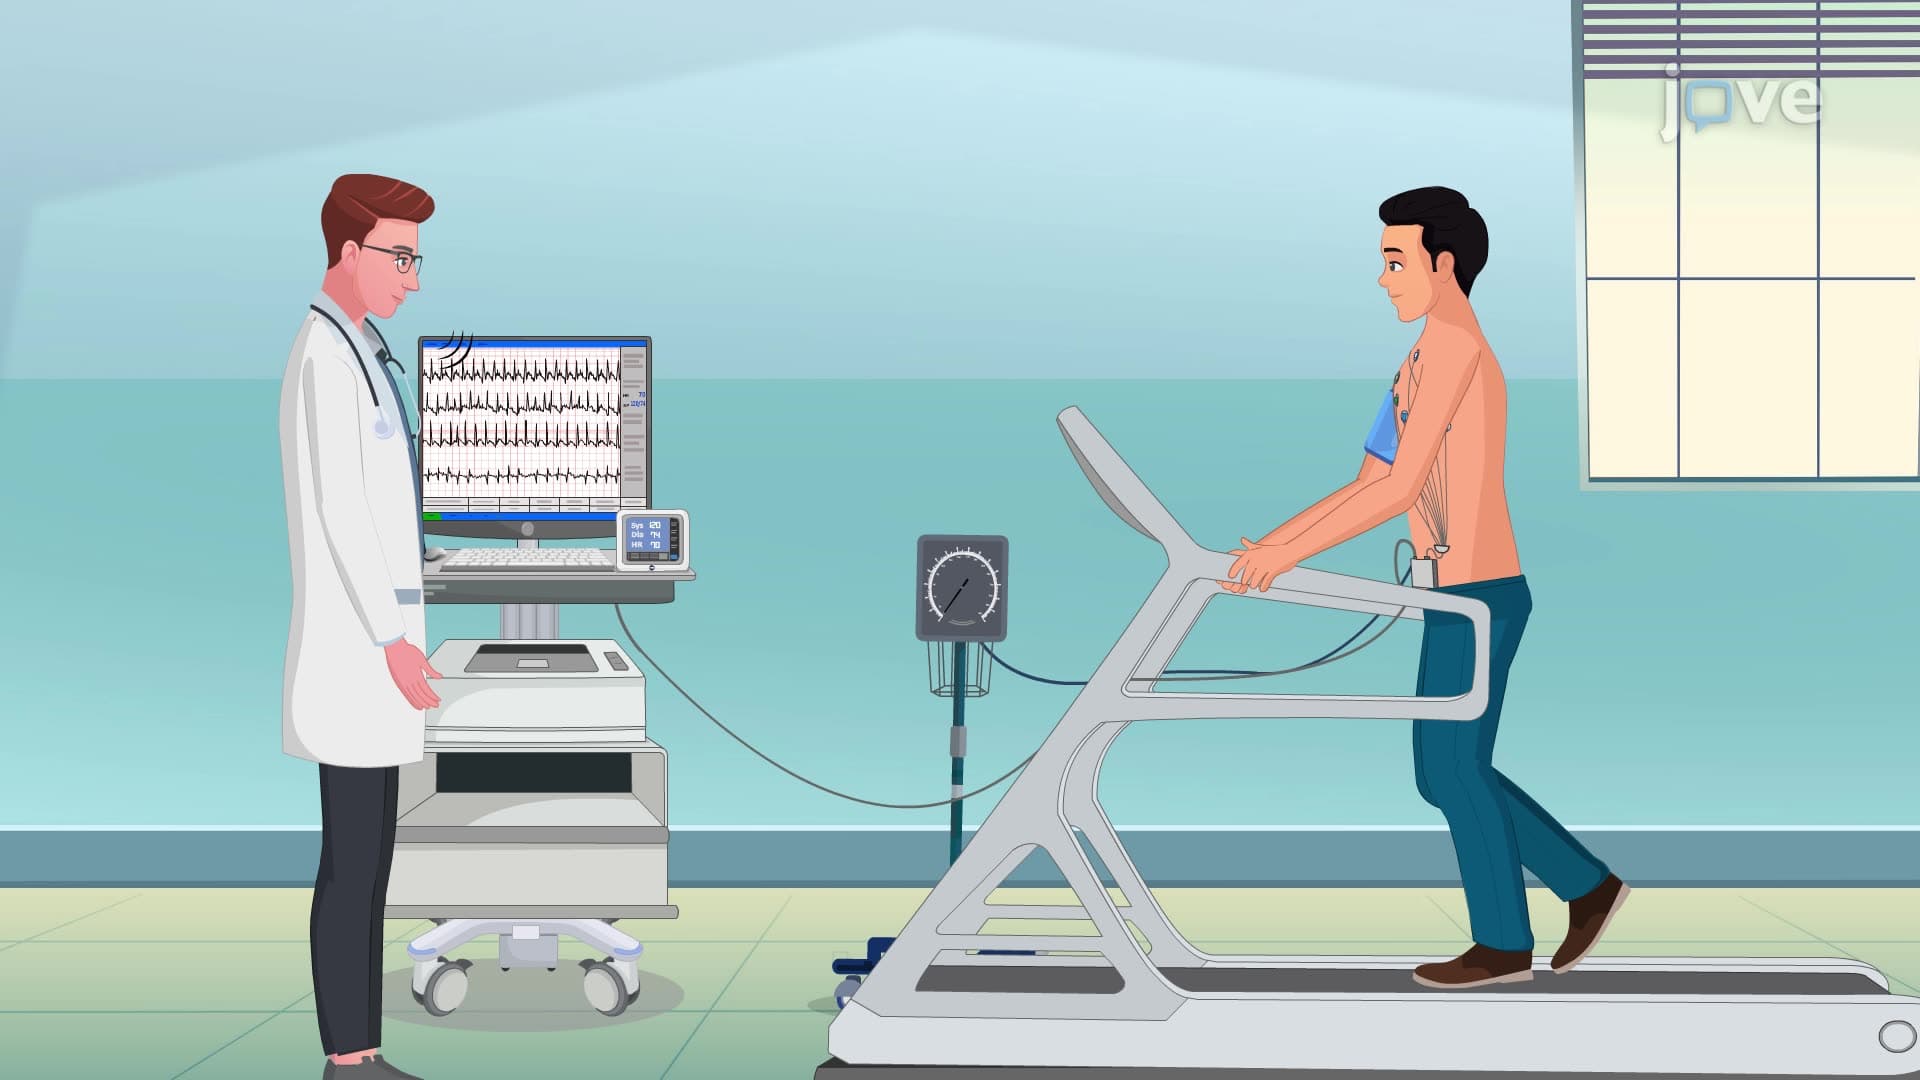
Exercise stress testing, commonly known as a treadmill test, is a noninvasive procedure used to evaluate cardiovascular function and diagnose heart conditions.
Definition
An exercise stress test measures the heart's response to exertion using a treadmill or stationary bicycle. Chest electrodes record the heart's electrical activity through an ECG, and blood pressure is monitored regularly.
Purposes
 01:29
Angina III: Clinical Manifestations and Assessment
 01:30
Acute Coronary Syndrome I: Introduction
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations
 01:26
Acute Coronary Syndrome V: Nursing Management