
Effects of potassium channel modulators on myogenic spontaneous phasic contractile activity in human detrusor from
Stephanie Oger1, Delphine Behr-Roussel, Diane Gorny
1Pelvipharm, Orsay Parc Bat Cèdre, Orsay, France.

Objective:
To characterize the spontaneous contractile activity (SCA) developed by detrusor from patients with neurogenic detrusor overactivity (NDO) because the alteration of detrusor properties plays a critical role in the pathogenesis of detrusor overactivity, as well as to evaluate the role of K(ATP) and K(Ca) channels on this SCA because these channels regulate detrusor SCA in many species, including humans without overactive bladder (OAB).
Patients And Methods:
Human bladder samples were obtained from 44 patients undergoing cystectomy for bladder cancer with no known OAB symptoms and from 38 patients suffering from urodynamically diagnosed NDO. Detrusor strips with or without urothelium/suburothelium were mounted isometrically in organ baths filled with Krebs-HEPES (37 °C; 95% O(2) /5% CO(2) ). Strips were incubated with 10 µm pinacidil (K(ATP) opener) followed by 10 µm glibenclamide (K(ATP) blocker). In another set of experiments, strips were incubated with 30 µm NS-1619 (BK(Ca) opener) followed by 100 nm iberiotoxin (BK(Ca) blocker) or with 100 nm apamin (SK(Ca) blocker).
Results:
SCA occurred more frequently with larger amplitude and area under the curve in detrusor strips from NDO patients compared to control patients. The presence of urothelium/suburothelium did not significantly modify SCA in either patient population. Pinacidil markedly inhibited SCA of detrusor strips from control and NDO patients. This effect was reversed by glibenclamide. By contrast, NS-1619 followed by iberiotoxin did not elicit any significant changes in SCA from NDO patients, contrary to control patients.
Conclusions:
K(ATP) and SK(Ca) channels regulate SCA of NDO patients' detrusor strips. By contrast, BK(Ca) channels are not involved in the regulation of detrusor SCA in NDO patients, whereas they regulate SCA in control patients. These results should be considered in the development of K(+) channels openers for the treatment of NDO. Moreover, SCA observed in vitro should be regarded as an in vitro modelling of human NDO.


Related Concept Videos
 01:27
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacological Actions
Although all competitive neuromuscular blockers are designed...
 01:28
Antihypertensive Drugs: Potassium-Sparing Diuretics
 01:17
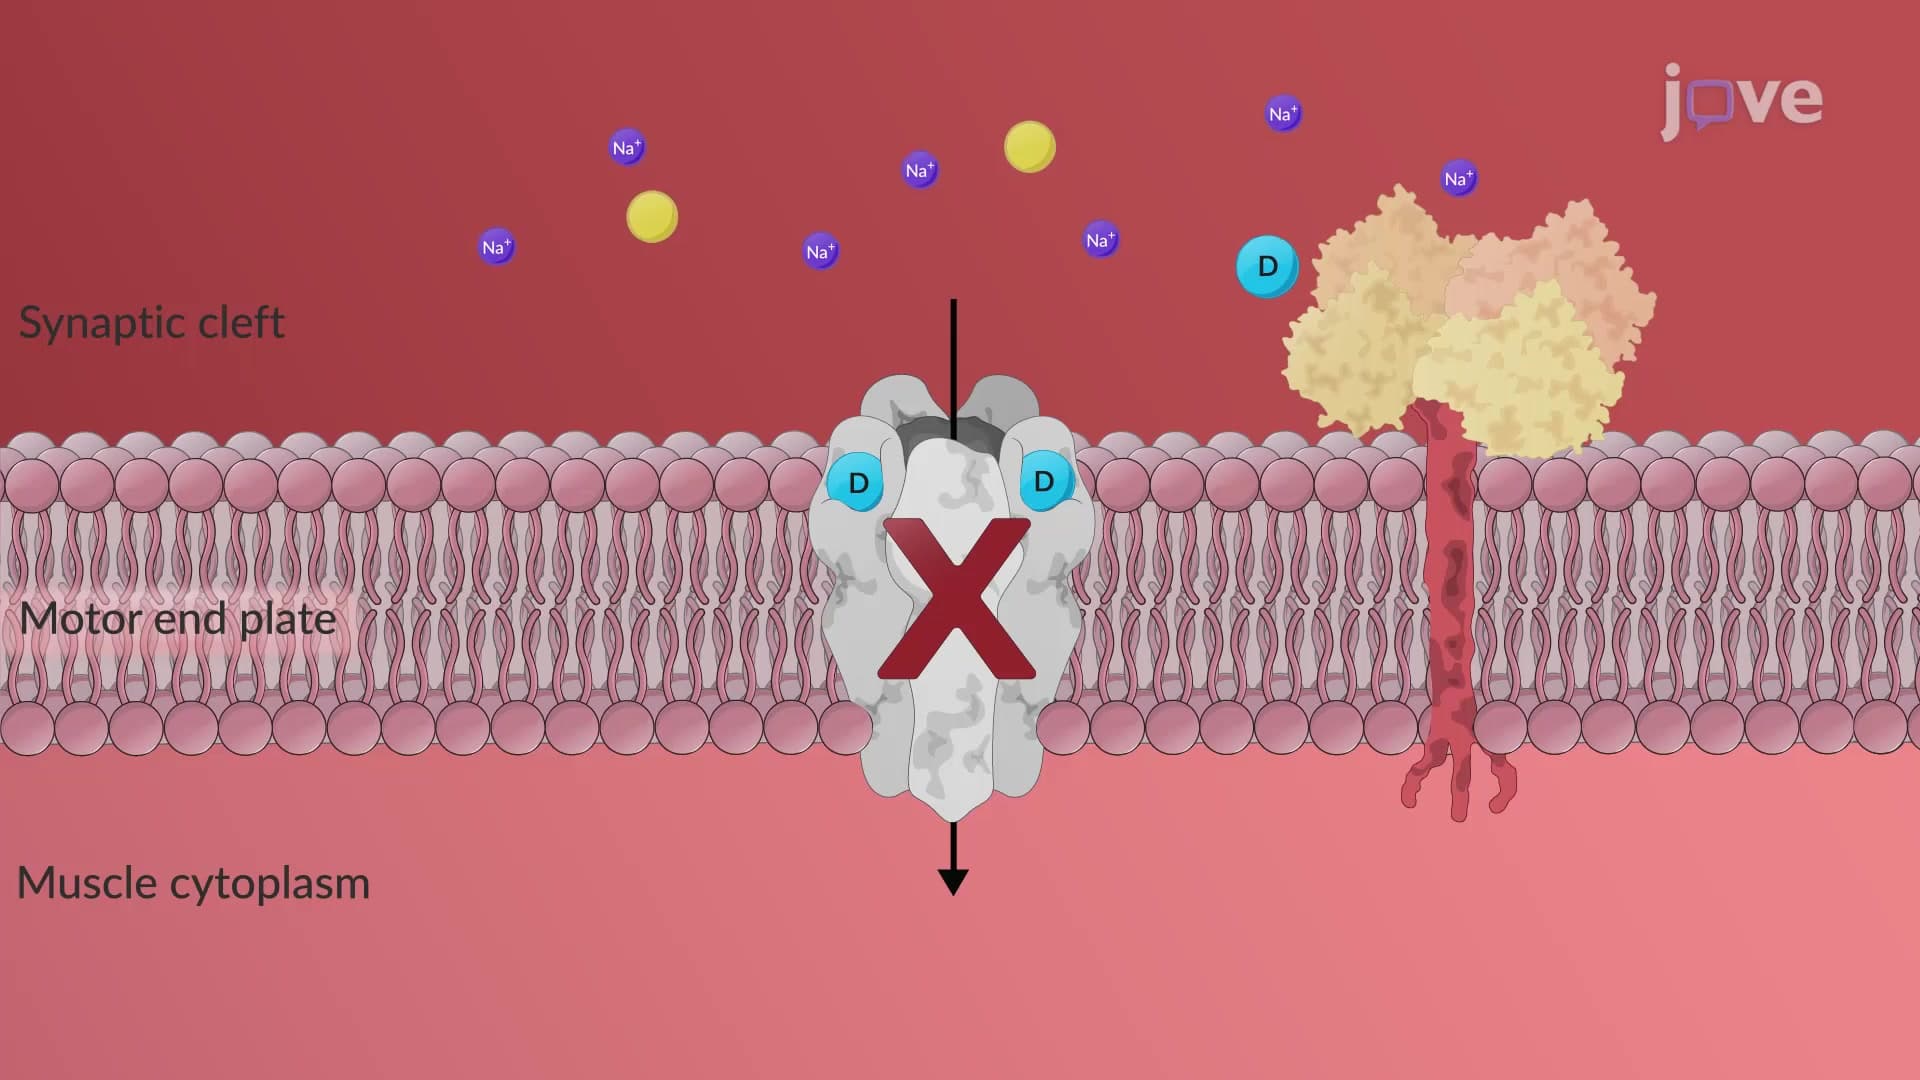
Nondepolarizing (Competitive) Neuromuscular Blockers: Mechanism of Action
Competitive antagonists prevent acetylcholine from binding to its receptor, inhibiting membrane depolarization. Without conformational changes or intrinsic...
 01:21
Skeletal Muscle Relaxants: Adverse Effects
Unlike...
 00:59
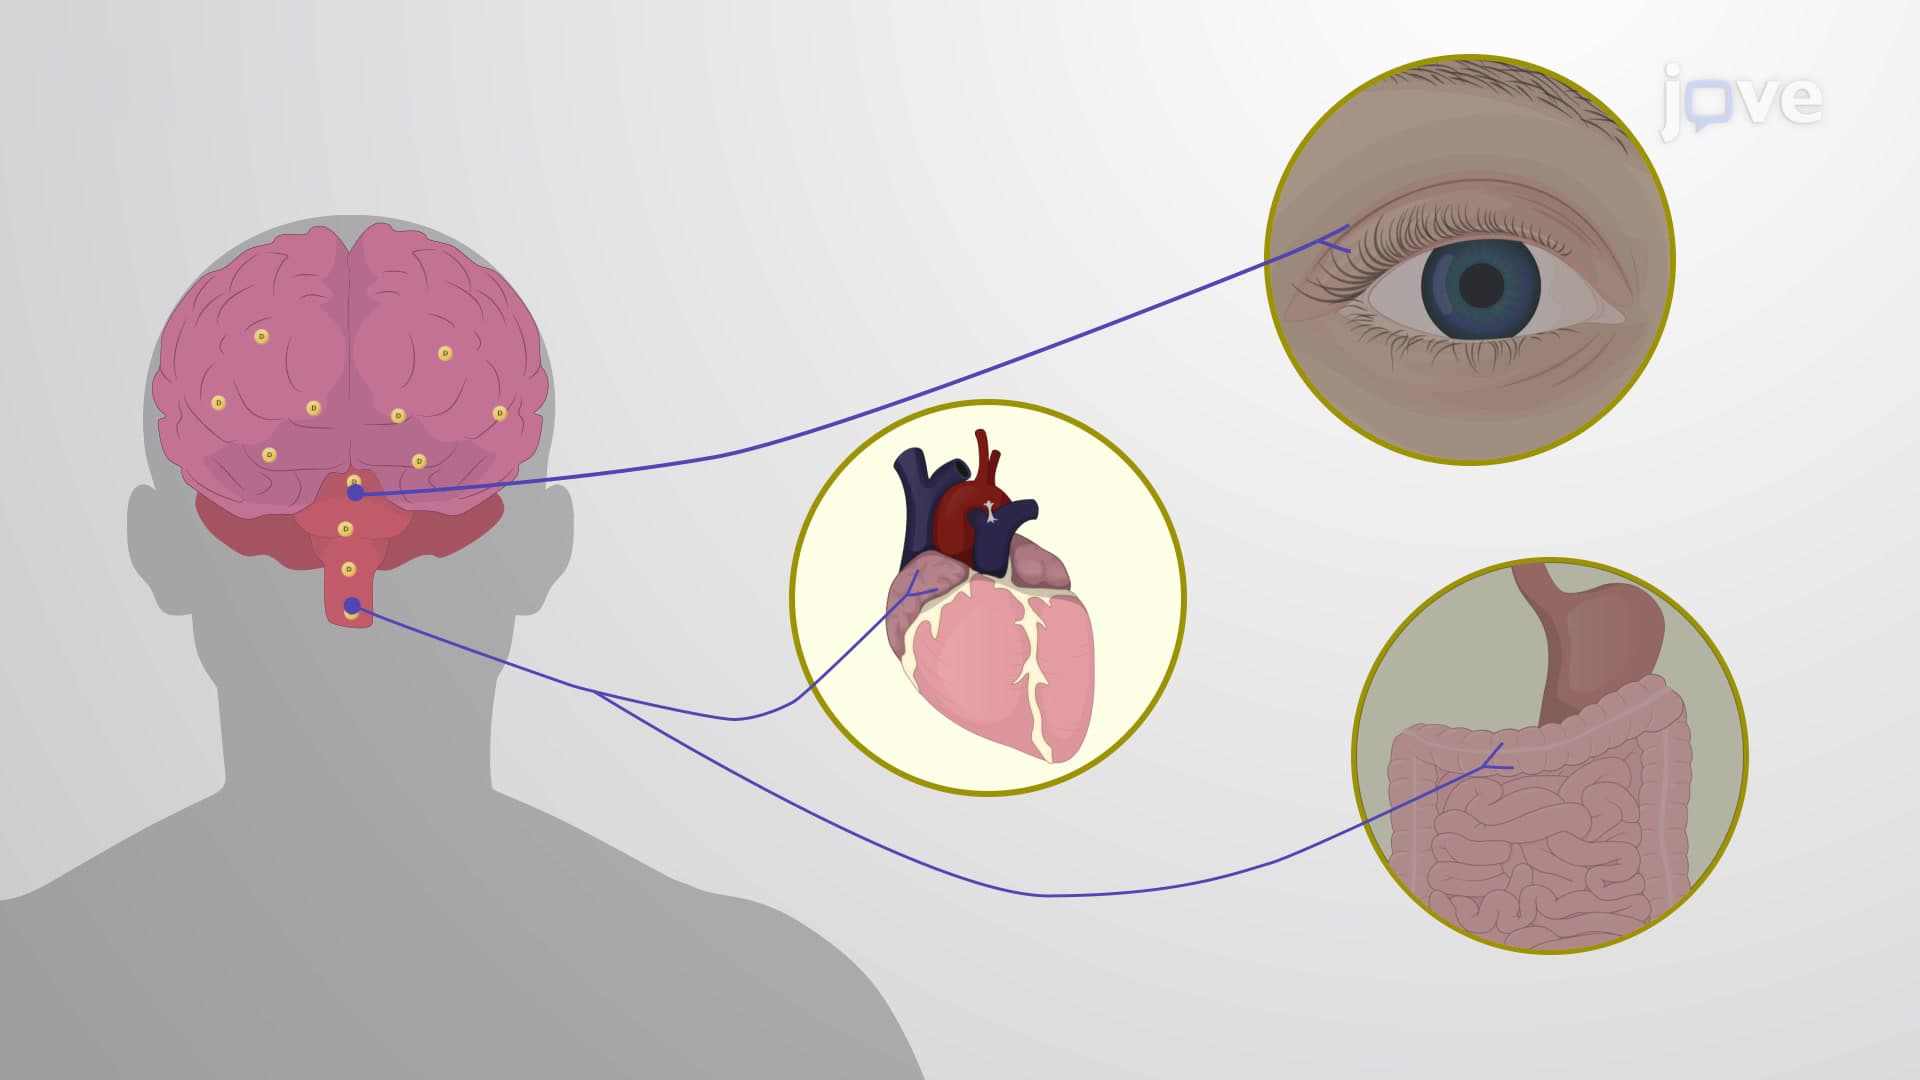
Direct-Acting Cholinergic Agonists: Pharmacological Actions
 01:28
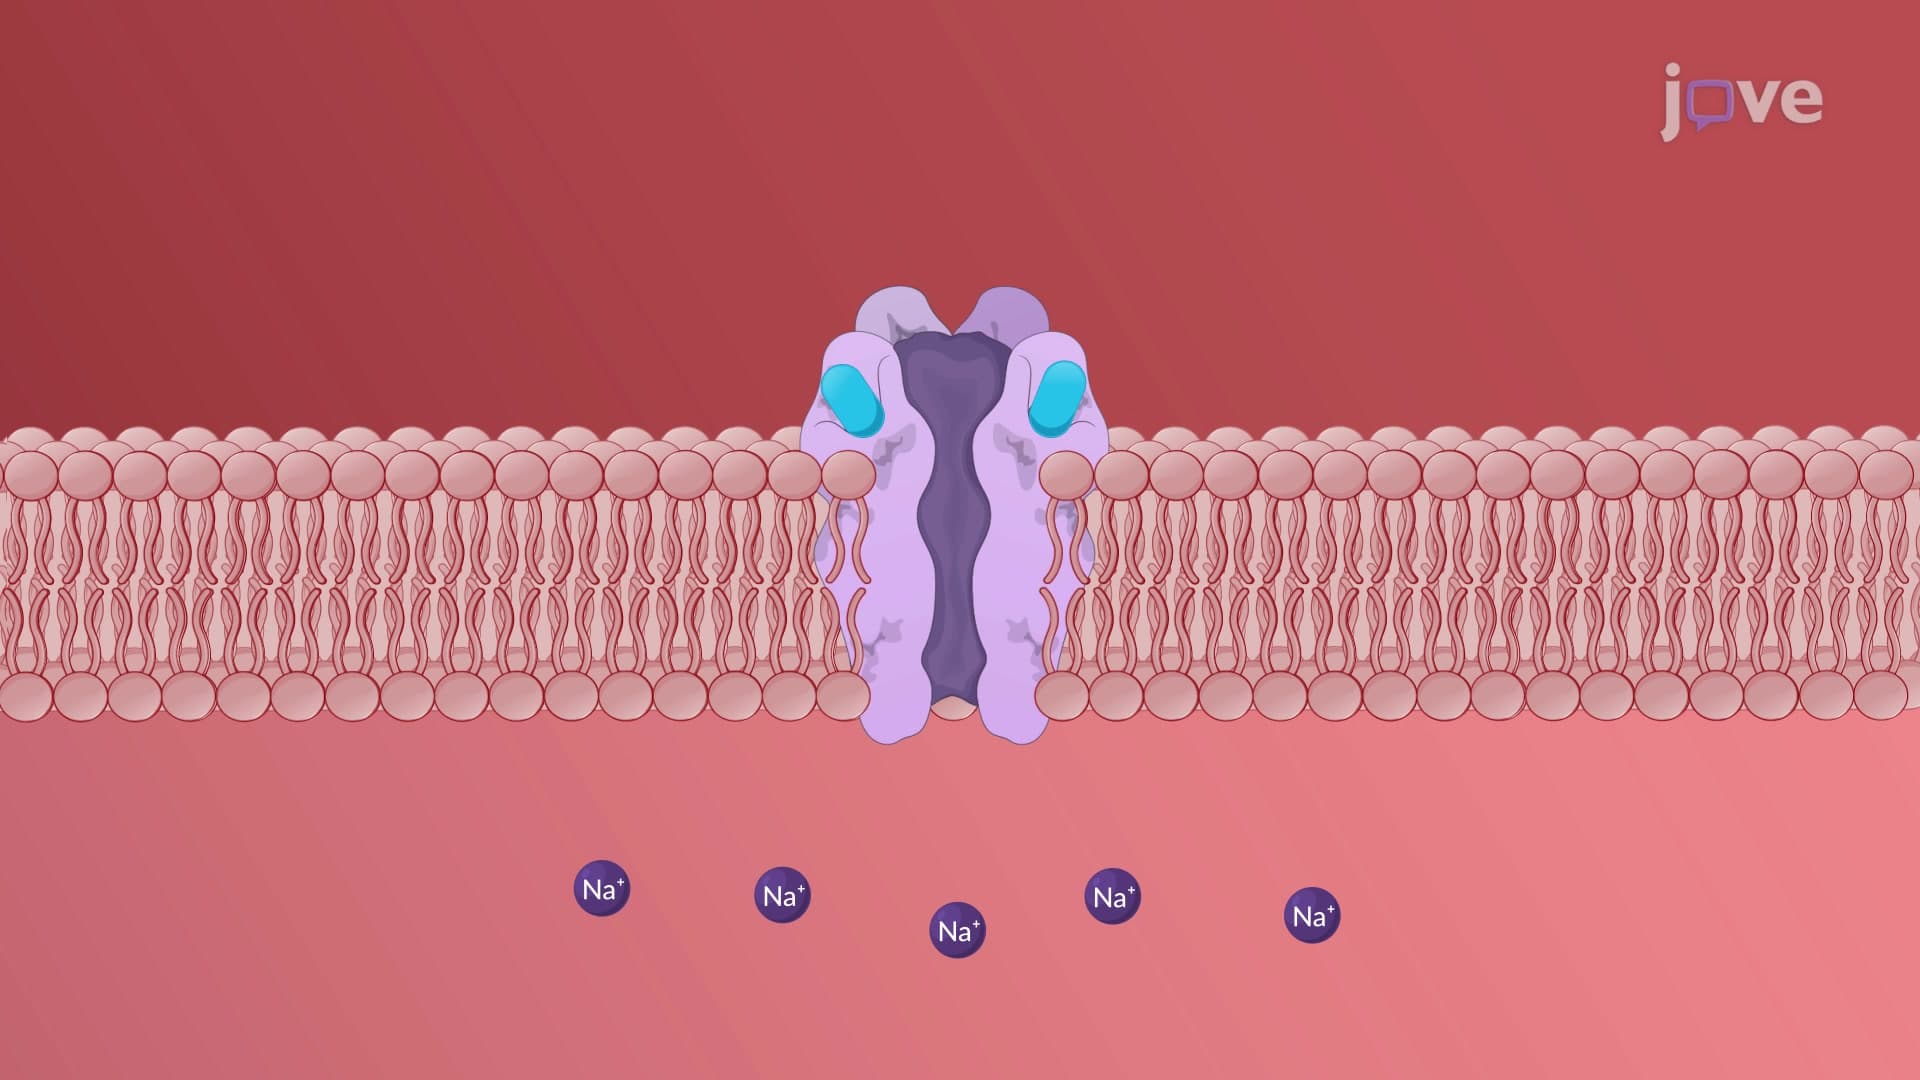
Depolarizing Blockers: Mechanism of Action
Succinylcholine is the most commonly used depolarizing blocker. Chemically, it constitutes two molecules of acetylcholine joined together by an acetate methyl group. They act on the receptors in the same way as acetylcholine. Because succinylcholine...