Related Experiment Videos
The role of Beta-blockers as first-line therapy in hypertension
Alberto Ranieri De Caterina1, Antonio Maria Leone
1Institute of Cardiology, Catholic University of the Sacred Heart, Policlinico A. Gemelli, Largo A. Gemelli, 8, 00168, Rome, Italy. adecatro@yahoo.it

Insights
Beta-blockers (BBs) are not recommended as first-line hypertension treatment due to less effective blood pressure reduction and poorer cardiovascular outcomes compared to other drugs. Evidence suggests BBs may increase stroke risk and are linked to worse overall cardiovascular prognosis.
Area of Science:
- Cardiology
- Pharmacology
Background:
- Current guidelines recommend beta-blockers (BBs) for uncomplicated hypertension prevention.
- However, BBs demonstrate reduced efficacy in lowering blood pressure, particularly central aortic pressure, compared to alternative antihypertensives.
Purpose of the Study:
- To evaluate the efficacy and safety of beta-blockers (BBs) as first-line agents for hypertension management.
- To assess the impact of BBs on cardiovascular outcomes, including stroke risk and overall prognosis.
Main Methods:
- Review of national and international guidelines.
- Analysis of recent meta-analyses comparing BBs with placebo and other antihypertensive drug classes.
- Consideration of factors influencing BBs' cardioprotective effects.
Main Results:
- BBs show weaker effects on blood pressure reduction compared to other agents.
- Meta-analyses indicate a limited benefit of BBs in stroke prevention and potentially worse cardiovascular outcomes.
- Factors like unfavorable metabolic profiles and lack of efficacy on left ventricular hypertrophy contribute to their mild cardioprotective effects.
Conclusions:
- Available evidence does not support the use of BBs as first-line therapy for uncomplicated hypertension.
- Further research is needed to determine if newer BBs like nebivolol and carvedilol offer improved cardiovascular outcomes compared to older agents.
Abstract:
National and international guidelines still recommend β-blockers (BBs) as first-line agents in uncomplicated prevention of hypertension. However, it has been shown that BBs reduce blood pressure less than other drugs, specifically with regard to central aortic pressure. More importantly, recent meta-analyses have highlighted that in primary prevention BBs are associated with a relatively weak effect in reducing stroke compared to placebo or no treatment and, compared with other drugs, show evidence of a worse cardiovascular outcome. Several reasons might explain their mild cardioprotective effect, such as their unfavorable metabolic properties, a lack of efficacy on left ventricular hypertrophy regression and endothelial dysfunction, and reduced patient compliance. Thus, the available evidence does not support the use of BBs as first-line drugs in the treatment of uncomplicated hypertension. It remains to be determined whether newer BBs, such as nebivolol and carvedilol, will be more effective than older compounds in improving cardiovascular prognosis.
Related Concept Videos
 01:28
Antihypertensive Drugs: Types of β-Blockers
 01:27
Adrenergic Antagonists: Pharmacological Actions of β-Receptor Blockers
 01:25
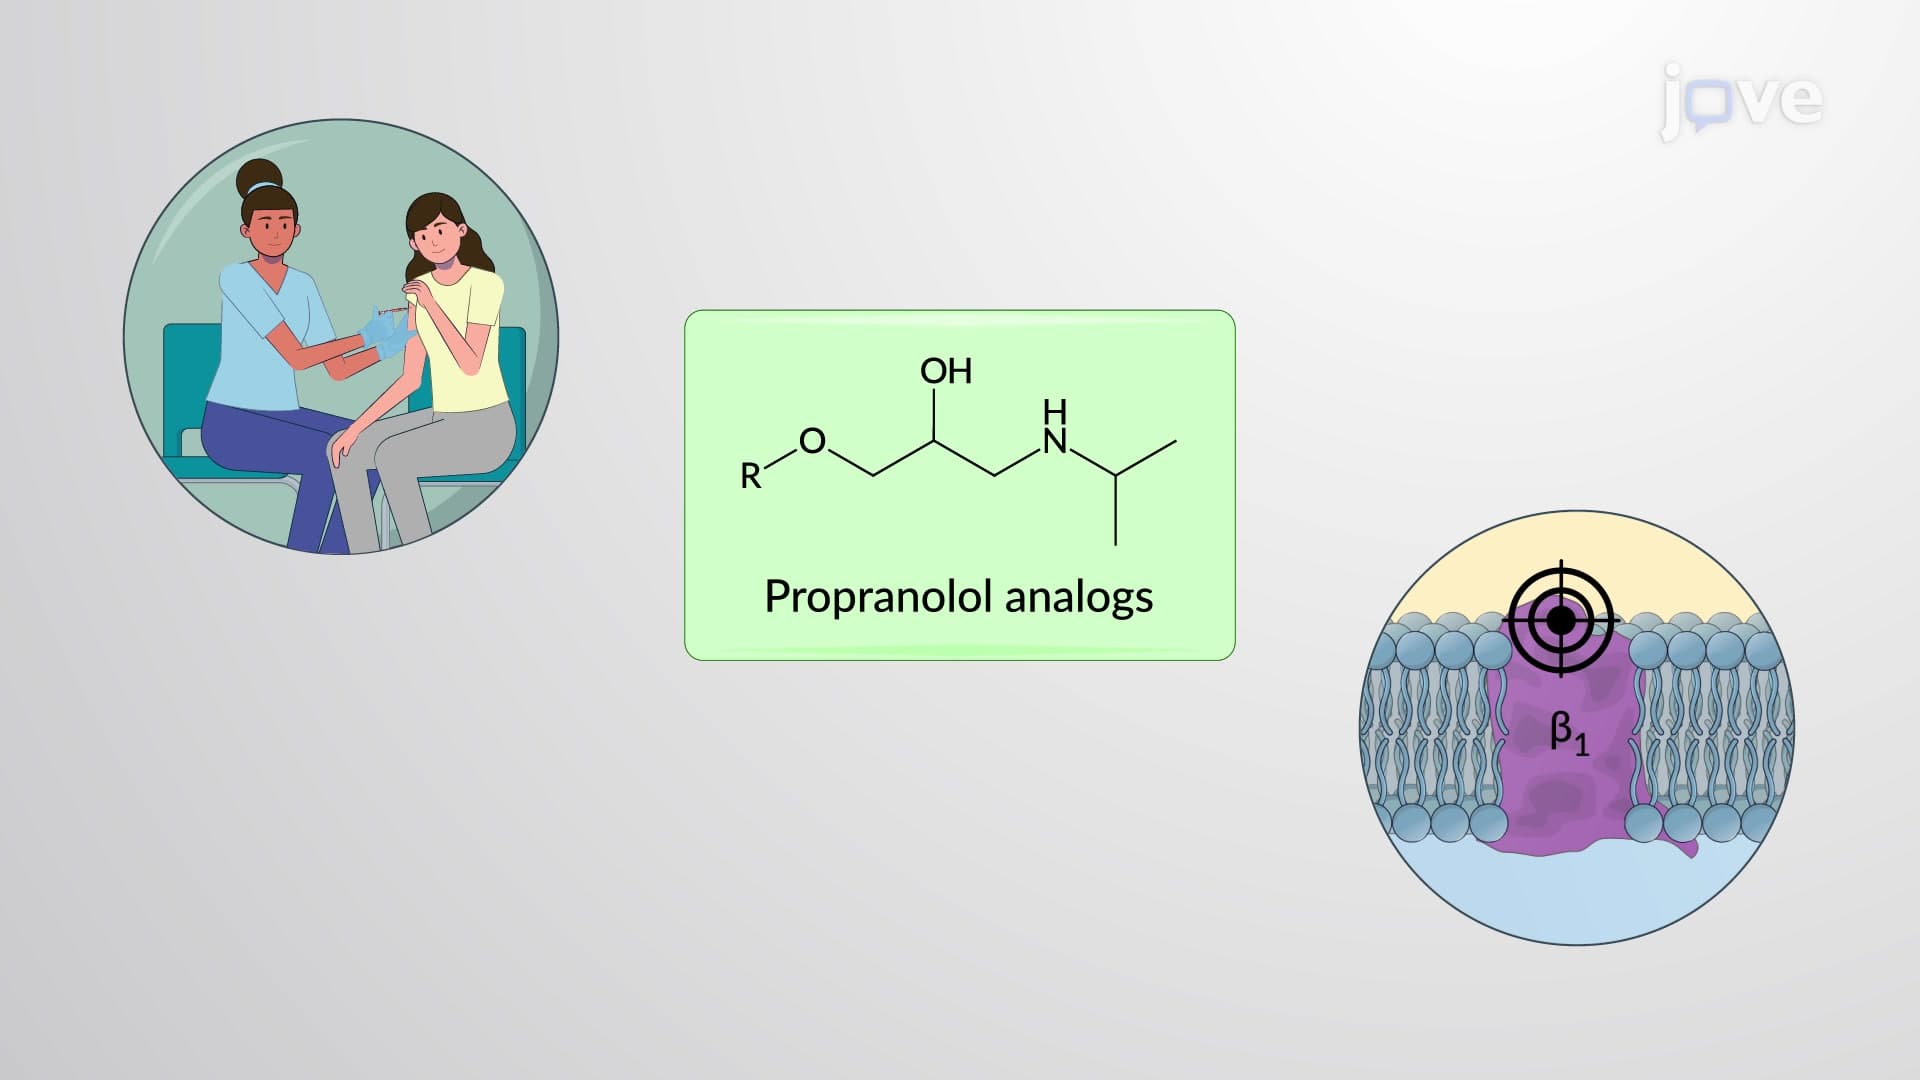
Adrenergic Antagonists: Chemistry and Classification of β-Receptor Blockers
 01:22
Heart Failure Drugs: β-Blockers
 01:17
Antihypertensive Drugs: Action of β1 Blockers
 01:28
Hypertension IV: Drug Therapy and Lifestyle Modifications