Related Experiment Video
Updated: Jun 4, 2026


Microfluidics in Assessing Platelet Function
Published on: November 8, 2024
Relationship between peripheral arterial reactive hyperemia and residual platelet reactivity after 600 mg clopidogrel
Michalis Hamilos1, Olivier Muller, Argyrios Ntalianis
1Cardiovascular Center Aalst, OLV Hospital, Moorselbaan 164, 9300, Aalst, Belgium.

Insights
Clopidogrel improves vascular endothelial function in stable angina patients, linked to effective platelet inhibition. This benefit is not seen in patients with high platelet reactivity after treatment.
Area of Science:
- Cardiology
- Pharmacology
- Vascular Biology
Background:
- Clopidogrel is known to reduce ischemic events in patients with coronary artery disease.
- The mechanism behind clopidogrel's benefits, particularly regarding endothelial function, is not fully understood.
- The association between clopidogrel's anti-platelet action and its effect on endothelial function requires further investigation.
Purpose of the Study:
- To test the hypothesis that clopidogrel's improvement of peripheral vascular endothelial function is associated with its inhibition of platelet aggregation.
- To determine if reduced platelet aggregation correlates with improved endothelial function markers after clopidogrel administration.
Main Methods:
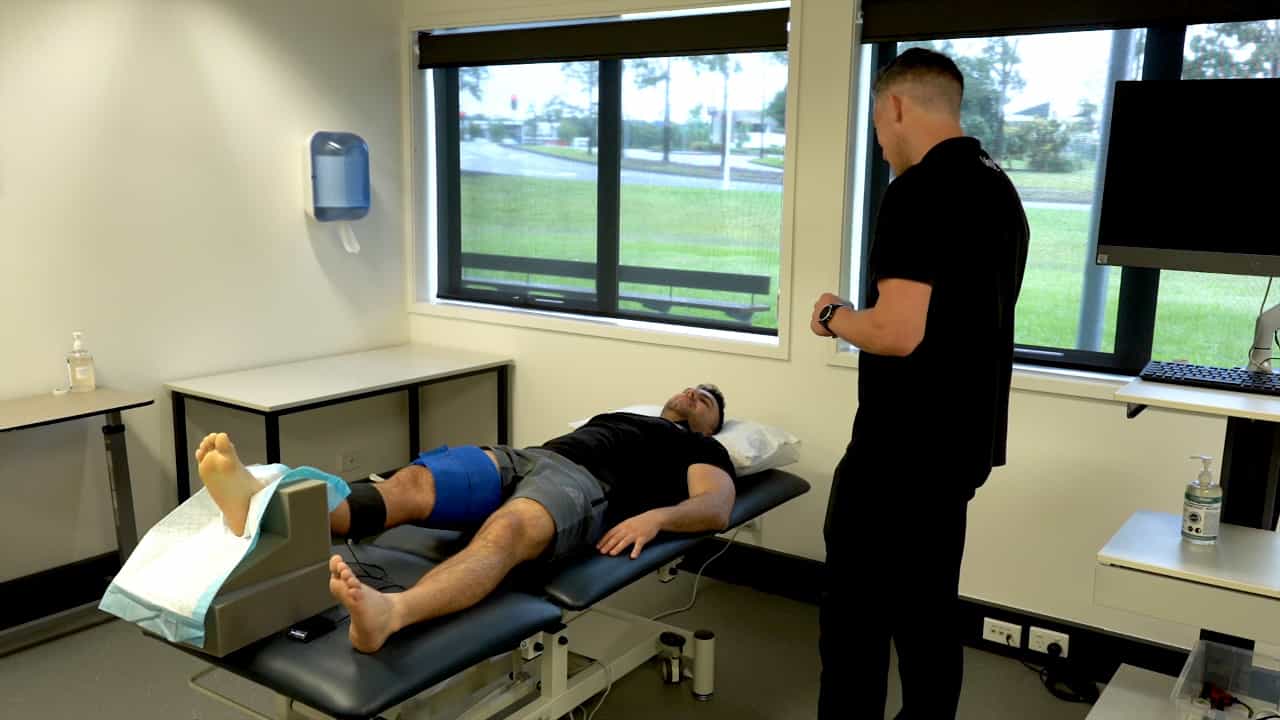
- Evaluated endothelial function using reactive hyperemia peripheral arterial tonometry (Endoscore) and circulating endothelial microparticles (EMPs) in 43 stable angina patients undergoing percutaneous coronary intervention.
- Assessed clopidogrel's response via VerifyNow P2Y12 assay, measuring platelet reaction unit (PRU) and percent platelet inhibition (%PI).
- Defined high platelet reactivity as PRU ≥ 240.
Main Results:
- Endothelial function improved in 20 patients after a 600 mg clopidogrel loading dose.
- Improved Endoscore was significantly correlated with lower PRU (r=-0.61) and higher %PI (r=0.57).
- Patients with PRU < 240 showed significant improvement in Endoscore and reduction in EMPs, unlike those with PRU ≥ 240.
Conclusions:
- A single 600 mg clopidogrel loading dose enhances vascular endothelial function in stable coronary artery disease patients.
- This endothelial improvement is contingent upon achieving optimal platelet inhibition.
- Patients exhibiting high platelet reactivity post-clopidogrel do not experience the same vascular endothelial benefits.
Abstract:
Clopidogrel reduces long-term ischemic events in patients with acute coronary syndrome or stable angina (SA) undergoing percutaneous coronary intervention (PCI). Endothelial function improvement has been proposed, among other factors, for this beneficial effect of clopidogrel, but whether this might be associated to its anti-platelet action remains unclear. We tested the hypothesis that clopidogrel improvement of peripheral vascular endothelial function might be associated with inhibition of platelet aggregation. Endothelial function was evaluated before and at least 12 h after 600 mg clopidogrel in 43 SA pts undergoing elective PCI by: (a) reactive hyperemia peripheral arterial tonometry (measuring the Endoscore); (b) circulating endothelial microparticles (EMPs). Response to clopidogrel was measured with point-of-care VerifyNow P2Y12 assay and expressed as platelet reaction unit (PRU) and percent platelet inhibition (%PI). High platelet reactivity after clopidogrel was defined as PRU ≥ 240. Endothelial function improved after clopidogrel in 20 pts. Changes in Endoscore (Δ Endoscore) were significantly correlated with both PRU (r = -0.61, P < 0.001) and %PI (r = 0.57, P < 0.001). Endoscore significantly increased after clopidogrel in pts with PRU < 240 (0.38 ± 0.26 to 0.57 ± 0.33, P < 0.001), but did not in pts with PRU ≥ 240 (0.53 ± 0.31 to 0.40 ± 0.37, P = 0.12). EMPs were also significantly reduced in pts with PRU < 240 (222 [140-593] to 142 [83-371]/μl, P = 0.001), while no changes were observed in pts with PRU ≥ 240 (256 [178-531] to 388 [238-499]/μl, P = 0.55). In patients with stable coronary artery disease, a single 600 mg clopidogrel loading dose improves vascular endothelial function. This improvement is associated with optimal platelet inhibition and it is not observed in patients with post-clopidogrel high platelet reactivity.

Related Concept Videos
 01:27
Peripheral Artery Disease III: Interprofessional Care
 01:20
Antiplatelet Drugs: Prostaglandin Synthesis, P2Y12 and Glycoprotein IIb/IIIa Inhibitors
Prostaglandin synthesis inhibitors, exemplified by the widely known aspirin, wield their power by irreversibly acetylating...
 01:22
Formation of the Platelet Plug
As the injured blood vessel contracts, endothelial cells undergo contraction, revealing collagen fibers in the basement membrane and underlying connective tissue. Furthermore, the plasma membrane of endothelial cells becomes adhesive, preparing the site for platelet adhesion. Platelets...
 01:30
Peripheral Artery Disease I: Introduction
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation